Related Experiment Video
Updated: Jun 6, 2026
Automated Measurement of Pulmonary Emphysema and Small Airway Remodeling in Cigarette Smoke-exposed Mice
Published on: January 16, 2015
Systematic review of the evidence relating FEV1 decline to giving up smoking
1PN Lee Statistics and Computing Ltd, Surrey, UK. PeterLee@pnlee.co.uk

Background:
The rate of forced expiratory volume in 1 second (FEV1) decline ("beta") is a marker of chronic obstructive pulmonary disease risk. The reduction in beta after quitting smoking is an upper limit for the reduction achievable from switching to novel nicotine delivery products. We review available evidence to estimate this reduction and quantify the relationship of smoking to beta.
Methods:
Studies were identified, in healthy individuals or patients with respiratory disease, that provided data on beta over at least 2 years of follow-up, separately for those who gave up smoking and other smoking groups. Publications to June 2010 were considered. Independent beta estimates were derived for four main smoking groups: never smokers, ex-smokers (before baseline), quitters (during follow-up) and continuing smokers. Unweighted and inverse variance-weighted regression analyses compared betas in the smoking groups, and in continuing smokers by amount smoked, and estimated whether beta or beta differences between smoking groups varied by age, sex and other factors.
Results:
Forty-seven studies had relevant data, 28 for both sexes and 19 for males. Sixteen studies started before 1970. Mean follow-up was 11 years. On the basis of weighted analysis of 303 betas for the four smoking groups, never smokers had a beta 10.8 mL/yr (95% confidence interval (CI), 8.9 to 12.8) less than continuing smokers. Betas for ex-smokers were 12.4 mL/yr (95% CI, 10.1 to 14.7) less than for continuing smokers, and for quitters, 8.5 mL/yr (95% CI, 5.6 to 11.4) less. These betas were similar to that for never smokers. In continuing smokers, beta increased 0.33 mL/yr per cigarette/day. Beta differences between continuing smokers and those who gave up were greater in patients with respiratory disease or with reduced baseline lung function, but were not clearly related to age or sex.
Conclusion:
The available data have numerous limitations, but clearly show that continuing smokers have a beta that is dose-related and over 10 mL/yr greater than in never smokers, ex-smokers or quitters. The greater decline in those with respiratory disease or reduced lung function is consistent with some smokers having a more rapid rate of FEV1 decline. These results help in designing studies comparing continuing smokers of conventional cigarettes and switchers to novel products.
Related Concept Videos
 01:26
COPD: Management Using Bronchodilators and Corticosteroids
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
COPD: Pathogenesis and Clinical Features
The primary cause for the onset of COPD is cigarette smoking and exposure to air pollution. These hazardous factors initiate a chain reaction within the lungs, resulting in chronic inflammation, damage to the airways, and a...
 01:23
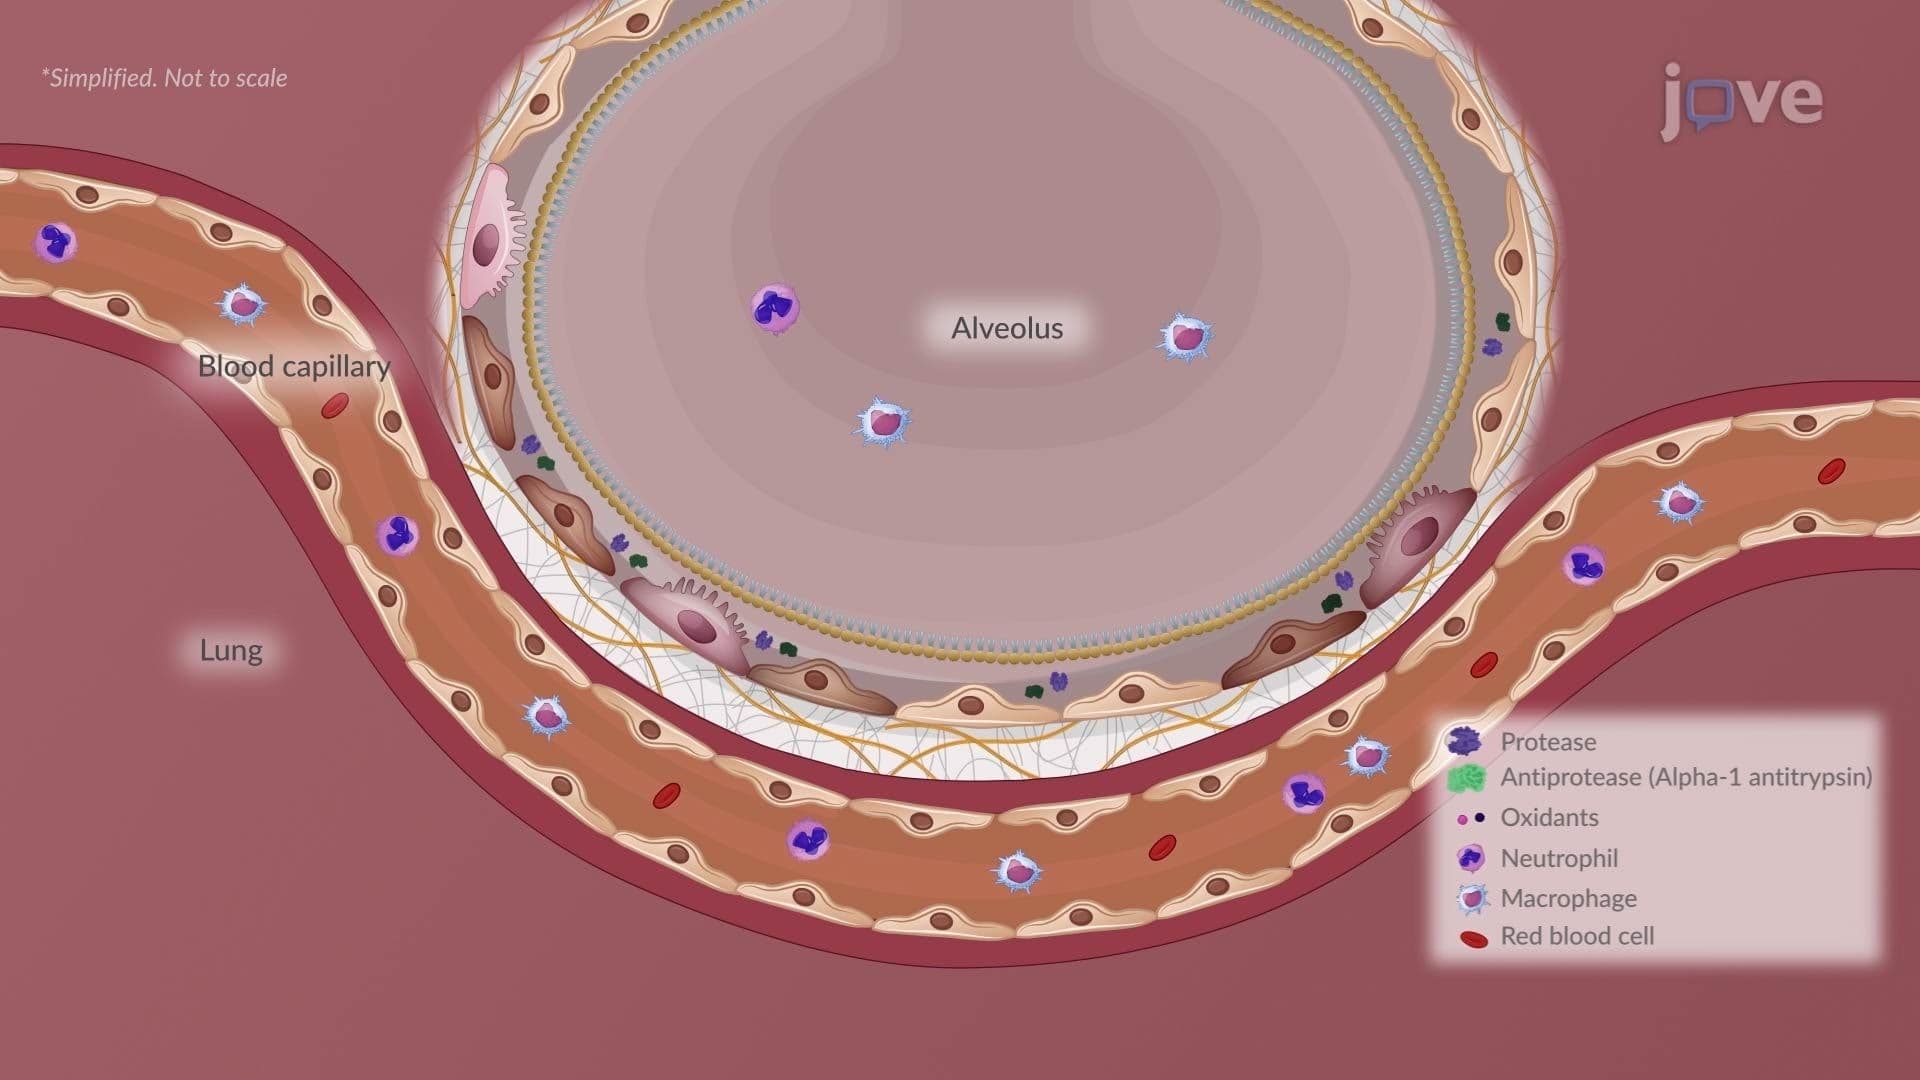
Chronic Obstructive Pulmonary Disease II: Emphysema
 01:29
Chronic Obstructive Pulmonary Disease-V: Management
Smoking Cessation
 01:25
Statistical Methods for Analyzing Epidemiological Data