Related Experiment Video
Updated: Jun 5, 2026
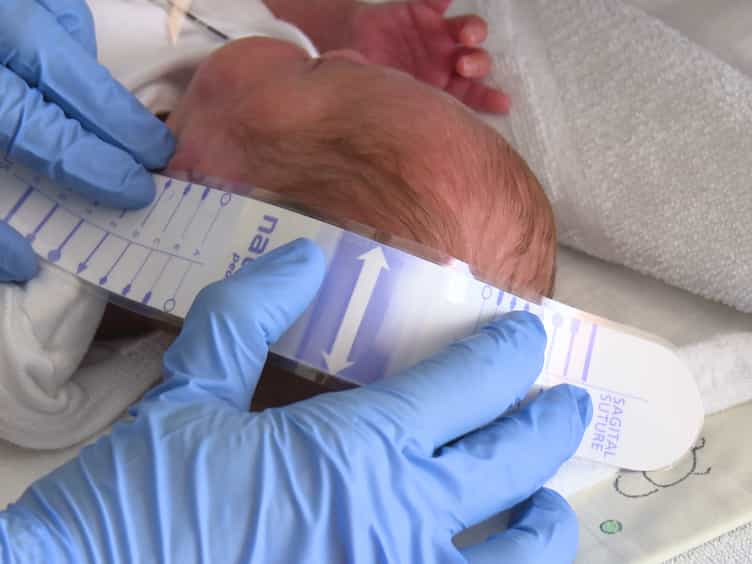

Application of an Amplitude-integrated EEG Monitor (Cerebral Function Monitor) to Neonates
Published on: September 6, 2017
Economic evaluation of caffeine for apnea of prematurity
Dmitry Dukhovny1, Scott A Lorch, Barbara Schmidt
1Division of Newborn Medicine, Harvard Medical School, Boston, Massachusetts, USA.

Insights
Caffeine therapy for premature infants with apnea is cost-effective, offering better outcomes and lower costs compared to placebo. This treatment is economically appealing for infants under 1250g up to 21 months corrected age.
Area of Science:
- Neonatal Medicine
- Health Economics
- Pharmacoeconomics
Background:
- Apnea of prematurity affects infants with low birth weights (<1250 g).
- Effective and economical treatments are crucial for this vulnerable population.
- Caffeine citrate is a common treatment for apnea of prematurity.
Purpose of the Study:
- To evaluate the cost-effectiveness of caffeine versus placebo for apnea of prematurity.
- To analyze treatment costs from birth through 18-21 months corrected age.
- To determine if caffeine therapy provides better outcomes at a lower cost.
Main Methods:
- Retrospective economic evaluation using data from the Caffeine for Apnea of Prematurity trial (N=1869).
- Included direct medical costs; excluded parental and societal costs.
- Calculated cost per survivor without neurodevelopmental impairment, using 2008 CAD, discounted at 3%.
Main Results:
- Mean cost per infant was $124,466 (caffeine) vs. $133,505 (placebo).
- Caffeine therapy resulted in lower costs (difference $9,039) and better outcomes in >99% of analyses.
- Results remained robust even with a 1000% increase in resource costs.
Conclusions:
- Caffeine therapy is a dominant, cost-effective treatment for apnea of prematurity in low birth weight infants.
- The economic benefits of caffeine extend through 18-21 months corrected age.
- Caffeine citrate presents an economically appealing option compared to placebo.
Objective:
To determine the cost-effectiveness of treatment with caffeine compared with placebo for apnea of prematurity in infants with birth weights less than 1250 g, from birth through 18 to 21 months' corrected age.
Methods:
We undertook a retrospective economic evaluation of the cost per survivor without neurodevelopmental impairment by using individual-patient data from the Caffeine for Apnea of Prematurity clinical trial (N = 1869). We included direct medical costs either to the insurance payer or the hospital but excluded costs to parents and society, such as lost productivity. We used a price of $0.21/mg of generic caffeine citrate for our base-case analysis. All costs were expressed in 2008 Canadian dollars and discounted at 3%. The time horizon for this analysis extended through 18 to 21 months' corrected age to match the clinical trial.
Results:
The mean cost per infant was $124 466 in the caffeine group and $133 505 in the placebo group (difference: $9039 [-14 749 to -3375]; adjusted P = .014). Cost-effectiveness analysis showed caffeine to be a dominant or "win-win" therapy: in >99% of 1000 bootstrap replications of the analysis, caffeine-treated infants had simultaneously better outcomes and lower mean costs. These results were robust to a 1000% increase in the individual resource items, including the price of caffeine citrate.
Conclusions:
In comparison with placebo, caffeine therapy for apnea of prematurity in infants weighing less than 1250 g is economically appealing for infants up to 18 to 21 months' corrected age.

