Related Experiment Video
Updated: Jun 5, 2026

Novel and Innovative Hybrid Technique for Type A Aortic Dissection
Published on: March 28, 2025
Epidemiology of thoracic aortic dissection
Scott A LeMaire1, Ludivine Russell
1The Division of Cardiothoracic Surgery, Michael E. DeBakey Department of Surgery, Baylor College of Medicine, One Baylor Plaza, Houston, TX 77030, USA. slemaire@bcm.edu

Abstract:
Thoracic aortic dissection (TAD) is estimated to occur at a rate of 3-4 cases per 100,000 persons per year and is associated with a high mortality. Reported rates are probably underestimates of the true incidence of TAD because of difficulties in diagnosis. The incidence of TAD appears to have been increasing over time. TAD is most common in men and older individuals. Aortic dilatation is a well-established risk factor for TAD but is not a prerequisite; most ascending aortic dissections occur when aortic diameter is <5.5 cm. Although atherosclerosis and typical cardiovascular risk factors, such as hypertension and smoking, are associated with TAD, evidence supporting their direct causal role is lacking. Notably, diabetes mellitus is remarkably uncommon in patients with TAD. Other risk factors for TAD include inflammatory diseases, iatrogenic aortic injury, and drug use. Congenital cardiovascular defects, such as bicuspid aortic valve, and certain genetic syndromes, such as Marfan syndrome, are the genetic factors most commonly associated with TAD. Specific nonsyndromic genetic mutations in families and single nucleotide polymorphisms have also been identified as possible risk factors for TAD.

Related Concept Videos
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Aneurysm I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:15
Aortic Regurgitation I: Introduction
 01:26
Aneurysm III: Interprofessional Care
 01:15
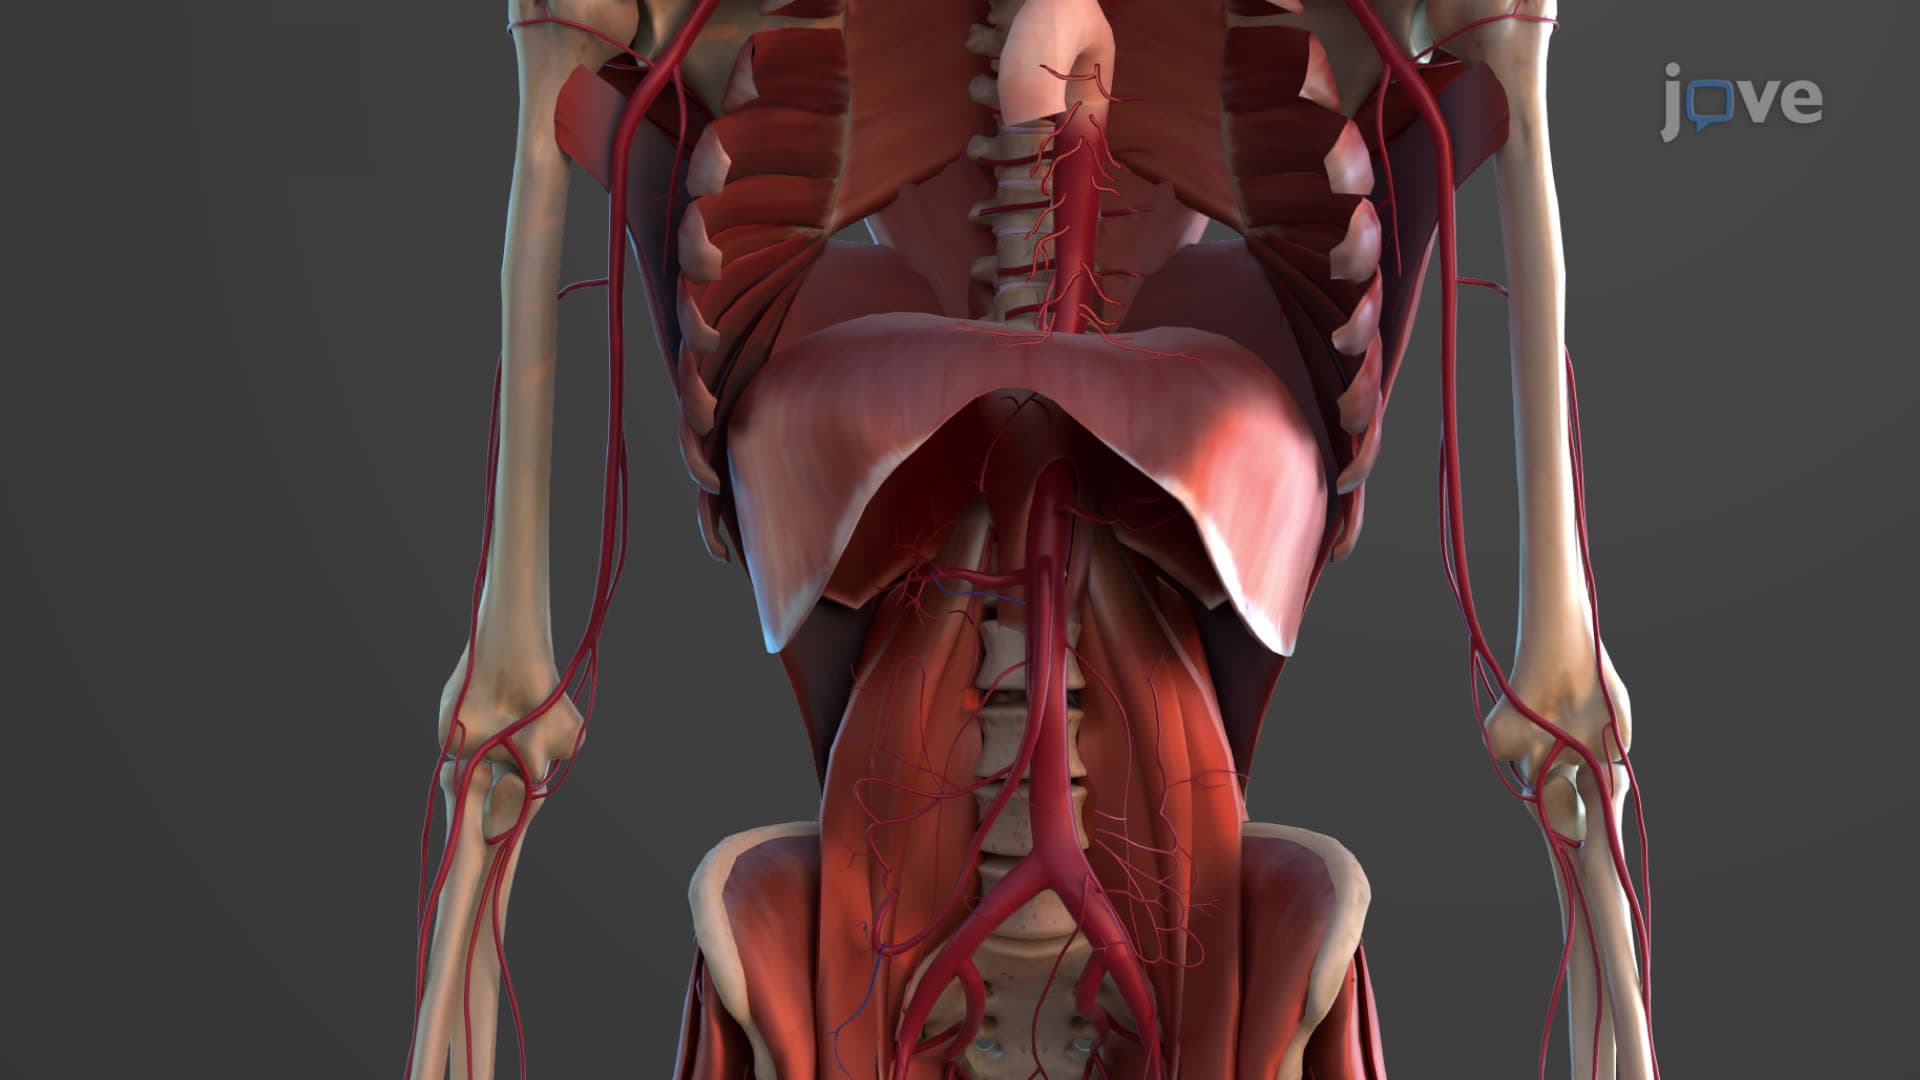
Thoracic Aorta