Sodium balance in maintenance hemodialysis
Related Experiment Video
Updated: Jun 5, 2026
Measurement of Tissue Oxygenation Using Near-Infrared Spectroscopy in Patients Undergoing Hemodialysis
Published on: October 2, 2020
Sergio F F Santos1, Aldo J Peixoto
1Division of Nephrology, State University of Rio de Janeiro, Rio de Janeiro, Brazil. aldo.peixoto@yale.edu

Maintenance of extracellular fluid volume balance is an essential role of chronic maintenance hemodialysis (HD). In this population, this balance is determined by salt intake during the interdialytic period and sodium removal in HD sessions. Most of the sodium in a HD session is removed by ultrafiltration of plasma water, and the diffusion process becomes responsible for the fine tuning of sodium balance. The observation of little variation in pre-HD serum sodium denotes that HD patients have an individual, stable osmolar set point. A positive dialysate-to-plasma sodium gradient is associated with increased thirst, interdialytic weight gain, and hypertension. To achieve an isonatric HD session, dialysate sodium concentration should approximately match patient's serum sodium, and all sodium gained in the interdialytic period must be removed by convection. The pre-HD serum sodium concentration may be used as a reference for dialysate sodium prescription in chronic HD. In this article, we also discuss new aspects of sodium balance, with particular attention to new observations on nonosmolar interstitial sodium storage.
Maintenance of extracellular fluid volume balance is an essential role of chronic maintenance hemodialysis (HD). In this population, this balance is determined by salt intake during the interdialytic period and sodium removal in HD sessions. Most of the sodium in a HD session is removed by ultrafiltration of plasma water, and the diffusion process becomes responsible for the fine tuning of sodium balance. The observation of little variation in pre-HD serum sodium denotes that HD patients have an individual, stable osmolar set point. A positive dialysate-to-plasma sodium gradient is associated with increased thirst, interdialytic weight gain, and hypertension. To achieve an isonatric HD session, dialysate sodium concentration should approximately match patient's serum sodium, and all sodium gained in the interdialytic period must be removed by convection. The pre-HD serum sodium concentration may be used as a reference for dialysate sodium prescription in chronic HD. In this article, we also discuss new aspects of sodium balance, with particular attention to new observations on nonosmolar interstitial sodium storage.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications
 01:25
Peritoneal Dialysis III: Nursing Management
 01:26
Regulation of Sodium and Potassium
Sodium Regulation
Sodium ions make up approximately 90% of extracellular cations, with a normal blood plasma concentration of 136–148 mEq/L. A decrease in blood volume and pressure triggers the release of renin from granular cells in the juxtaglomerular complex (JGC), primarily in...
 01:29
Renal Regulation of Acid-Base Balance
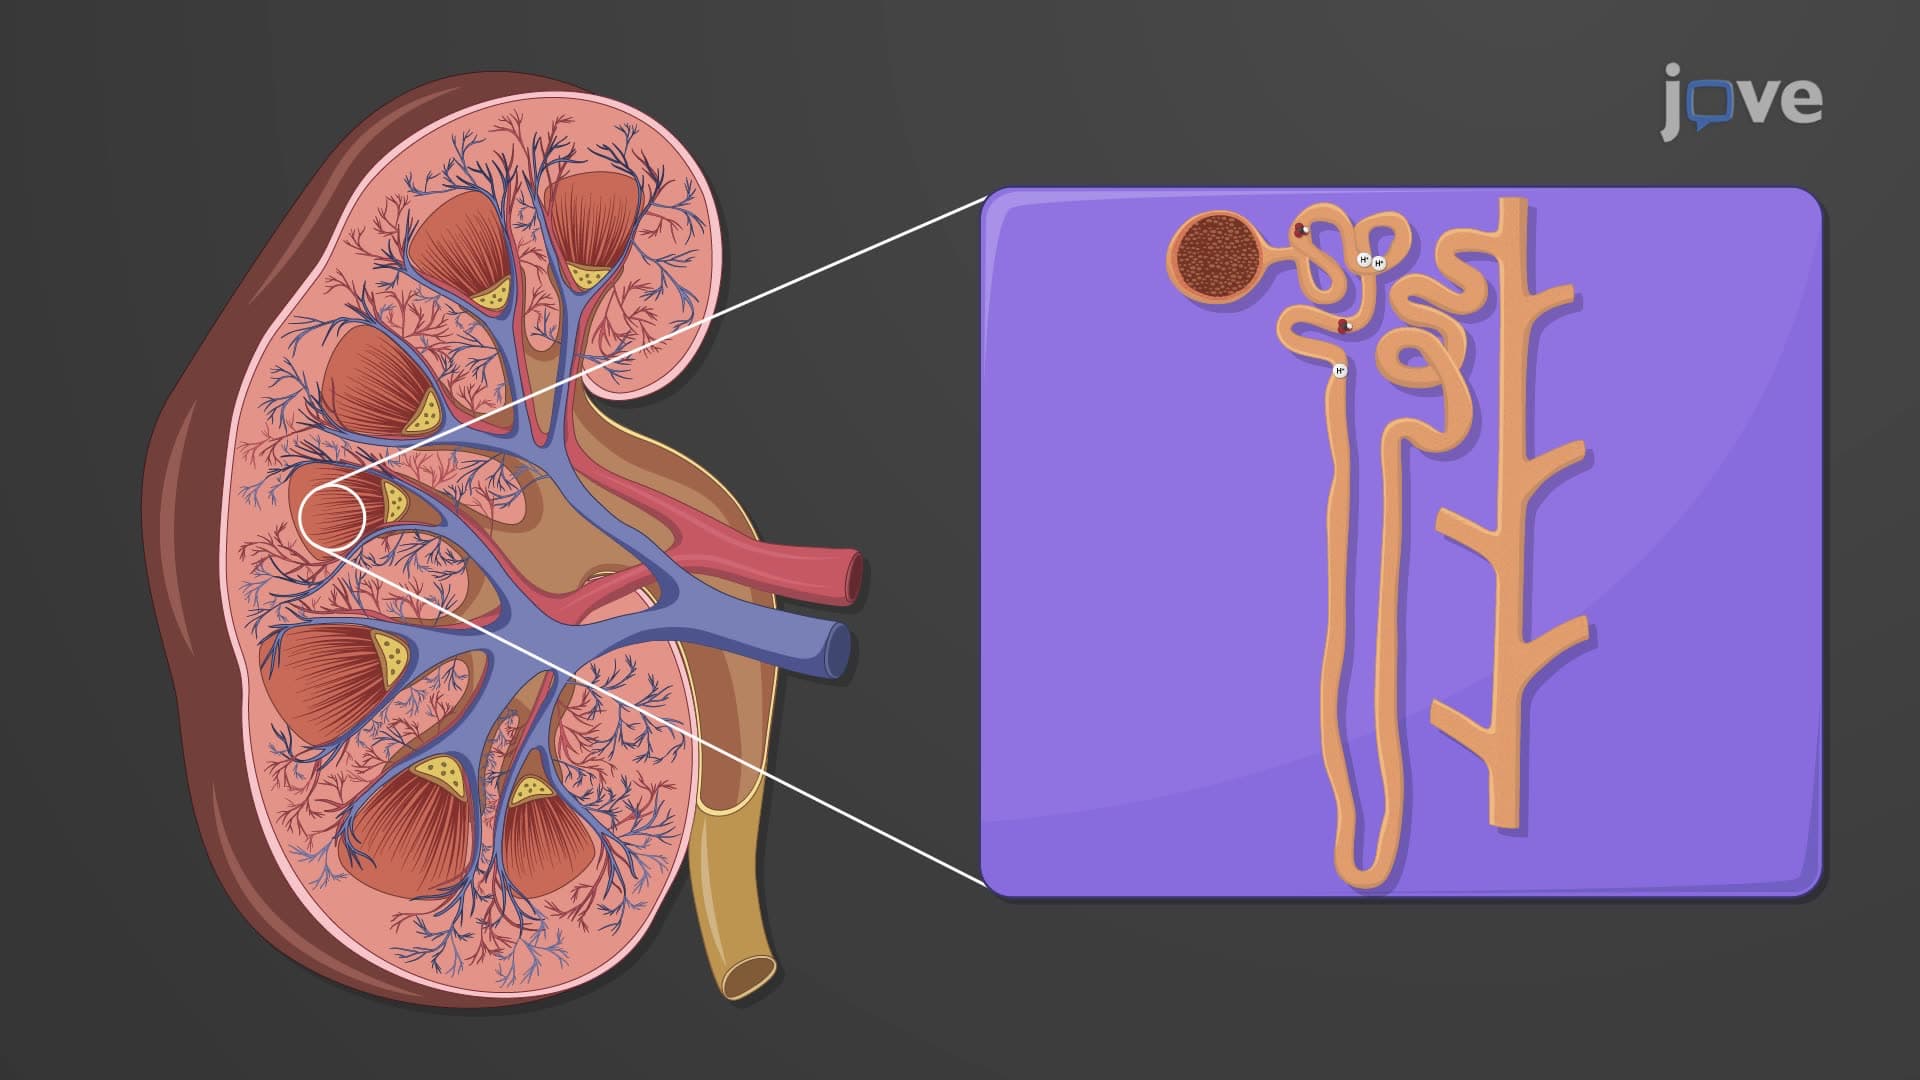
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:25
Hemodialysis I: Introduction