Related Experiment Video
Updated: Jun 5, 2026
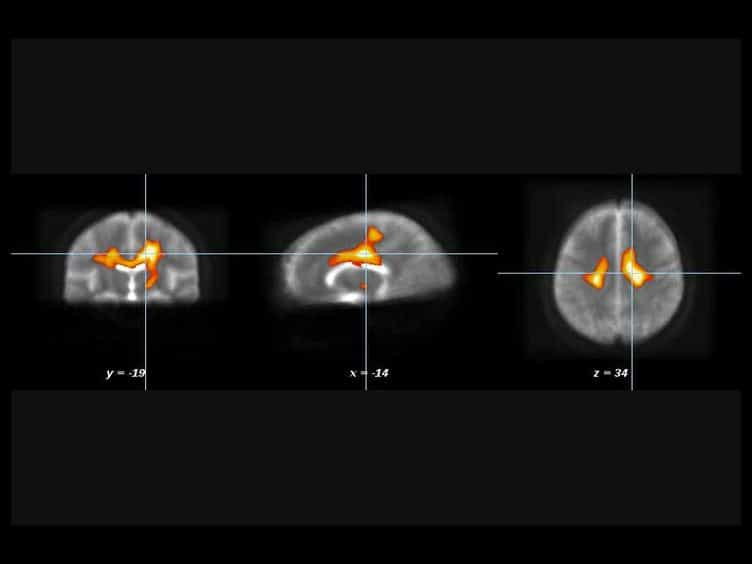

Diffusion Tensor Magnetic Resonance Imaging in the Analysis of Neurodegenerative Diseases
Published on: July 28, 2013
White matter damage in Alzheimer disease and its relationship to gray matter atrophy
Federica Agosta1, Michela Pievani, Stefania Sala
1Neuroimaging Research Unit, Institute of Experimental Neurology, Division of Neuroscience, Scientific Institute and University Ospedale San Raffaele, Via Olgettina 60, 20132 Milan, Italy.

Purpose:
To explore the regional patterns of white matter (WM) tract damage in (a) patients with probable Alzheimer disease (AD) and (b) patients with amnestic mild cognitive impairment (aMCI) and at least one abnormal biomarker and to investigate whether WM damage is related to gray matter (GM) atrophy.
Materials And Methods:
This study was approved by the institutional review board, and written informed consent was obtained from each participant. Twenty-three patients with AD, 15 patients with aMCI, and 15 healthy control subjects underwent diffusion tensor magnetic resonance imaging. WM tract damage was investigated by using tract-based spatial statistics, and GM atrophy was measured by using voxel-based morphometry.
Results:
Compared with control subjects, patients with AD had an increase in mean diffusivity in all major WM tracts studied, including the limbic, cortico-cortical, interhemispheric, and corticospinal tracts. Conversely, fractional anisotropy decreased only in the parahippocampal tract, fornix, and small, inferior parietal regions. In addition, patients with AD showed a widespread increase in axial and radial diffusivity compared with control subjects. Patients with aMCI showed an increase in axial diffusivity only in tracts projecting to the frontal cortex and splenium of the corpus callosum. Significant and anatomically congruent correlations between WM changes and regional GM atrophy were found in patients with AD. Conversely, damage to most WM tracts in patients with aMCI did not correlate with GM atrophy.
Conclusion:
In AD, the observed patterns of WM abnormalities may reflect the advanced phase of a secondary degenerative process and an association, especially in the early phases of the disease, with primary WM tract damage over and above GM abnormalities.
Insights
Alzheimer disease (AD) shows widespread white matter (WM) damage, while amnestic mild cognitive impairment (aMCI) exhibits more localized WM changes. WM damage in AD correlates with gray matter (GM) atrophy, but not in aMCI.
Area of Science:
- Neuroimaging
- Neurology
- Biomarkers
Background:
- Alzheimer disease (AD) and amnestic mild cognitive impairment (aMCI) are associated with neurodegeneration.
- White matter (WM) integrity is crucial for cognitive function and can be affected in neurodegenerative diseases.
- Understanding the patterns of WM damage and their relationship with gray matter (GM) atrophy is vital for early diagnosis and treatment.
Purpose of the Study:
- To investigate regional WM tract damage in patients with probable AD and biomarker-positive aMCI.
- To determine the relationship between WM damage and GM atrophy in these patient groups.
- To differentiate WM pathology patterns between AD and aMCI.
Main Methods:
- Diffusion tensor magnetic resonance imaging (DT-MRI) was used to assess WM integrity.
- Tract-based spatial statistics (TBSS) analyzed WM tract damage.
- Voxel-based morphometry (VBM) quantified GM atrophy.
Main Results:
- Patients with AD exhibited increased mean diffusivity in all major WM tracts and increased axial/radial diffusivity.
- WM damage in AD correlated significantly with regional GM atrophy.
- Patients with aMCI showed increased axial diffusivity in specific frontal and callosal tracts, with limited correlation to GM atrophy.
Conclusions:
- WM abnormalities in AD may indicate a secondary degenerative process, with early stages potentially showing primary WM damage.
- WM tract damage in AD is associated with GM atrophy.
- WM changes in aMCI are more localized and less correlated with GM atrophy compared to AD.
More Related Videos
 12:50
Lesion Explorer: A Video-guided, Standardized Protocol for Accurate and Reliable MRI-derived Volumetrics in Alzheimer's Disease and Normal Elderly
Published on: April 14, 2014
 10:52
Correlative Light and Electron Microscopy to Study Microglial Interactions with β-Amyloid Plaques
Published on: June 1, 2016
Related Concept Videos
 01:23
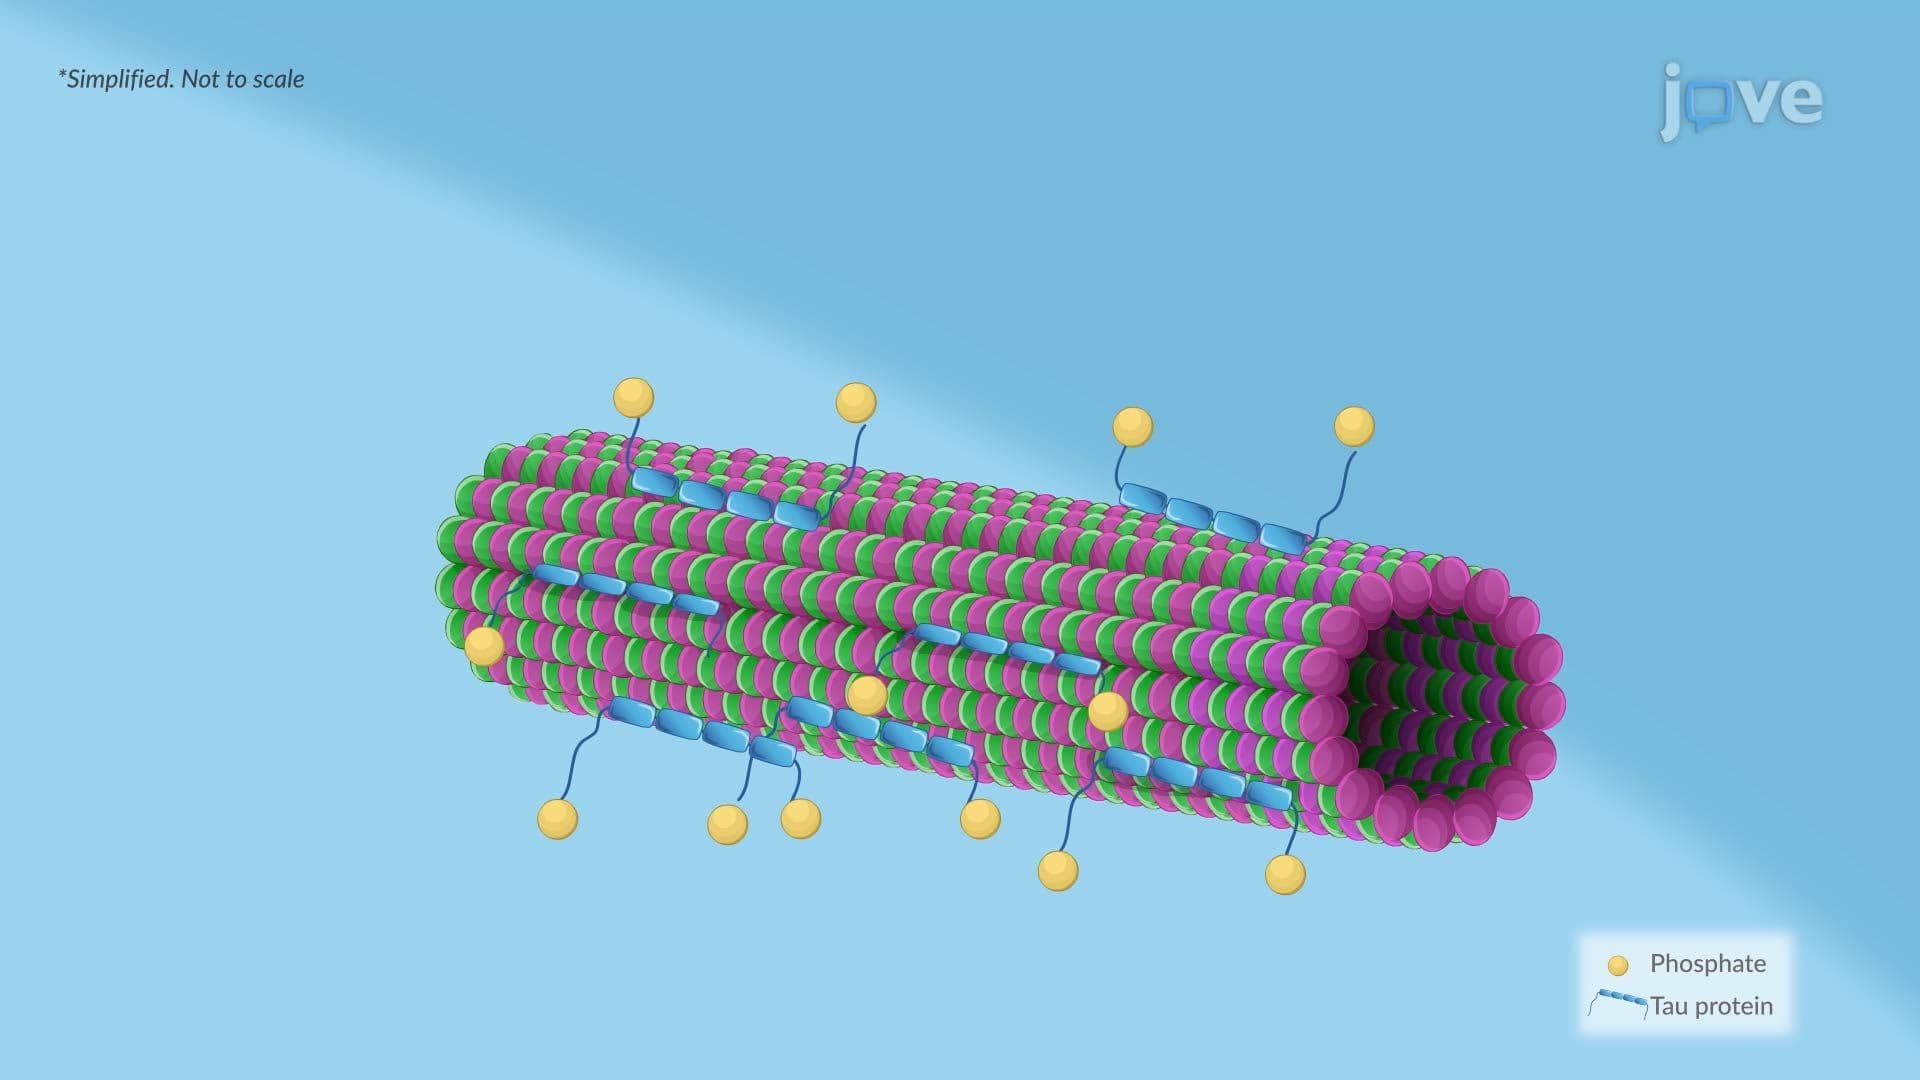
Alzheimer Disease ll: Pathophysiology
 01:29
Alzheimer Disease l: Introduction
 01:26
Alzheimer's Disease: Overview
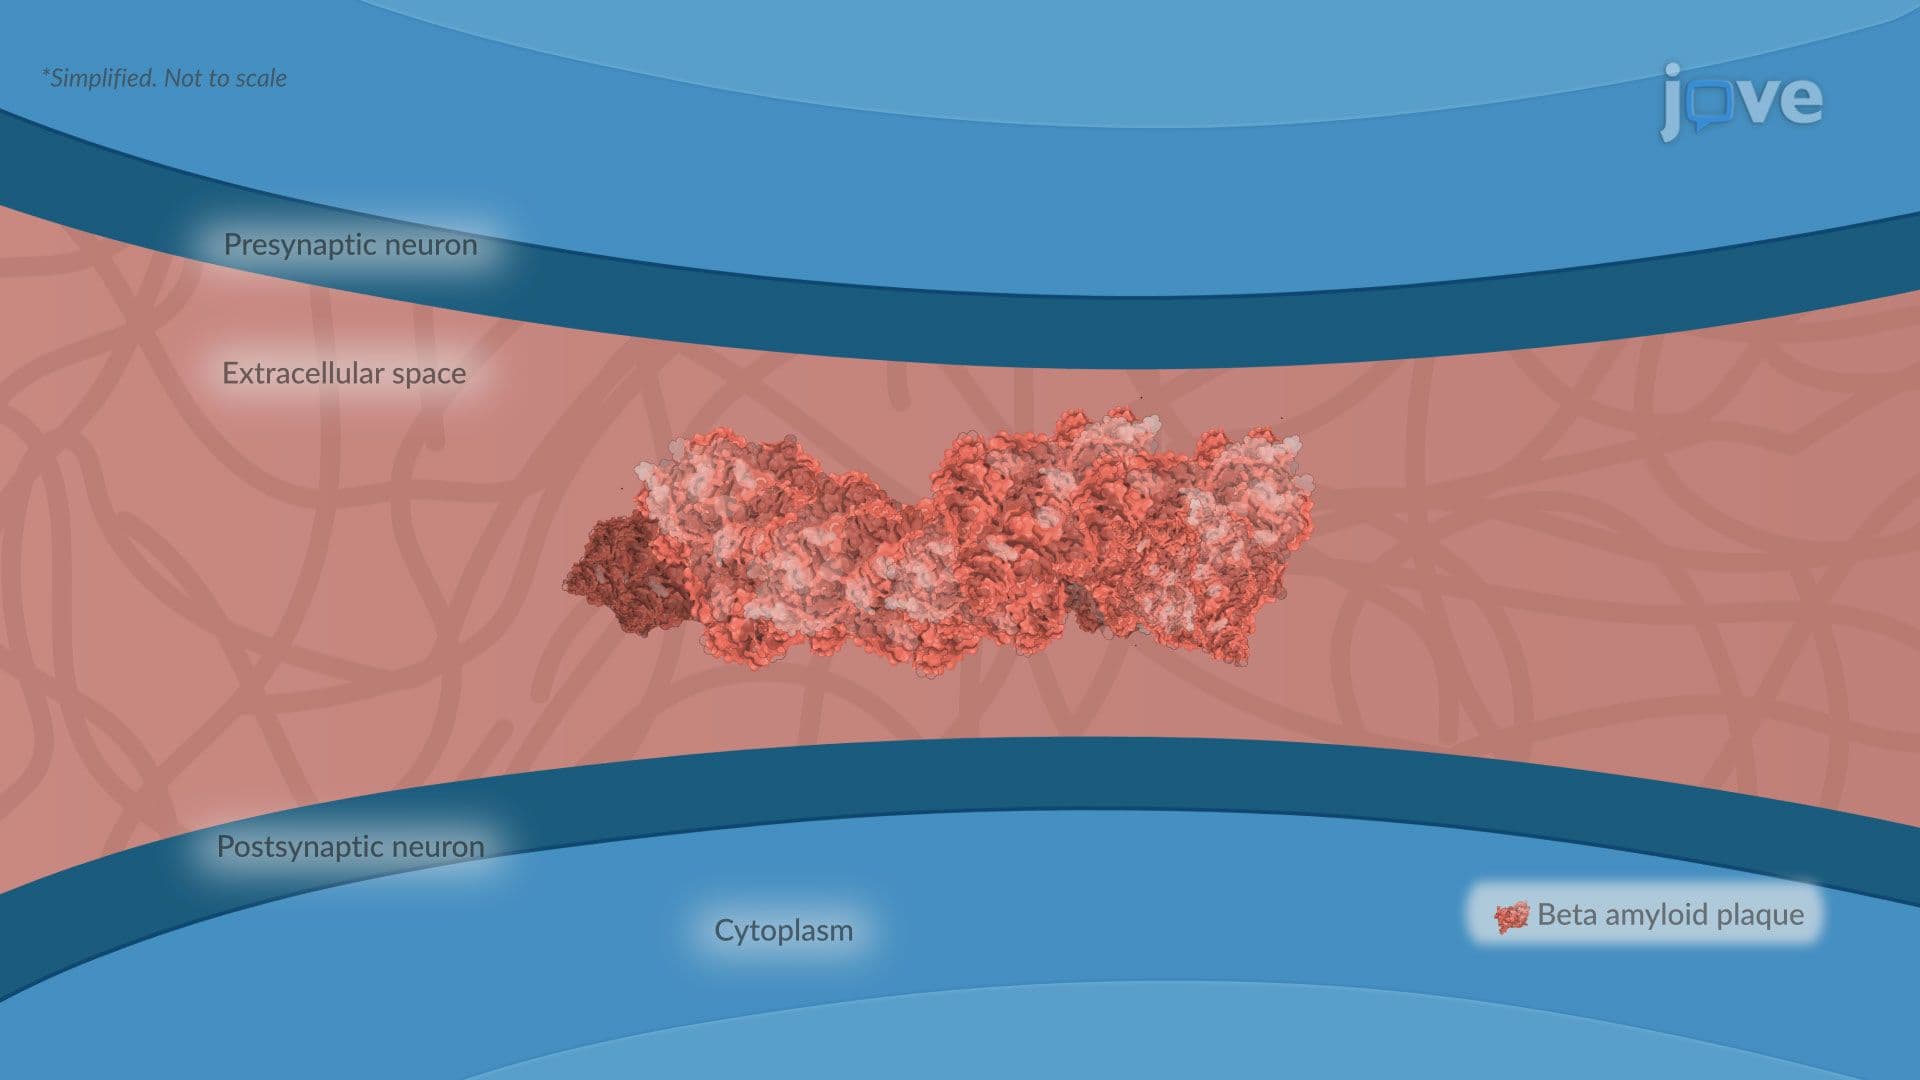
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Dementia l: Introduction
 01:22
Alzheimer's Disease: Treatment
 01:30
Dementia
The progression of dementia is generally gradual.