Related Experiment Video
Updated: Jun 5, 2026


Subcutaneous Infection of Methicillin Resistant Staphylococcus Aureus (MRSA)
Published on: February 9, 2011
Prevalence and risk factor analysis for methicillin-resistant Staphylococcus aureus nasal colonization in children
Melissa B Miller1, David J Weber, Jennifer S Goodrich
1UNC School of Medicine, Department of Pathology and Laboratory Medicine, Campus Box 7525, Chapel Hill, NC 27599, USA. mbmiller@unch.unc.edu

Abstract:
Children attending child care centers (CCCs) are at increased risk for infections, including those caused by methicillin-resistant Staphylococcus aureus (MRSA). Nasal colonization often precedes infection, and MRSA colonization has been associated with increased infection risk. Community-associated MRSA (CA-MRSA) has caused increased MRSA infections in the general population, including children. Little is known about the frequency of MRSA nasal colonization in young children, particularly in those attending CCCs where disease transmission is common. We sampled the nares of 1,163 children in 200 classrooms from 24 CCCs in North Carolina and Virginia to assess S. aureus colonization. MRSA strains were molecularly analyzed for staphylococcal cassette chromosome mec (SCCmec) type, Panton-Valentine leukocidin status, and multilocus sequence type. A case-control study was performed to identify risk factors for MRSA colonization. We found that 18.1% children were colonized with S. aureus and 1.3% with MRSA. Molecular analysis of the MRSA strains identified 47% as CA-MRSA and 53% as health care-associated MRSA (HA-MRSA). Although two centers had multiple children colonized with MRSA, genotyping indicated that no transmission had occurred within classrooms. The case-control study did not detect statistically significant risk factors for MRSA colonization. However, MRSA-colonized children were more likely to be nonwhite and to have increased exposure to antibiotics and skin infections in the home. Both CA-MRSA and HA-MRSA strains were found colonizing the nares of children attending CCCs. The low frequency of colonization observed highlights the need for a large multicenter study to determine risk factors for MRSA colonization and subsequent infection in this highly susceptible population.
Insights
Methicillin-resistant Staphylococcus aureus (MRSA) nasal colonization was found in 1.3% of children in child care centers (CCCs). Both community-associated (CA-MRSA) and healthcare-associated (HA-MRSA) strains were present, with no classroom transmission detected.
Area of Science:
- Pediatric infectious diseases
- Microbiology
- Epidemiology
Background:
- Children in child care centers (CCCs) face higher infection risks, including methicillin-resistant Staphylococcus aureus (MRSA).
- Nasal colonization by MRSA is a precursor to infection and linked to increased risk.
- Limited data exists on MRSA nasal colonization prevalence in young children attending CCCs.
Purpose of the Study:
- To determine the frequency of Staphylococcus aureus and MRSA nasal colonization in children attending CCCs.
- To characterize MRSA strains (CA-MRSA vs. HA-MRSA) and investigate potential transmission within classrooms.
- To identify risk factors associated with MRSA colonization in this population.
Main Methods:
- Nasal swabs were collected from 1,163 children across 24 CCCs in North Carolina and Virginia.
- MRSA isolates underwent molecular analysis for SCCmec type, Panton-Valentine leukocidin status, and multilocus sequence type.
- A case-control study was conducted to identify risk factors for MRSA colonization.
Main Results:
- Overall, 18.1% of children were colonized with S. aureus, and 1.3% were colonized with MRSA.
- Molecular analysis revealed 47% of MRSA strains were CA-MRSA and 53% were HA-MRSA.
- No evidence of MRSA transmission within classrooms was found, despite multiple colonized children at two centers. Statistically insignificant risk factors were identified, though non-white ethnicity, antibiotic exposure, and home skin infections were noted.
Conclusions:
- Both CA-MRSA and HA-MRSA strains are found colonizing children in CCCs.
- The low observed MRSA colonization frequency suggests a need for larger multicenter studies.
- Further research is required to elucidate risk factors for MRSA colonization and subsequent infection in this vulnerable pediatric group.
Related Concept Videos
 01:25
Clinical Significance of Antibiotic Resistance
 01:29
Staphylococcal Skin Infections
 01:25
Mechanism of Antibiotic Resistance in MRSA
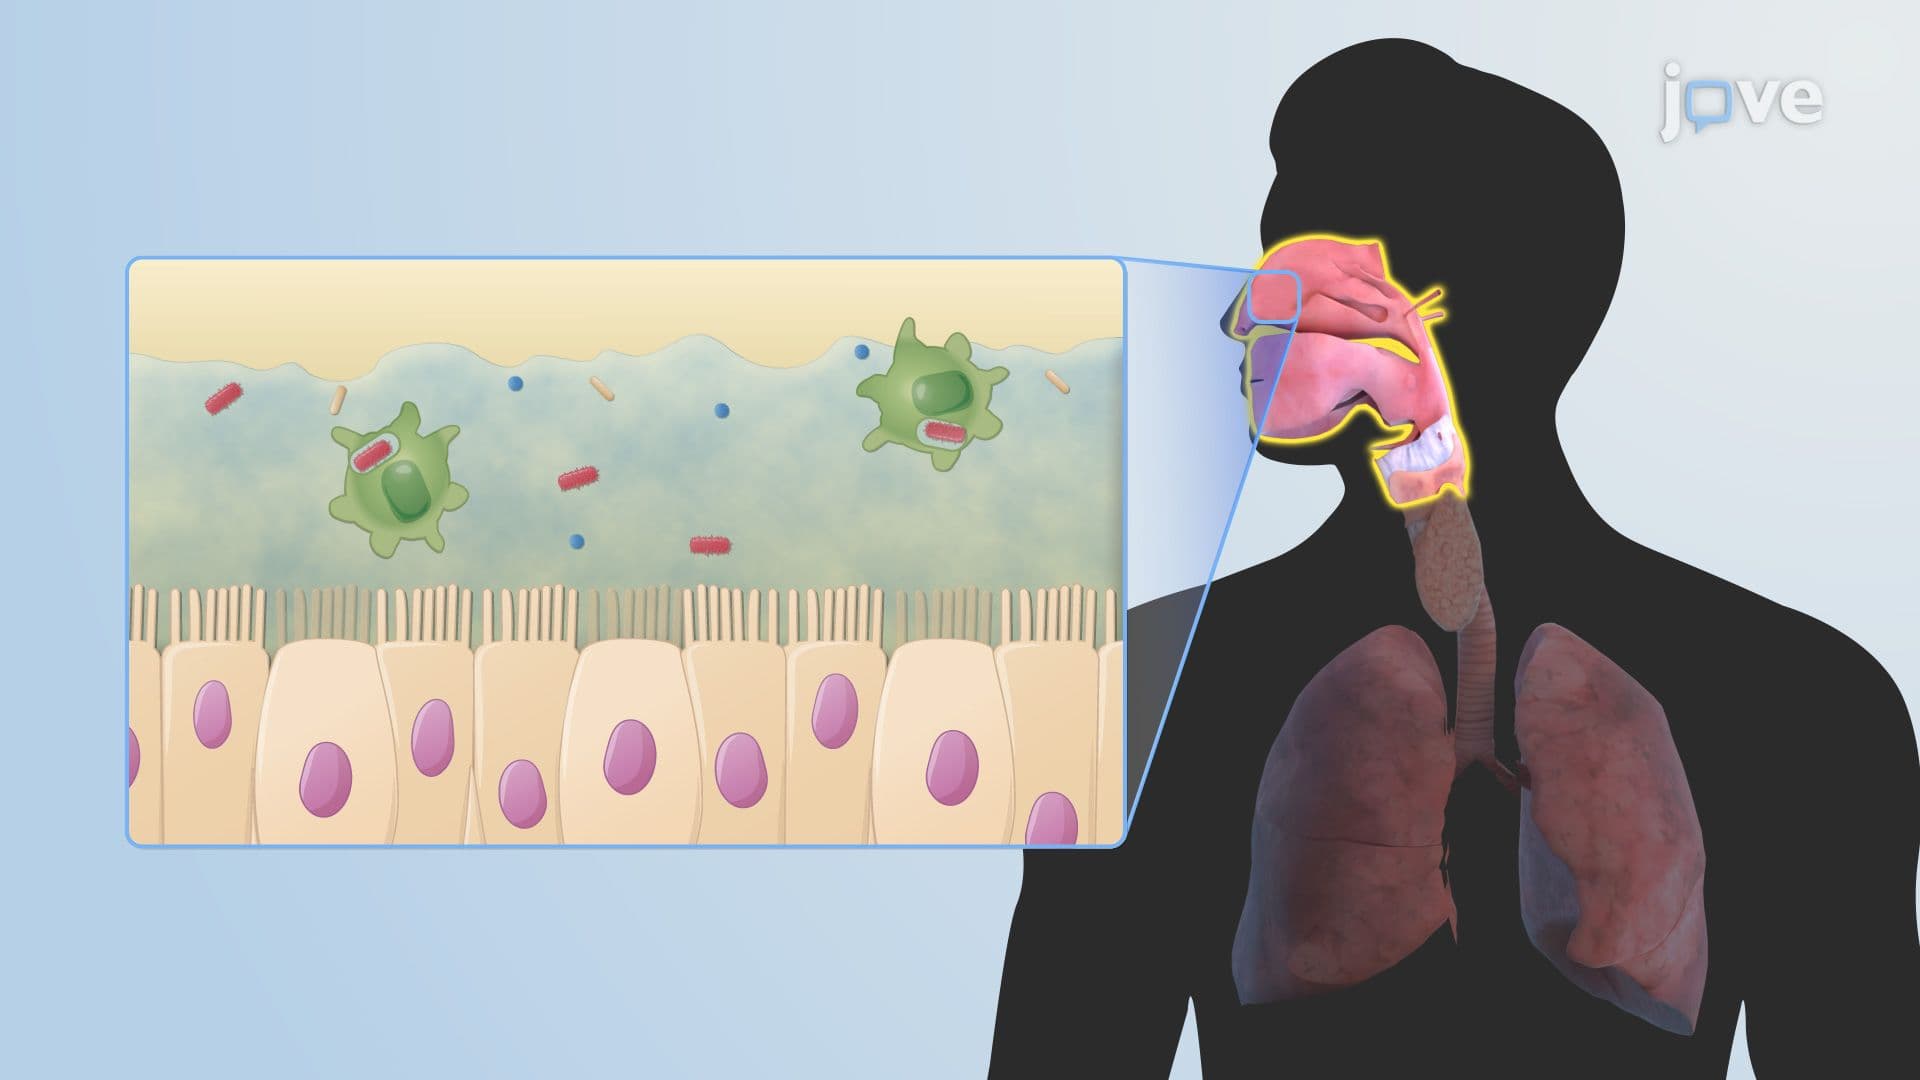 01:29
Microbiota of the Respiratory Tract
 01:28
Development of the Oral Microbiota
 01:26
Factors Affecting the Risk of Infection
The integrity and count of the white blood cells help the body resist pathogens and fight infection. When impaired, it reduces the body's resistance to pathogens. The acidic pH levels of the gastrointestinal, genitourinary tracts, and skin create...