Related Experiment Video
Updated: Jun 5, 2026
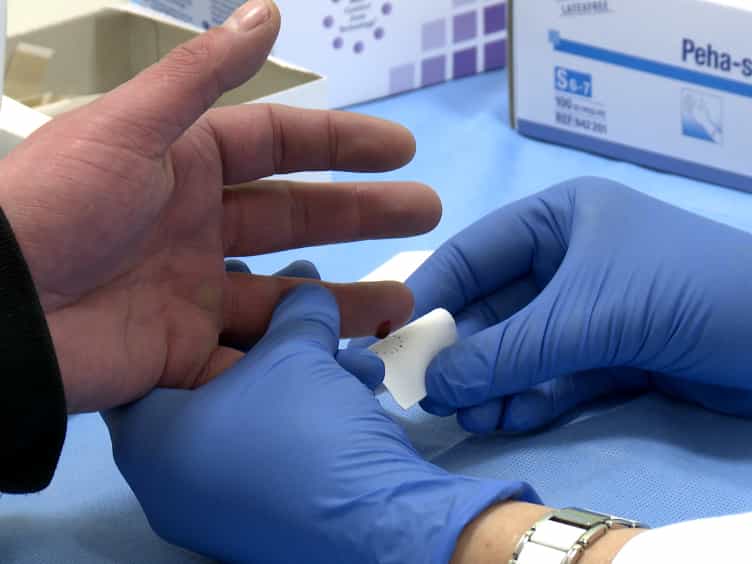

Dried Blood Spots - Preparing and Processing for Use in Immunoassays and in Molecular Techniques
Published on: March 13, 2015
HBV disease: HBsAg carrier and occult B infection reactivation in haematological setting
Carlo Marinone1, Monica Mestriner
1S.C. Medicina Interna 2 - Ospedale San Giovanni Battista - Molinette - C.so Bramante 88, 10100 Torino, Italy. carlo.marinone@tin.it

HBV reactivation in patients with haematological malignancies undergoing chemoimmunotherapy is a serious and frequent complication. This is linked to either the high frequency of inactive HbsAg carriers and occult B infection among oncohaematological patients or the profound immunosuppression caused by high dose chemotherapy, monoclonal antibody therapy or auto- and allo-haematopoietic stem cell (HSC) transplantations. Identifying the patients at risk is mandatory in this clinical setting and prophylaxis with antiviral drugs or close monitoring may reduce and/or eliminate the HBV reactivation risk and the serious consequences. In general, preemptive anti-HBV therapy is more effective than treatment at reactivation. Prompt lamivudine prophylaxis should be given to HBsAg positive patients (inactive carriers) undergoing chemotherapy-immunochemotherapy and continued after cessation of immunosuppression even though long-term lamivudine therapy involves a risk of developing drug resistance. Use of newer anti-HBV agents may be considered. HBV reactivation has also been observed in occult B infection (HBcAb positive) and the optimal management of this group of patients requires special attention.
HBV reactivation in patients with haematological malignancies undergoing chemoimmunotherapy is a serious and frequent complication. This is linked to either the high frequency of inactive HbsAg carriers and occult B infection among oncohaematological patients or the profound immunosuppression caused by high dose chemotherapy, monoclonal antibody therapy or auto- and allo-haematopoietic stem cell (HSC) transplantations. Identifying the patients at risk is mandatory in this clinical setting and prophylaxis with antiviral drugs or close monitoring may reduce and/or eliminate the HBV reactivation risk and the serious consequences. In general, preemptive anti-HBV therapy is more effective than treatment at reactivation. Prompt lamivudine prophylaxis should be given to HBsAg positive patients (inactive carriers) undergoing chemotherapy-immunochemotherapy and continued after cessation of immunosuppression even though long-term lamivudine therapy involves a risk of developing drug resistance. Use of newer anti-HBV agents may be considered. HBV reactivation has also been observed in occult B infection (HBcAb positive) and the optimal management of this group of patients requires special attention.

Related Concept Videos
 01:25
Hepatitis
 01:27
Cytomegalovirus Disease
 01:23
Genital Herpes
 01:28
Herpes
 01:28
Graves' Disease I: Introduction
 01:28
Viral Hepatitis I: Introduction