Related Experiment Video
Updated: Jun 5, 2026
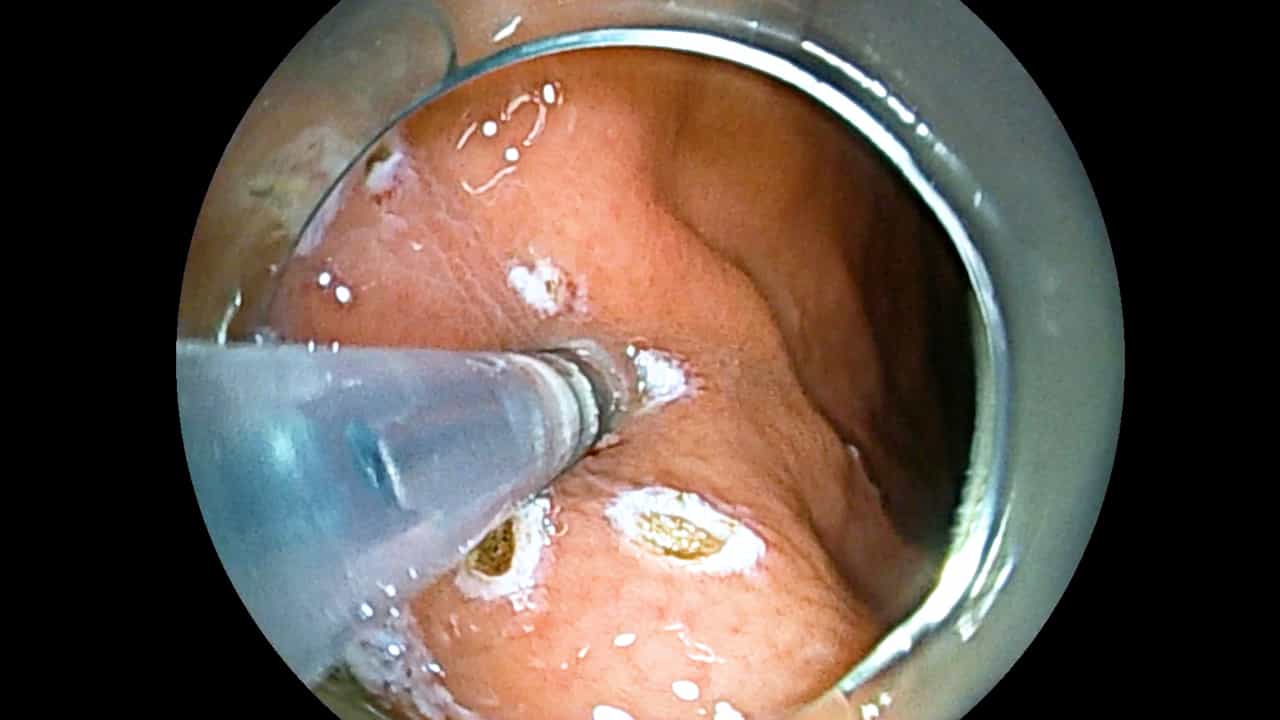

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Low-frequency of bacteremia after endoscopic submucosal dissection of the stomach
Soichi Itaba1, Yoichiro Iboshi, Kazuhiko Nakamura
1Department of Medicine and Bioregulatory Science, Graduate School of Medical Sciences, Kyushu University, Fukuoka, Japan.

Background:
Mainstream therapy for early gastric cancer in Japan has now shifted from endoscopic mucosal resection (EMR) to endoscopic submucosal dissection (ESD). Although bacteremia is reported as being infrequent and transient in gastric EMR, there are no reports of it being investigated in gastric ESD. This study aimed to determine the frequency of bacteremia in gastric ESD.
Patients And Methods:
A prospective study, in 46 consecutive patients who underwent gastric ESD, investigated the frequency of bacteremia before and after the procedure.
Results:
The median time for the total ESD procedure was 105min (range 30-400). The median volume of the submucosal injection was 80ml (range 20-260). The mean size of the resected specimen was 40±9.7mm. Blood cultures obtained before ESD were positive in 4.4% (2/45) of cases. Bacillus subtilis and Bacillus spp. were the isolated microorganisms. Blood cultures obtained 10min after ESD were positive in 4.3% (2/46) of cases; with the same microorganisms being isolated. Blood cultures obtained 3h after ESD were all negative. No signs of sepsis were seen in the two patients with a positive blood culture 10min after ESD.
Conclusions:
The frequency of bacteremia after gastric ESD was low and transient. ESD for gastric lesions is thought to have a low risk of infectious complications; therefore, prophylactic administration of antibiotics may not be warranted.
Related Concept Videos
 01:27
Microbiota of the Stomach and Small Intestine
 01:28
Peptic Ulcer Disease III: Clinical Manifestations and Diagnostic Studies
Few clinical manifestations differentiate gastric ulcers from duodenal ulcers. Distinctions in the location, timing, and pain relief are crucial for healthcare providers in differentiating between gastric and duodenal ulcers during clinical assessments.
 01:26
Gastritis II: Pathophysiology
 01:29
Endoscopic Procedures I: Esophagogastroduodenoscopy
During an EGD, the endoscope can be used to:
 01:50
What is Monogastric Digestion?
 01:25
Peptic Ulcer Disease III: Clinical Manifestations and Complications