Related Experiment Videos
Persistence of acute rheumatic fever in a tertiary children's hospital
Michael T Smith1, David Lester-Smith, Yvonne Zurynski
1The Australian Paediatric Surveillance Unit, The Children's Hospital at Westmead, Westmead, New South Wales, Australia. apsu@chw.edu.au

Insights
Acute rheumatic fever (ARF) disproportionately affects disadvantaged children in Sydney, particularly those from Pacific Islander and Aboriginal and Torres Strait Islander backgrounds. Early diagnosis and effective secondary prophylaxis are crucial for preventing rheumatic heart disease (RHD).
Area of Science:
- Pediatrics
- Cardiology
- Public Health
Background:
- Acute rheumatic fever (ARF) is a significant cause of acquired heart disease in children globally.
- Rheumatic heart disease (RHD) prevention strategies rely on early diagnosis and management of ARF.
- Socioeconomic and ethnic disparities are known risk factors for ARF.
Purpose of the Study:
- To identify and describe children admitted with ARF to a Sydney tertiary pediatric hospital over nine years.
- To analyze demographic, clinical characteristics, management, and short-term outcomes of pediatric ARF cases.
- To document delays in diagnosis, ARF recurrence, and secondary prophylaxis use.
Main Methods:
- Retrospective medical record review of children under 15 years admitted with ARF (ICD-10 I0.0-I09.9) between 2000-2008.
- Inclusion criteria: adherence to National Heart Foundation of Australia diagnostic criteria for ARF.
- Data collected included demographics, clinical presentation, management, and outcomes.
Main Results:
- Twenty-six children met ARF criteria; median age 11.5 years, 58% male.
- High representation of Pacific Islander (38%) and Aboriginal and Torres Strait Islander (19%) children.
- Most lived in disadvantaged areas (69%); 81% had carditis, 15% Sydenham's chorea.
- 81% experienced diagnostic delays; 50% received oral rather than intramuscular penicillin prophylaxis.
Conclusions:
- Pediatric ARF in Sydney predominantly affects children from socioeconomically disadvantaged backgrounds, with over-representation of Pacific Islander and ATSI children.
- Timely diagnosis and appropriate secondary prophylaxis delivery are essential for mitigating RHD.
- Addressing socioeconomic and ethnic disparities is critical for ARF and RHD prevention efforts.
Aim:
To identify and describe all children admitted with acute rheumatic fever (ARF) to a tertiary paediatric hospital in Sydney over a 9-year period and to describe their demographic and clinical characteristics, management and short-term outcomes. Delays in diagnosis, recurrence of ARF and use of secondary prophylaxis were also documented.
Methods:
Retrospective review of medical records for children aged < 15 years admitted to the Children's Hospital at Westmead, Sydney, with ARF (International Classification of Diseases (ICD)-10 classification I0.0-109.9) during 2000-2008. Only cases meeting the National Heart Foundation of Australia diagnostic criteria for ARF were included.
Results:
Twenty-six children met the National Heart Foundation of Australia criteria for ARF. The median age was 11.5 years (range 5.8-14.6) and 15 (58%) were male. Ten (38%) identified as Pacific Islander, and 5 (19%) as Aboriginal and Torres Strait Islander (ATSI). Most (n= 20, 77%) lived in suburban Sydney, and 69% were classified in the two most disadvantaged quintiles on the Index of Relative Socioeconomic Disadvantage and Advantage. Four (15%) had Sydenham's chorea, and 81% had carditis (mitral and/or aortic regurgitation). Six (23%) children had previous ARF. Antibiotic prophylaxis to prevent recurrent ARF was prescribed in all cases, but 50% received oral penicillin, rather than by intramuscular injection. Barriers to timely diagnosis were identified in 81%, including delayed presentation and delayed referral.
Conclusion:
Most children presenting to the hospital with ARF lived in disadvantaged areas of Sydney. Pacific Islander and Aboriginal and Torres Strait Islander children were over-represented. Mitigation of RHD requires early identification of ARF and appropriate delivery of secondary prophylaxis.
Related Concept Videos
 01:23
Rheumatic Heart Disease I: Introduction
 01:22
Rheumatic Heart Disease II: Clinical Manifestations and Diagnostic Studies
 01:21
Rheumatic Heart Disease III: Medical Management
 01:30
Tonsillitis I: Introduction
Etiology
Three primary contributing factors have been identified.
 01:30
Acute Pharyngitis
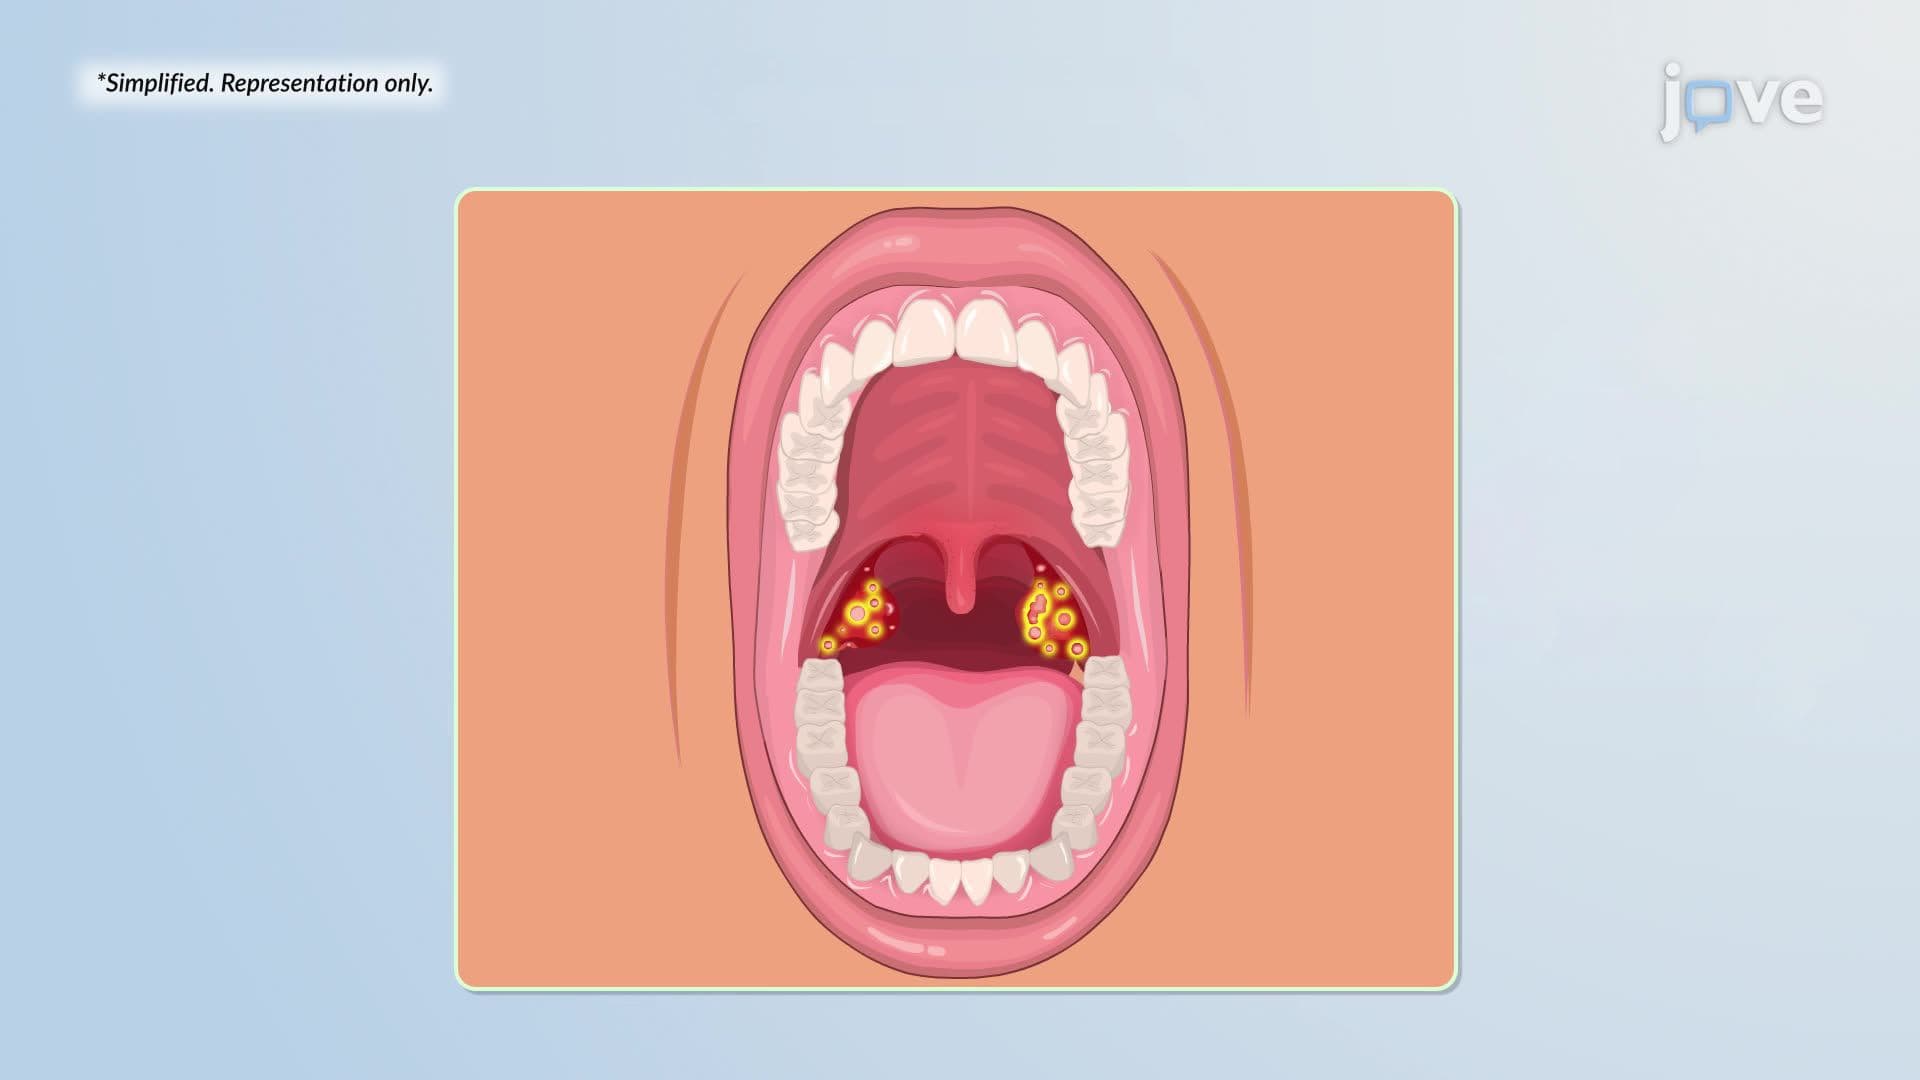
Acute pharyngitis is the inflammation of the back of the throat (pharynx), commonly resulting in a sore throat. It is a frequently encountered condition that prompts individuals to seek medical advice.
Classification
Acute pharyngitis can be categorized based on its underlying cause:
 01:27
Streptococcal Pharyngitis