Related Experiment Video
Updated: Jun 5, 2026


A Competent Hepatocyte Model Examining Hepatitis B Virus Entry through Sodium Taurocholate Cotransporting Polypeptide as a Therapeutic Target
Published on: May 10, 2022
Treatment of HBeAg-negative chronic hepatitis B patients with nucleos(t)ide analogues
12nd Department of Internal Medicine, Athens University Medical School, Hippokration General Hospital of Athens, Athens, Greece. gepapath@med.uoa.gr

Abstract:
Current agents used in the treatment of chronic hepatitis B (CHB) can be classified into interferons-α (IFN-α: standard or pegylated) and nucleos(t)ide analogues (NUCs). NUCs are now used in most CHB patients for several reasons. They can be given to all CHB patients, even those with contraindications to IFN-α. NUCs are more convenient to use (one oral tablet daily) than IFN-α (subcutaneous injections) and are well tolerated with a good safety profile, while IFN-α has frequent and potentially severe side effects and worsens the patient's quality of life. All NUCs are potent anti-hepatitis B virus agents (all but adefovir are more potent than IFN-α) with entecavir(ETV) and tenofovir offering the highest potency and most importantly minimal to negligible risk of resistance during long-term monotherapy [corrected]. Prolongation of entecavir or tenofovir monotherapy maintains and slightly increases the initially high virological remission rates (67-76% of HBeAg-positive and 90-93% of HBeAg-negative patients) and this is expected to result in improved long-term outcomes. The need for long-term, perhaps indefinite, treatment is the main limitation of NUCs and the finite duration (48 weeks) the main advantage of IFN-α. However, only a minority of IFN-α-treated patients achieve durable sustained off-treatment responses (HBeAg-positive: 30-35%, HBeAg-negative: 20-25%), while NUCs may be safely discontinued in HBeAg-positive patients with stable HBeAg seroconversion. Because there will always be concerns for safety and family planning issues with long-term therapy, NUCs should be used judiciously and should not be prescribed in young CHB patients with mild liver disease.


Related Concept Videos
 01:22
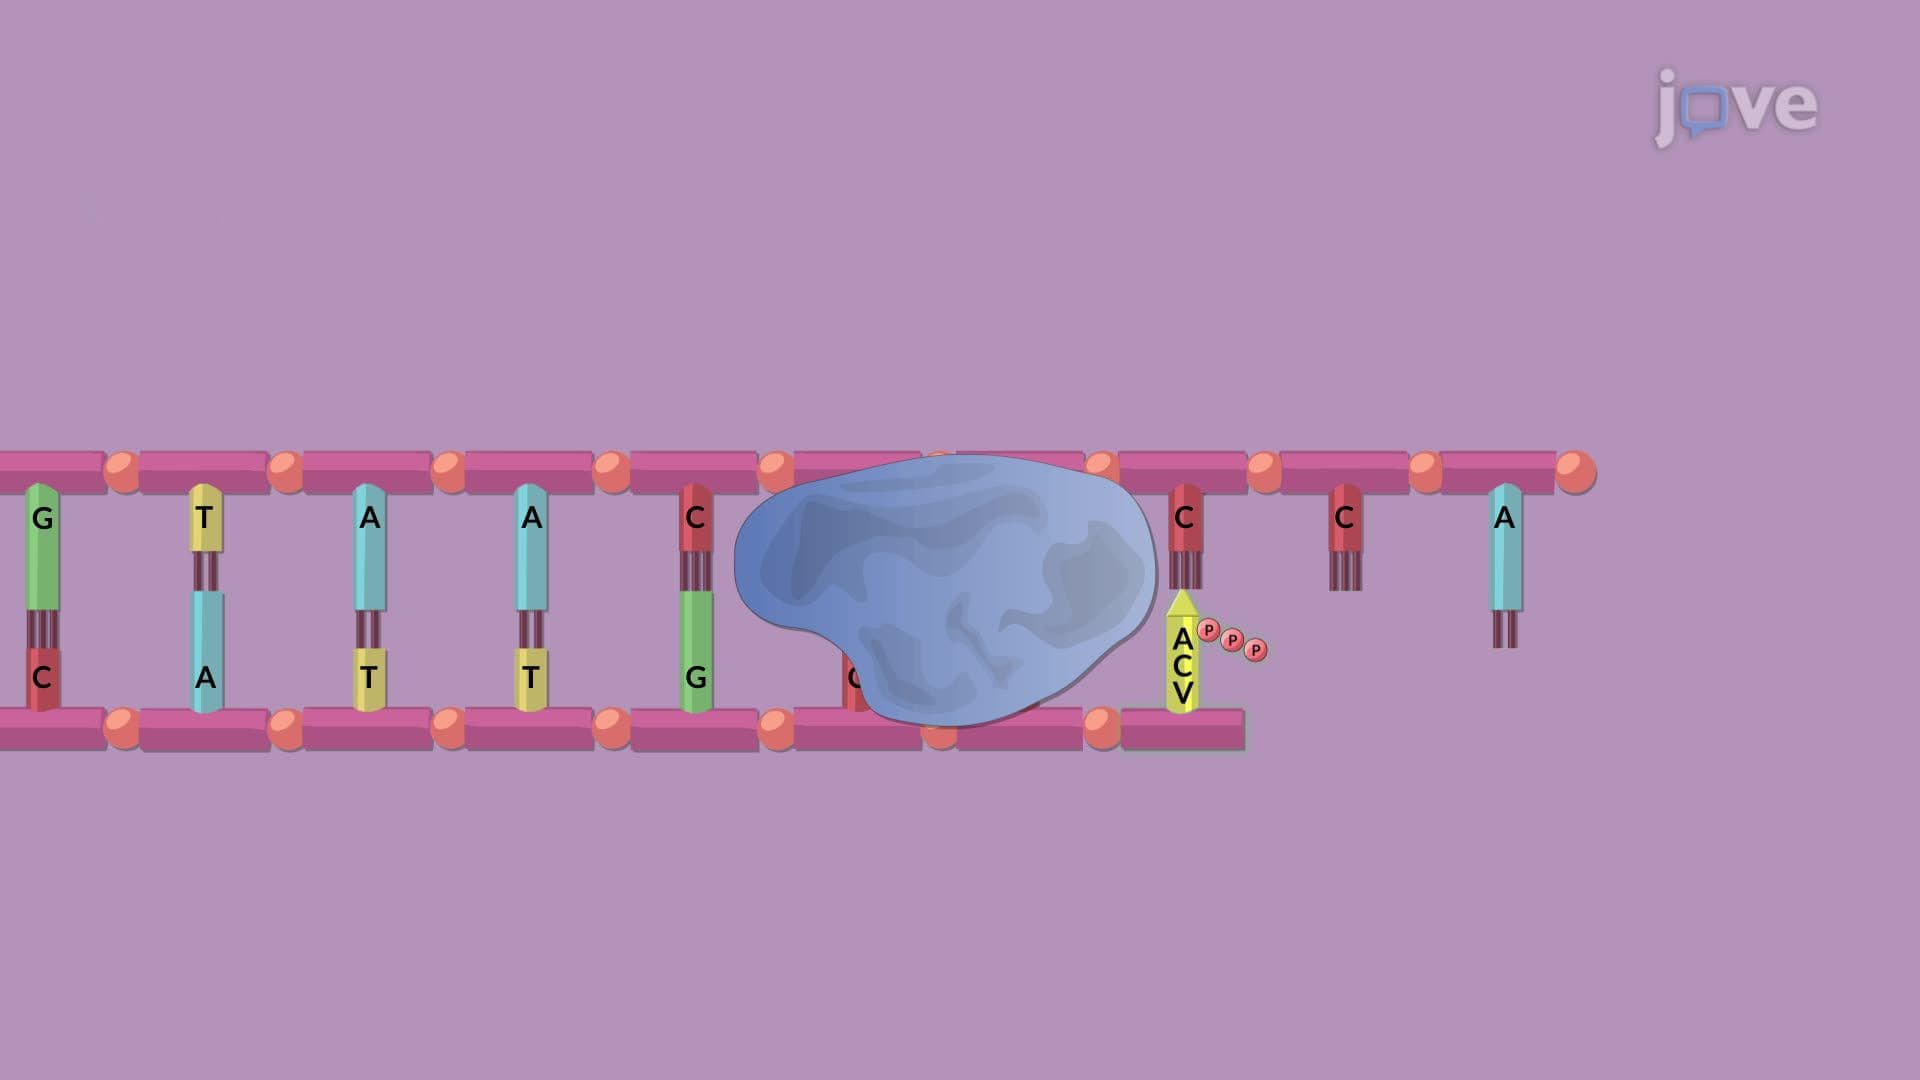
Antiviral Nucleoside Inhibitors
 01:25
Hepatitis
 01:29
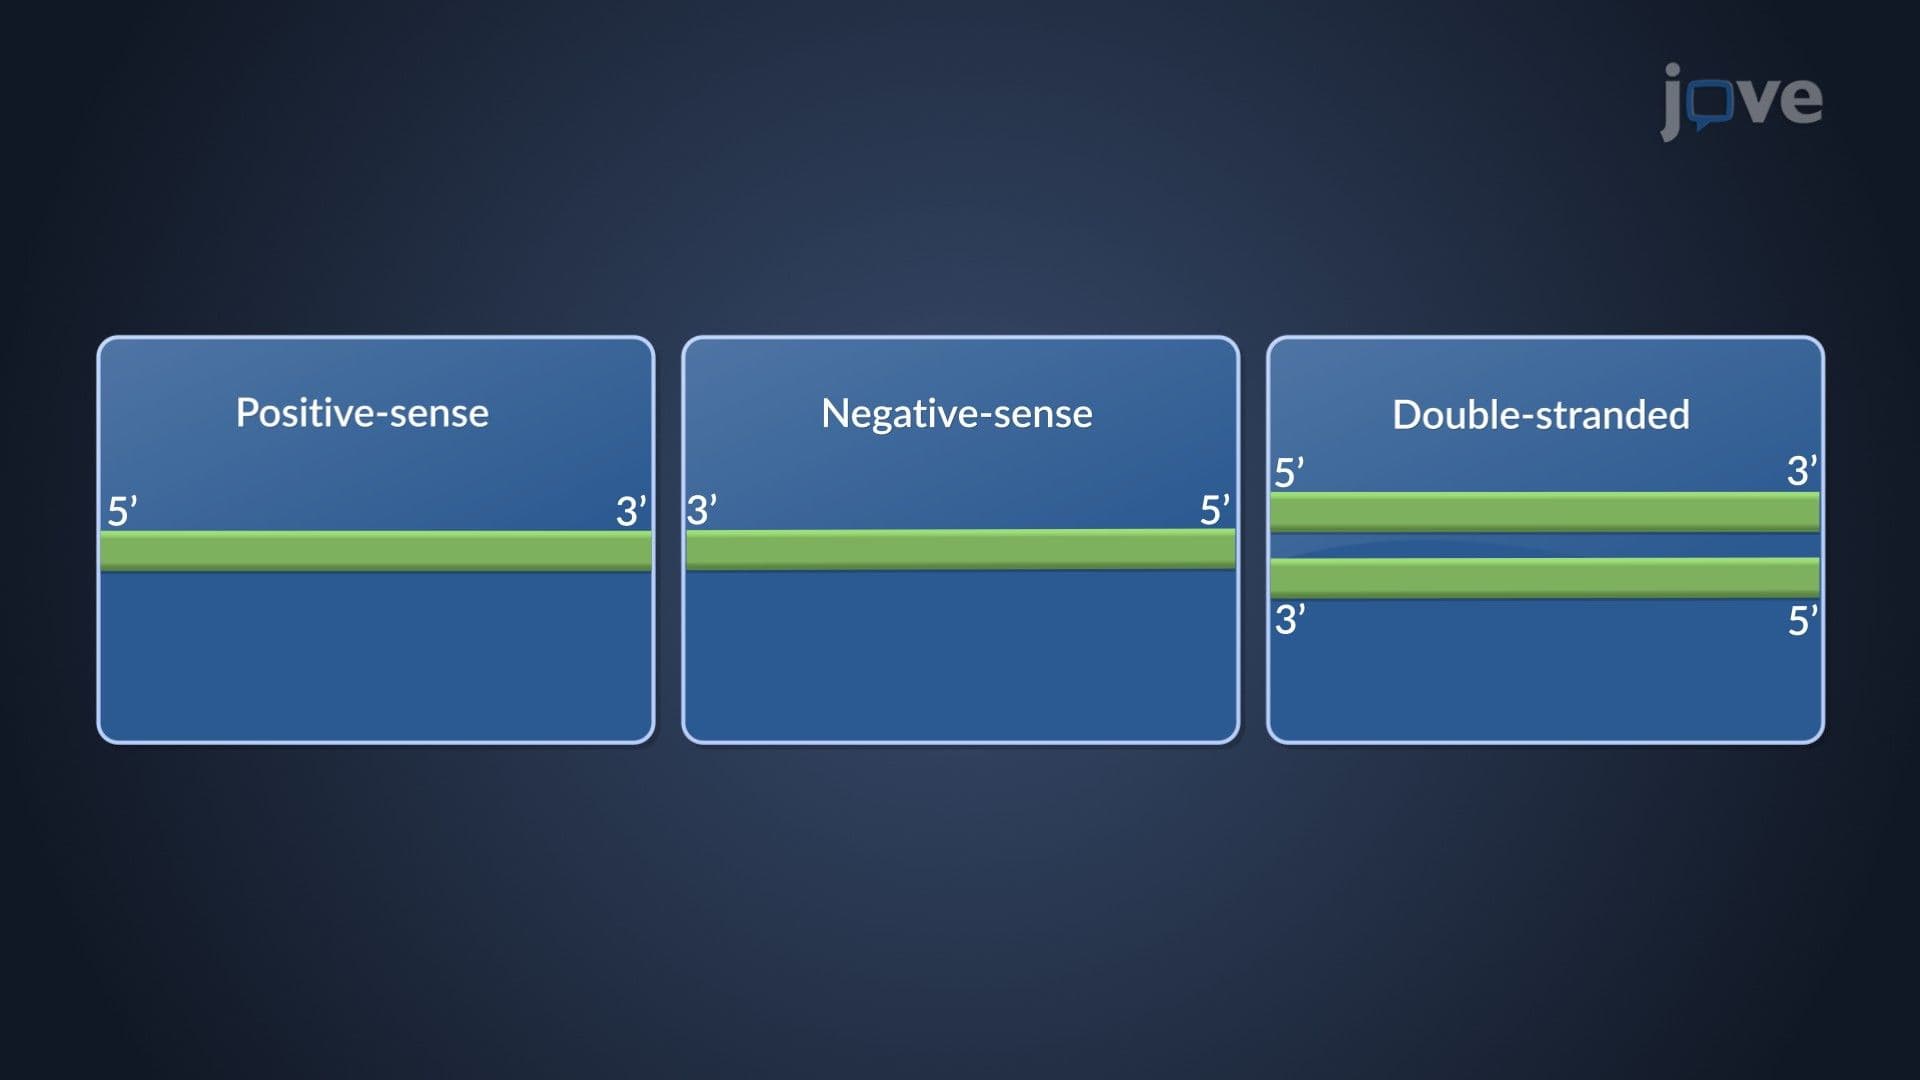
Viruses with RNA Genomes
 01:10
Retrovirus Life Cycles
 01:30
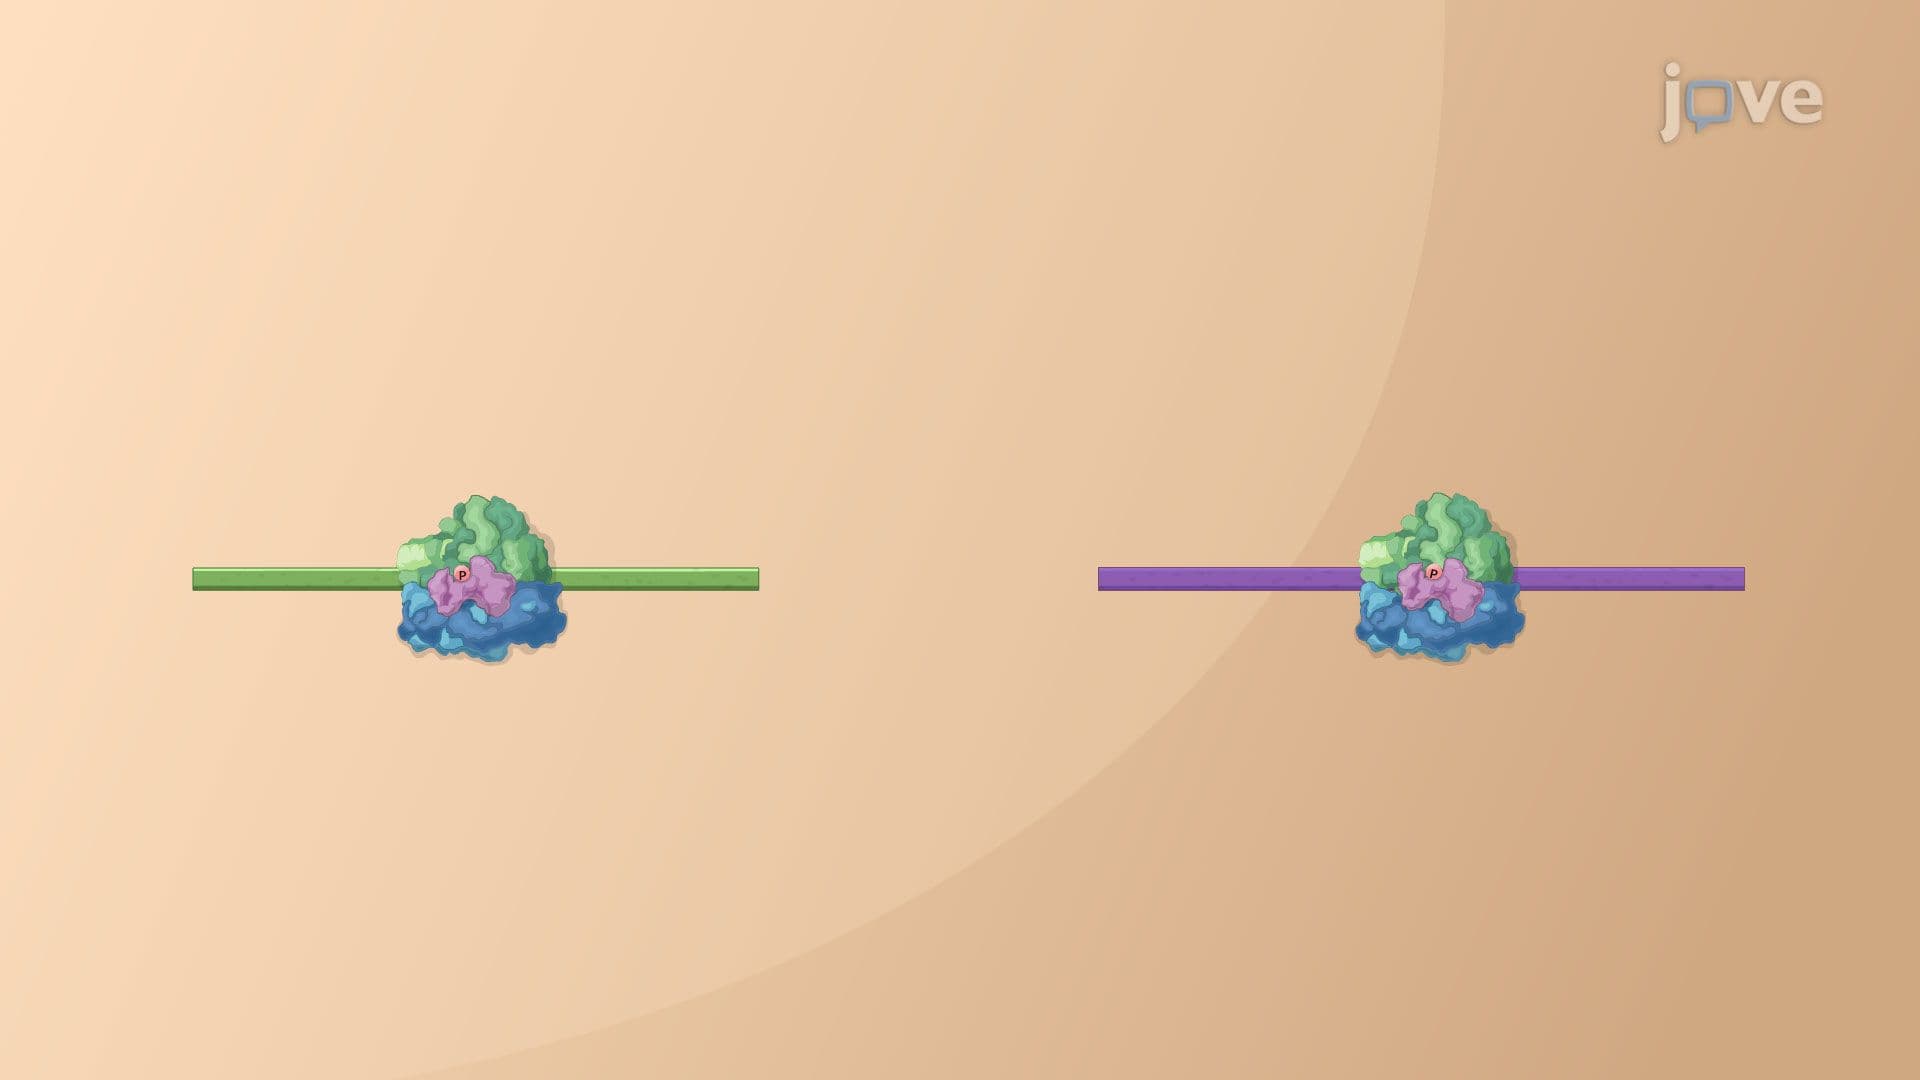
Inhibitors of Viral Protein Synthesis
 01:27
Pharmacogenetics of Phase II Enzymes: N-acetyltransferase, Thiopurine S-methyltransferase, UDP-glucuronosyltransferase