Related Experiment Video
Updated: Jun 5, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
A case of myxedema coma caused by isolated thyrotropin stimulating hormone deficiency and Hashimoto's thyroiditis
Keiji Iida1, Yasuhisa Hino, Takeshi Ohara
1Division of Diabetes and Endocrinology, Hyogo Prefectural Kakogawa Medical Center, Kakogawa, Japan. iida@hp.pref.hyogo.jp

Abstract:
Myxedema coma (MC) is a rare, but often fatal endocrine emergency. The majority of cases that occur in elderly women with long-standing primary hypothyroidism are caused by particular triggers. Conversely, MC of central origin is extremely rare. Here, we report a case of MC with both central and primary origins. A 56-year-old woman was transferred to our hospital due to loss of consciousness; a chest x-ray demonstrated severe cardiomegaly. Low body temperature, bradycardia, and pericardial effusion suggested the presence of hypothyroidism. Endocrinological examination revealed undetectable levels of serum free thyroxine (T(4)) and free triiodothyronine (T(3)), whereas serum thyroid-stimulating hormone (TSH) levels were not elevated. The woman's serum anti-thyroid peroxidase antibody and anti-thyroglobulin antibody tests were positive, indicating that she had Hashimoto's thyroiditis. Provocative tests to the anterior pituitary revealed that she had TSH and growth hormone (GH) deficiency; however, GH levels were restored after supplementation with levothyroxine for 5 months. This was not only a rare case of MC with TSH deficiency and Hashimoto's thyroiditis; the patient also developed severe osteoporosis and possessed transient elevated levels of serum carcinoembryonic antigen (CEA). This atypical case may suggest the role of anterior pituitary hormone deficiencies, as well as hypothyroidism, in the regulation of bone metabolism.
Related Concept Videos
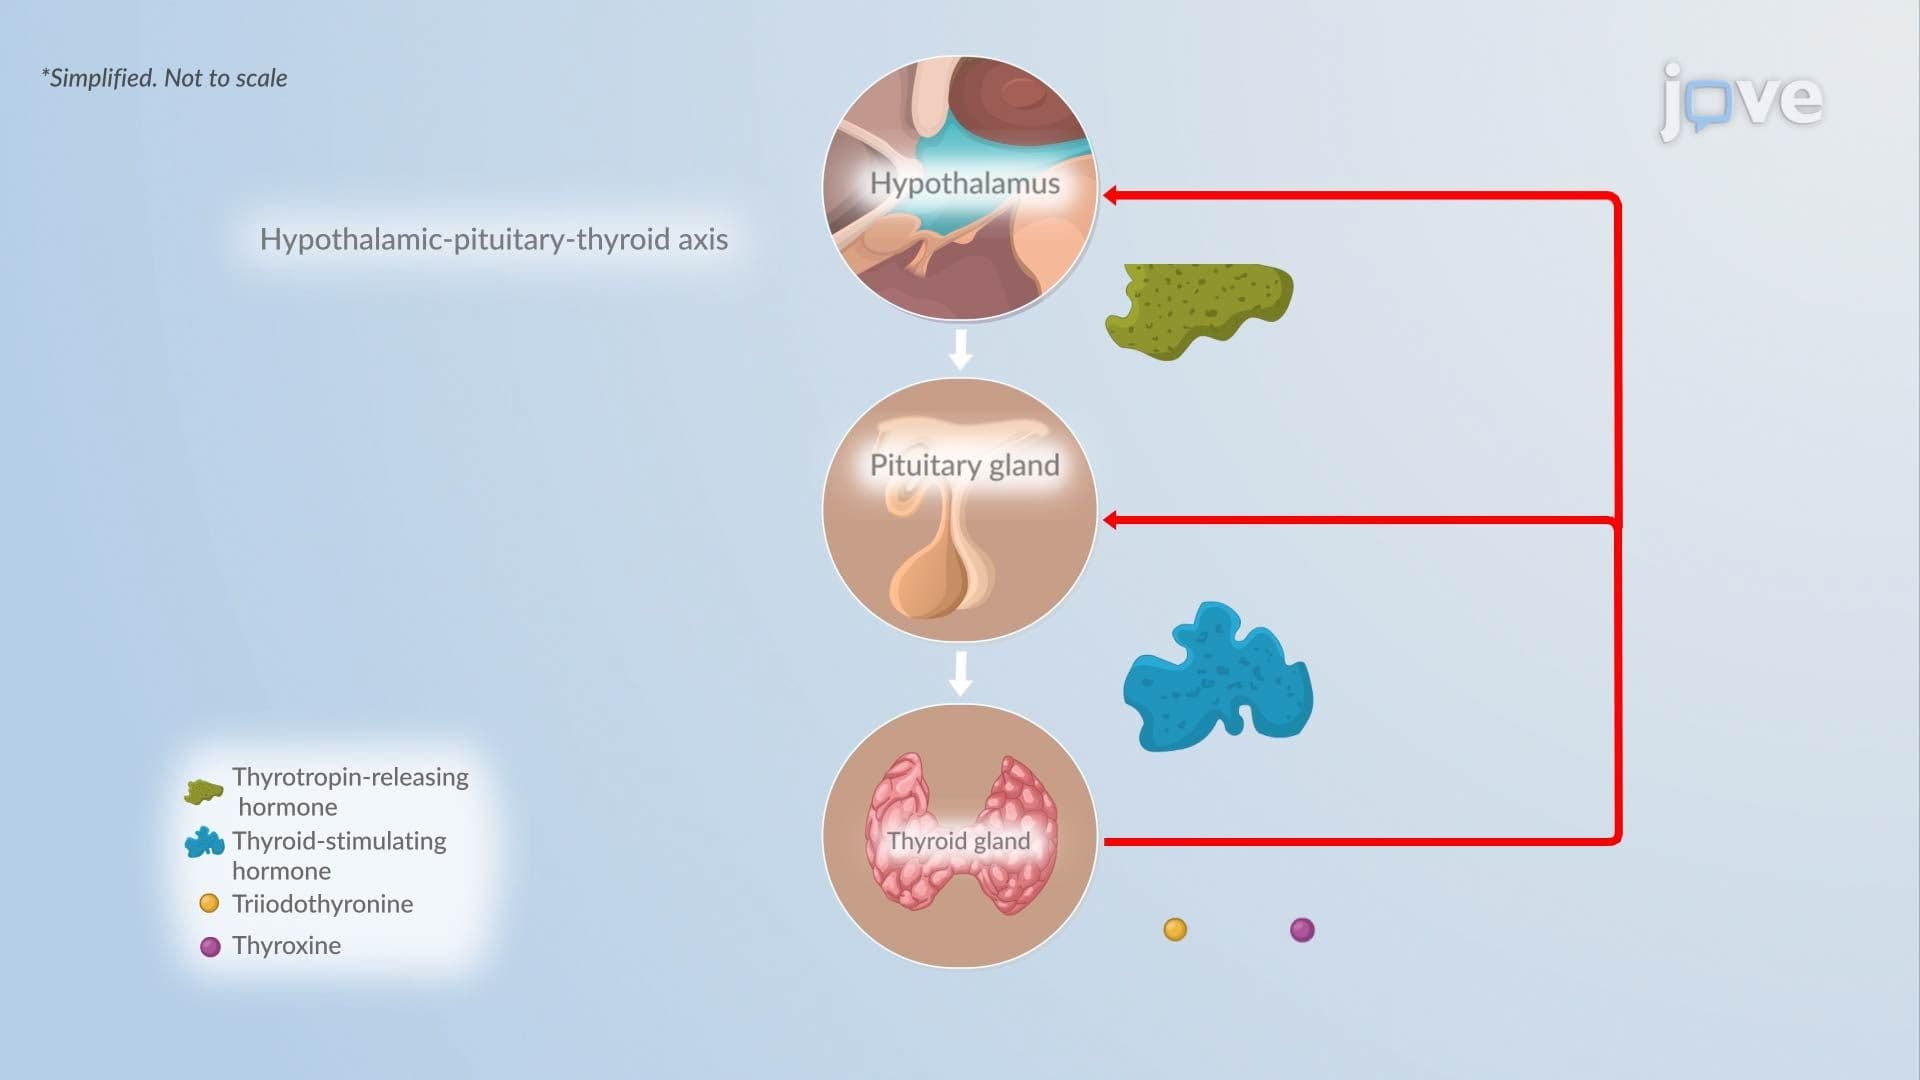 01:25
Hyperthyroidism I: Introduction
 01:28
Graves' Disease I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
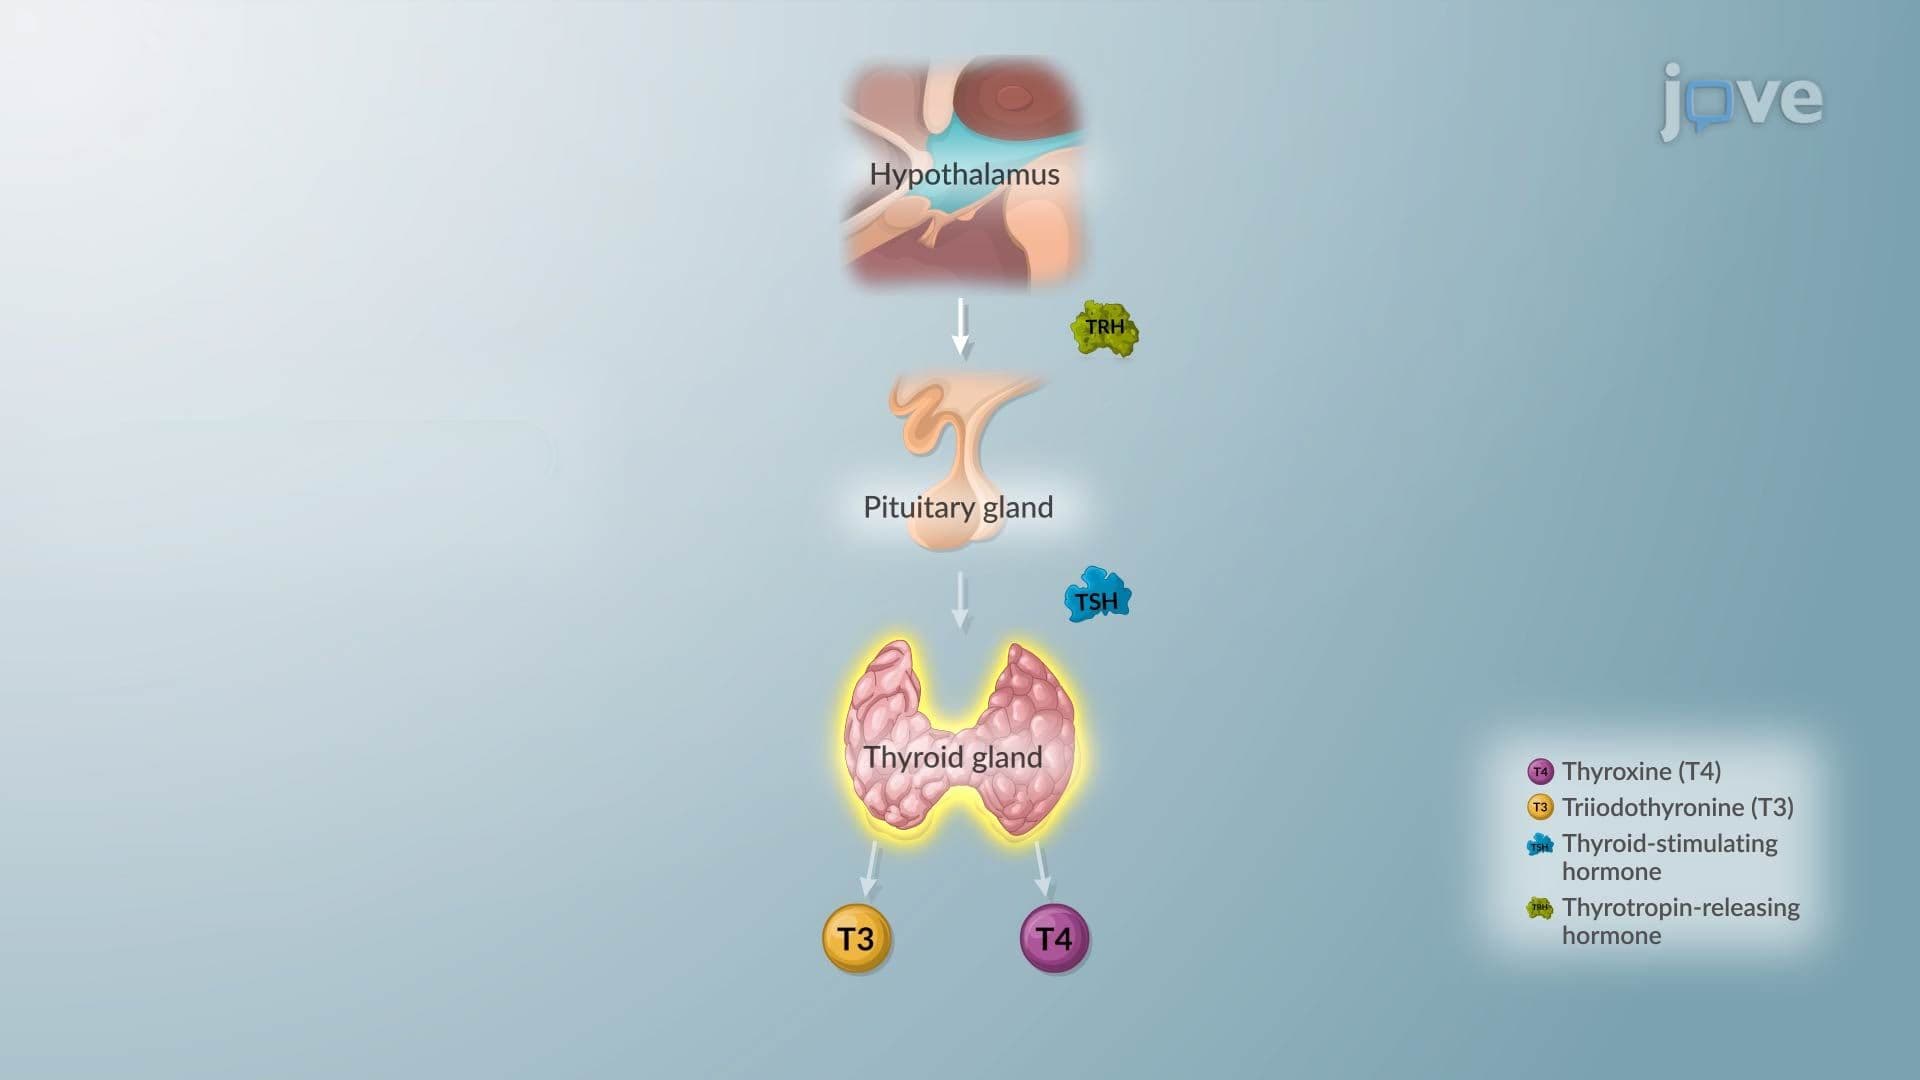 01:23
Hypothyroidism II: Pathophysiology
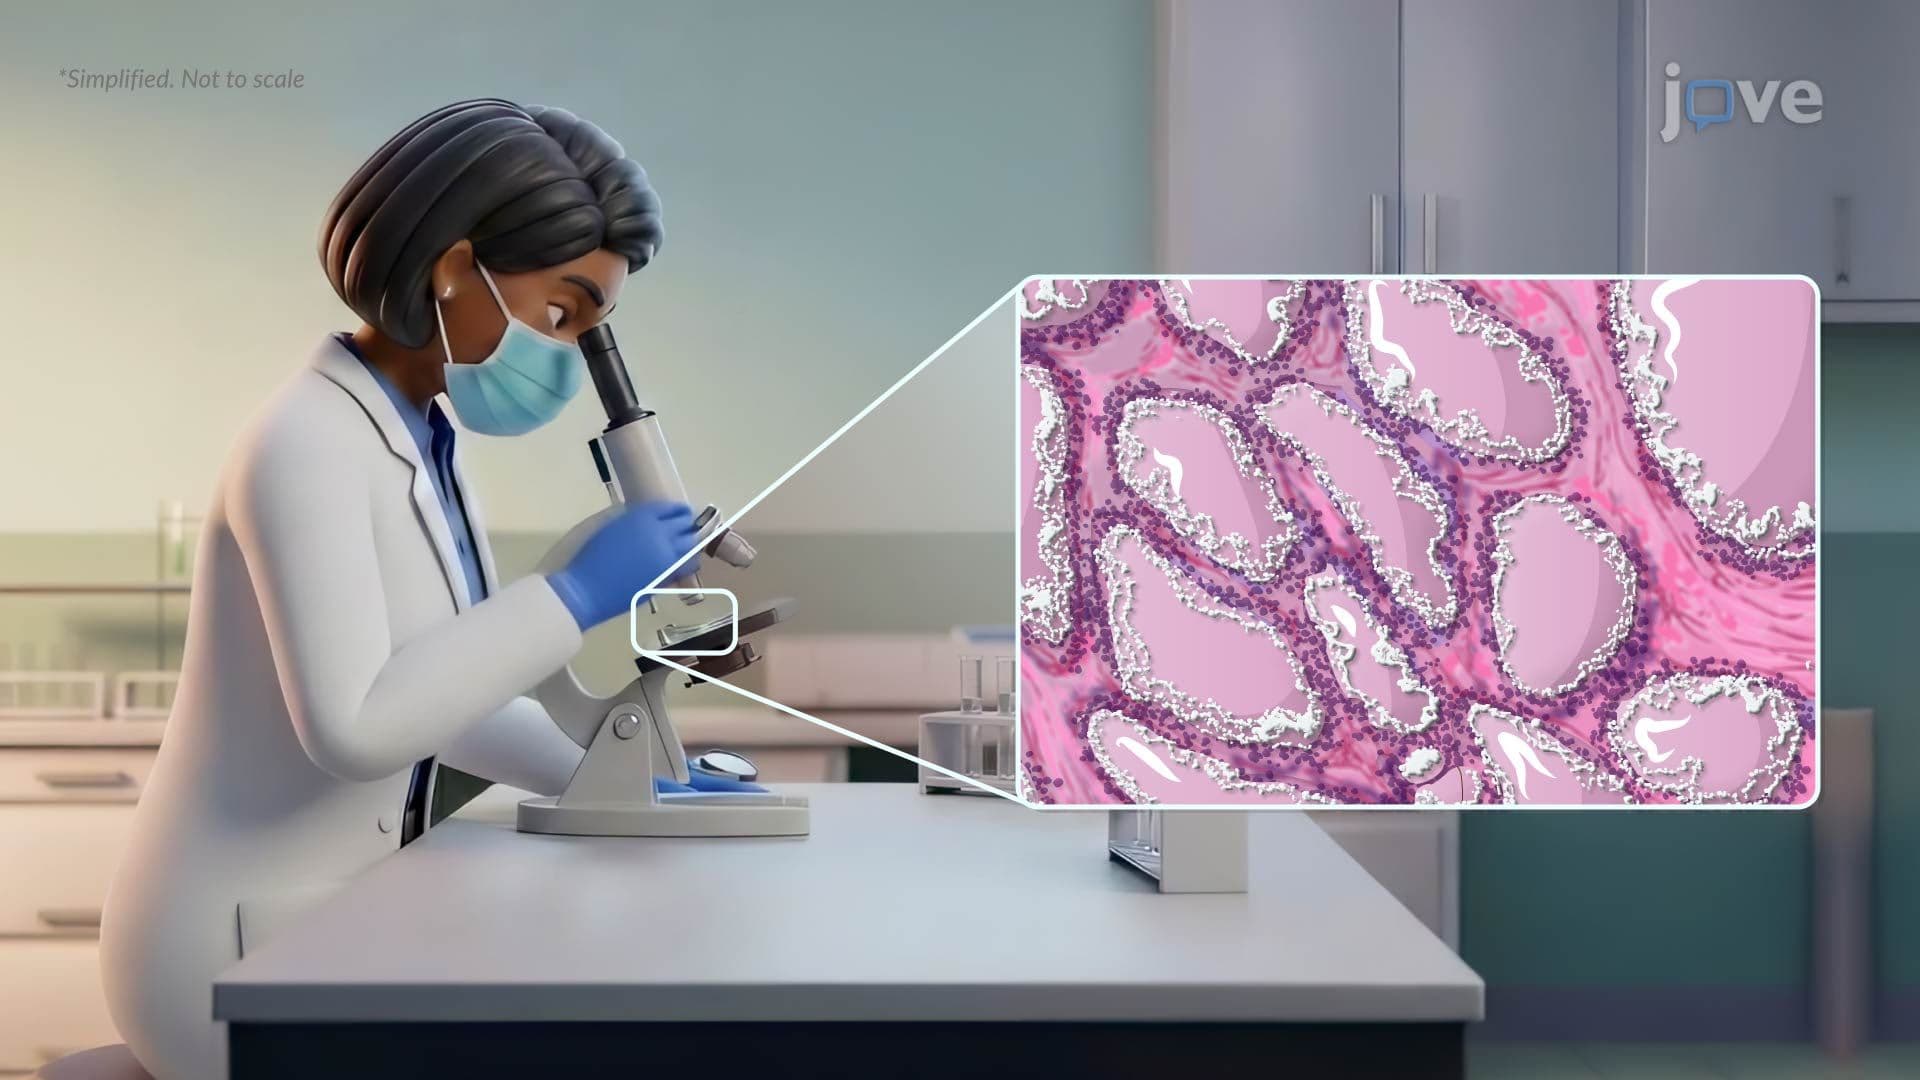 01:24
Graves Disease II: Pathophysiology
 01:27
Goiter