Spasticity mechanisms - for the clinician
Related Experiment Video
Updated: Jun 5, 2026
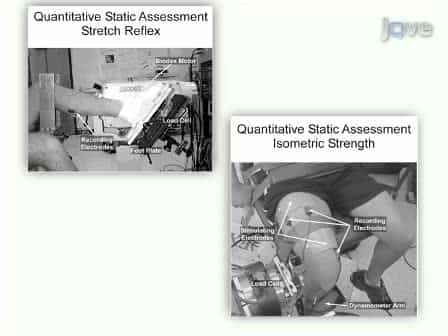
Methods to Quantify Pharmacologically Induced Alterations in Motor Function in Human Incomplete SCI
Published on: April 18, 2011
Angshuman Mukherjee1, Ambar Chakravarty
1Department of Neurology, Vivekananda Institute of Medical Sciences Kolkata, India.

Abstract:
Spasticity, a classical clinical manifestation of an upper motor neuron lesion, has been traditionally and physiologically defined as a velocity dependent increase in muscle tone caused by the increased excitability of the muscle stretch reflex. Clinically spasticity manifests as an increased resistance offered by muscles to passive stretching (lengthening) and is often associated with other commonly observed phenomenon like clasp-knife phenomenon, increased tendon reflexes, clonus, and flexor and extensor spasms. The key to the increased excitability of the muscle stretch reflex (muscle tone) is the abnormal activity of muscle spindles which have an intricate relation with the innervations of the extrafusal muscle fibers at the spinal level (feed-back and feed-forward circuits) which are under influence of the supraspinal pathways (inhibitory and facilitatory). The reflex hyperexcitability develops over variable period of time following the primary lesion (brain or spinal cord) and involves adaptation in spinal neuronal circuitries caudal to the lesion. It is highly likely that in humans, reduction of spinal inhibitory mechanisms (in particular that of disynaptic reciprocal inhibition) is involved. While simply speaking the increased muscle stretch reflex may be assumed to be due to an altered balance between the innervations of intra and extrafusal fibers in a muscle caused by loss of inhibitory supraspinal control, the delayed onset after lesion and the frequent reduction in reflex excitability over time, suggest plastic changes in the central nervous system following brain or spinal lesion. It seems highly likely that multiple mechanisms are operative in causation of human spasticity, many of which still remain to be fully elucidated. This will be apparent from the variable mechanisms of actions of anti-spasticity agents used in clinical practice.

Related Concept Videos
 01:12
Alterations in Muscle Tone ll
 01:29
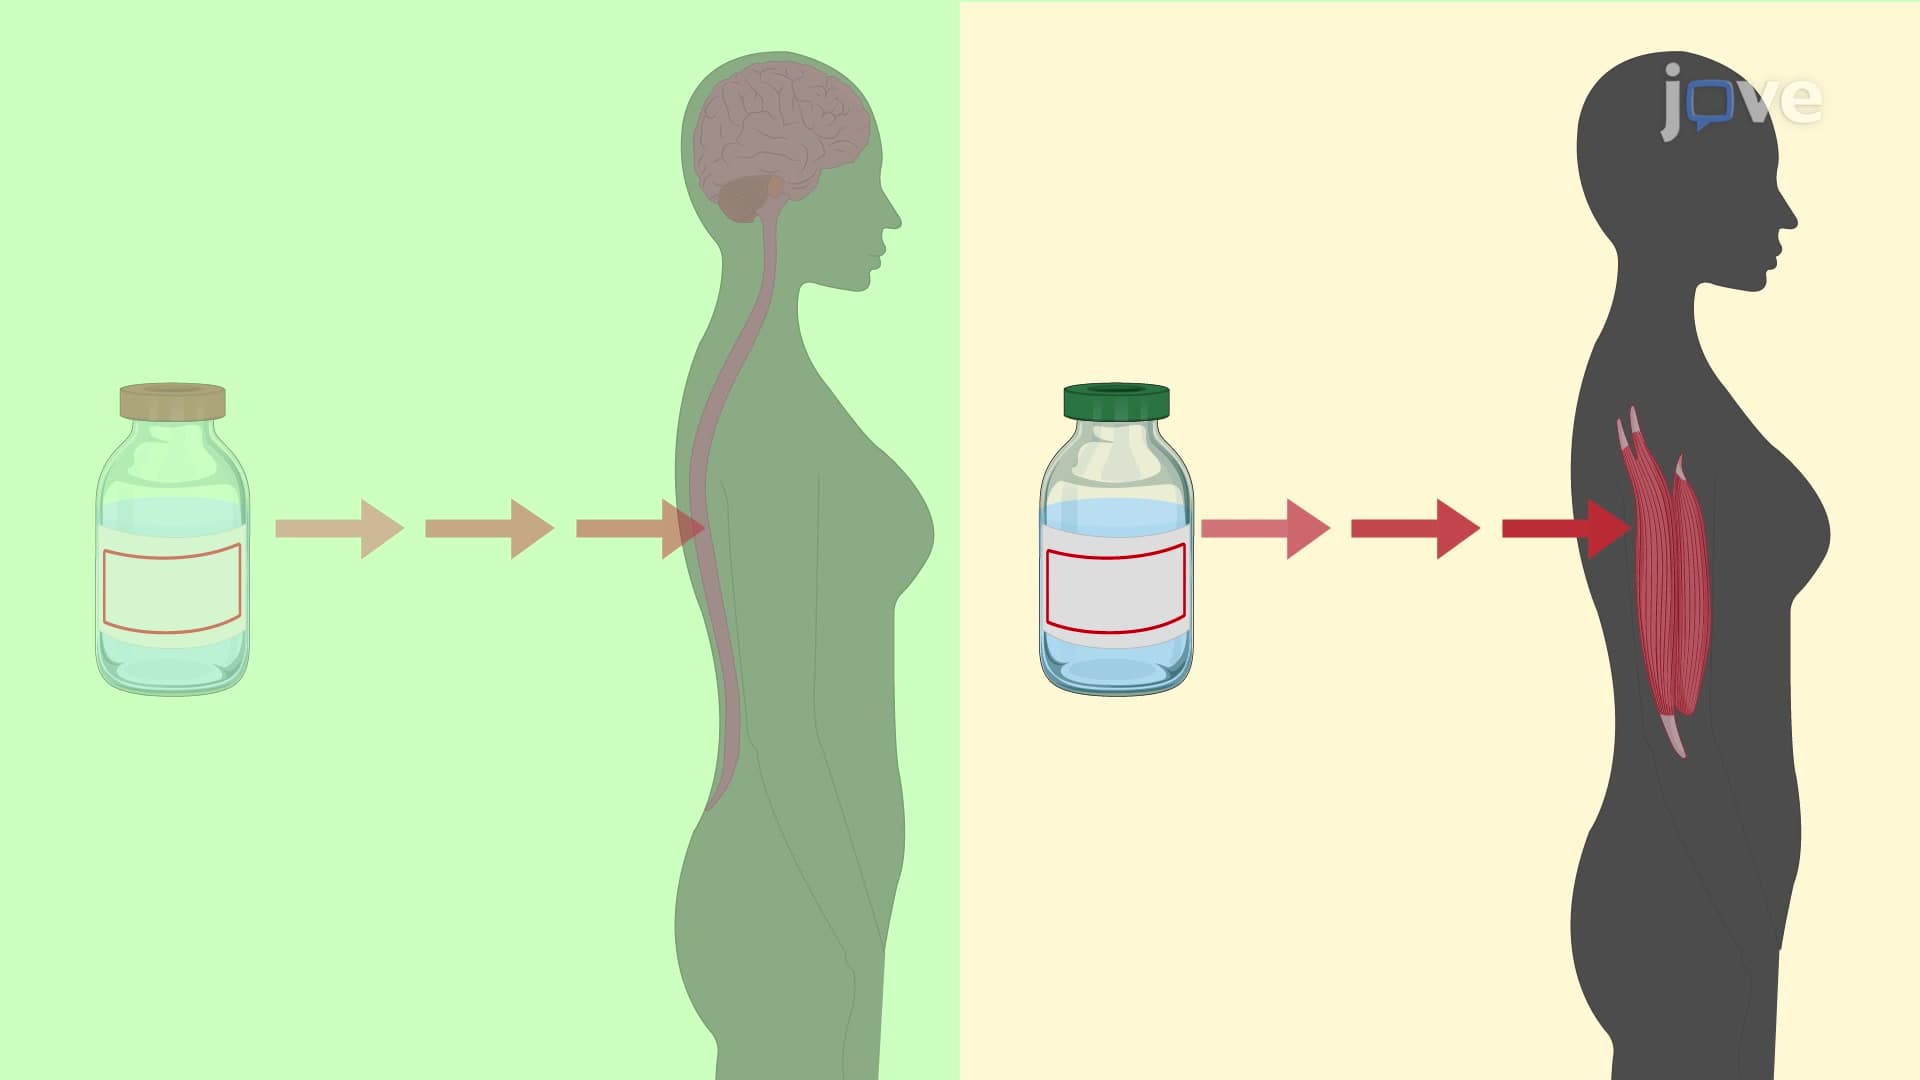
Spasmolytic Agents: Chemical Classification
A major class of centrally acting spasmolytics is the α2-agonist, such as tizanidine. These drugs bind to α2-adrenoceptors, inhibiting the release of the excitatory neurotransmitter glutamate. They also promote...
 01:11
Alterations in Muscle Tone lll
 01:28
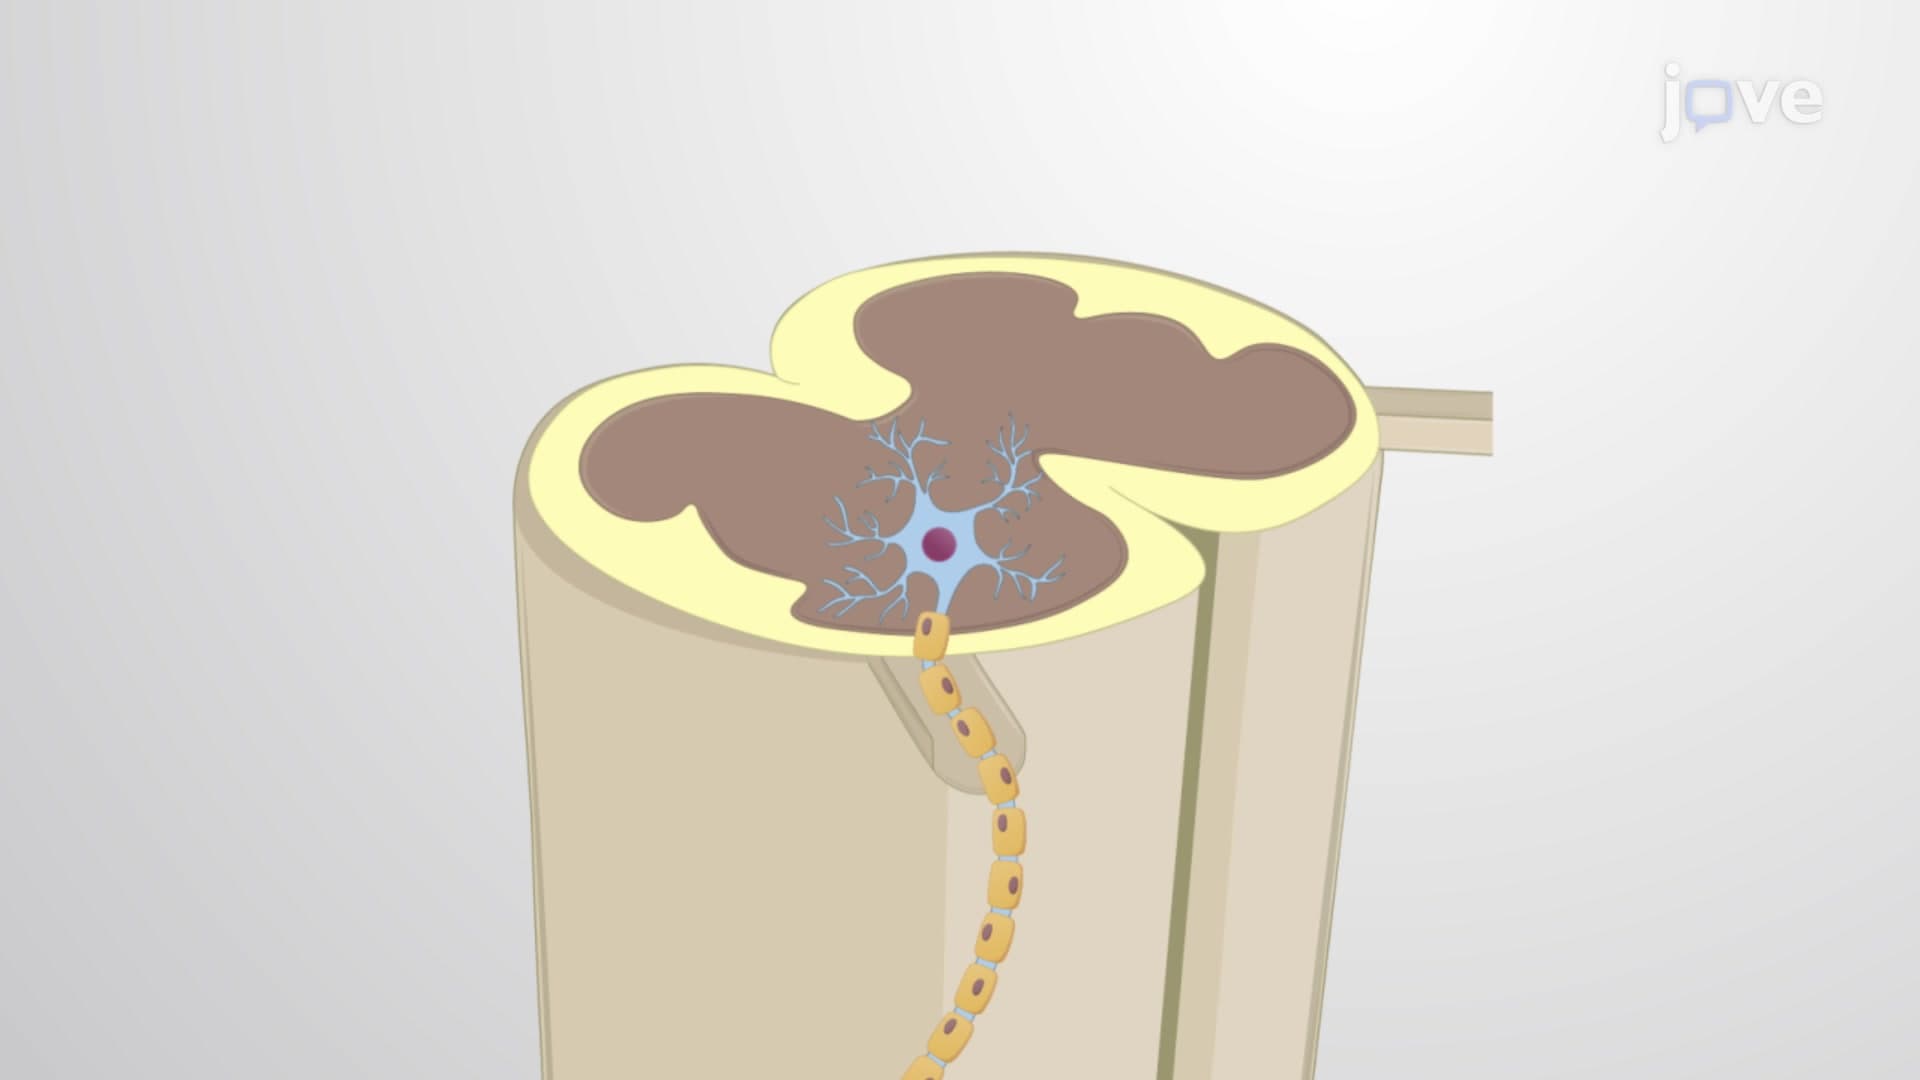
Classification of Skeletal Muscle Relaxants
Peripherally acting skeletal muscle relaxants interfere with the neurotransmission at the neuromuscular end plate to induce paralysis during...
 01:31
Skeletal Muscle Relaxants: Therapeutic Uses
 01:24
Centrally Acting Muscle Relaxants: Therapeutic Uses
Centrally acting drugs are classified into spasmolytic and antispasmodic drugs. Spasmolytic drugs such as baclofen, diazepam, and tizanidine inhibit spinal motor neurons and decrease muscle tone. Spasmolytic drugs are administered for severe and chronic spasms due to multiple sclerosis, cerebral palsy, stroke, and spinal cord and muscle injuries. However,...