Related Experiment Video
Updated: Jun 5, 2026


Block Building Task Identifies Distinct Groups of Left/Right-hand Choice Patterns After Unilateral Peripheral Nerve Injury
Published on: March 21, 2025
Variations in the anatomic relations of the posterior interosseous nerve associated with proximal forearm trauma
Ryan P Calfee1, Joyce M Wilson, Ambrose H W Wong
1Washington University Medical Center, St. Louis, MO 63110, USA. calfeer@wudosis.wustl.edu

Background:
The posterior interosseous nerve is at risk for iatrogenic injury during surgery involving the proximal aspect of the radius. Anatomic relationships of this nerve in skeletally intact cadavers have been defined, but variations associated with osseous and soft-tissue trauma have not been examined. This study quantifies the effect of a simulated diaphyseal fracture of the proximal aspect of the radius and of a radial neck fracture with an Essex-Lopresti injury on the posterior interosseous nerve.
Methods:
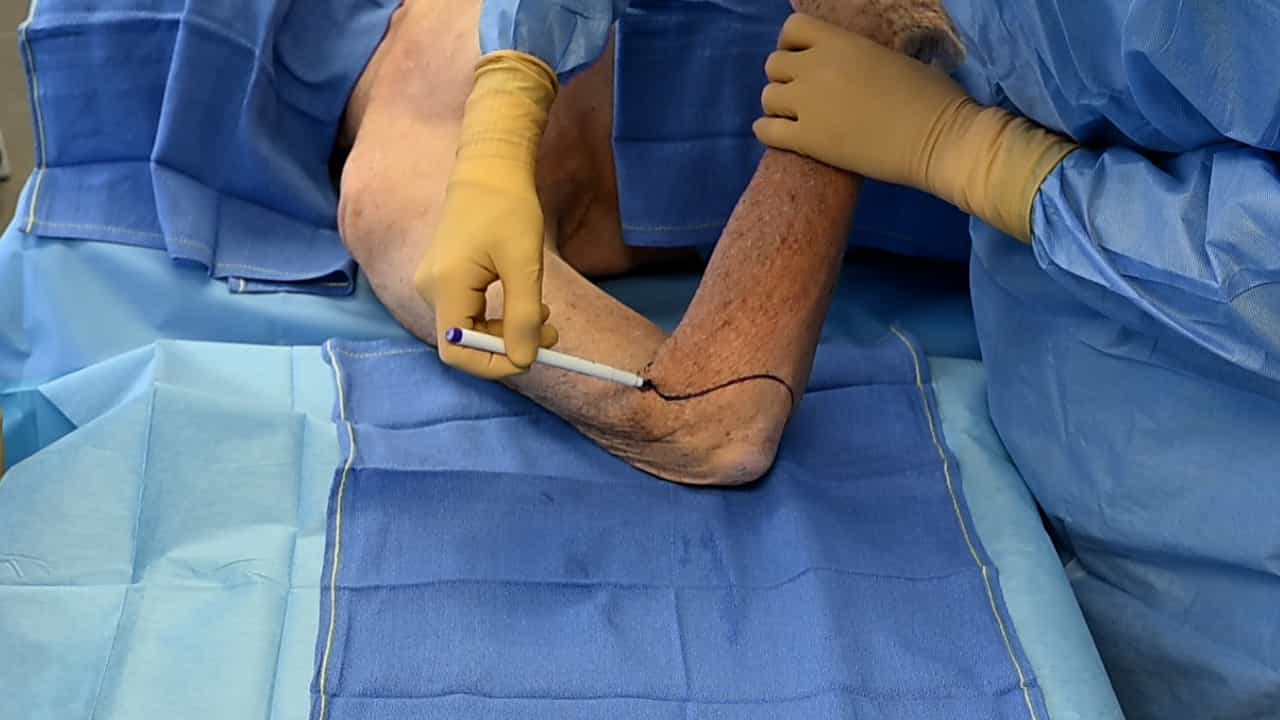
In twenty unembalmed cadaveric upper extremities, the distance from the radiocapitellar joint to the point where the posterior interosseous nerve crosses the midpoint of the axis of the radius (Thompson approach) was recorded in three forearm positions (supination, neutral, and pronation). Specimens were then treated with either proximal diaphyseal osteotomy (n = 10) or radial head excision with simulated Essex-Lopresti injury (n = 10), and the position of the nerve in each forearm position was remeasured. We evaluated the effect of the simulated trauma on nerve position and correlated baseline measurements with radial length.
Results:
In neutral rotation, the posterior interosseous nerve crossed the radius at a mean of 4.2 cm (range, 2.5 to 6.2 cm) distal to the radiocapitellar joint. In pronation, the distance increased to 5.6 cm (range, 3.1 to 7.4 cm) (p < 0.01). Supination decreased that distance to 3.2 cm (range, 1.7 to 4.5 cm) (p < 0.01). Radial length correlated with each of these measurements (r > 0.50, p = 0.01). Diaphyseal osteotomy of the radius markedly decreased the effect of forearm rotation, as the change in nerve position from supination to pronation decreased from 2.13 ± 0.8 cm to 0.24 ± 0.2 cm (p = 0.001). Proximal migration of the radius following radial head excision was accompanied by similar magnitudes of proximal nerve migration in all forearm positions.
Conclusions:
Forearm pronation has minimal effect on posterior interosseous nerve position within the surgical window following a displaced diaphyseal osteotomy of the proximal aspect of the radius. The nerve migrates proximally toward the capitellum with proximal migration of the radius in all forearm positions following a simulated Essex-Lopresti lesion. Visualization and protection of the posterior interosseous nerve is recommended when operatively exposing the traumatized proximal aspect of the radius.
Related Concept Videos
 01:16
Muscles of the Forearm that Move the Hand and Fingers
Anterior Compartment
The anterior compartment muscles originate from the humerus. They primarily function as flexors and are also known as flexor muscles. They typically insert on the carpals, metacarpals, and phalanges. The superficial layer includes the flexor carpi radialis,...
 01:22
Spinal Nerves: Plexus I
The Cervical Plexus
The cervical plexus, formed by the anterior rami of the first four...
 01:16
Muscles that Move the Forearm
Forearm Flexors
The biceps brachii, brachialis, and brachioradialis are forearm flexors. The biceps brachii is made up of two heads. Its long head originates at the supraglenoid tubercle of the scapula, whereas that of the short head is...
 01:15
Bones of the Upper Limb: Ulna
 01:09
Bones of the Upper Limb: Radius
The radius has a nail-shaped head, and a short...
 01:12
Arteries of the Upper Limbs