Related Experiment Video
Updated: Jun 5, 2026
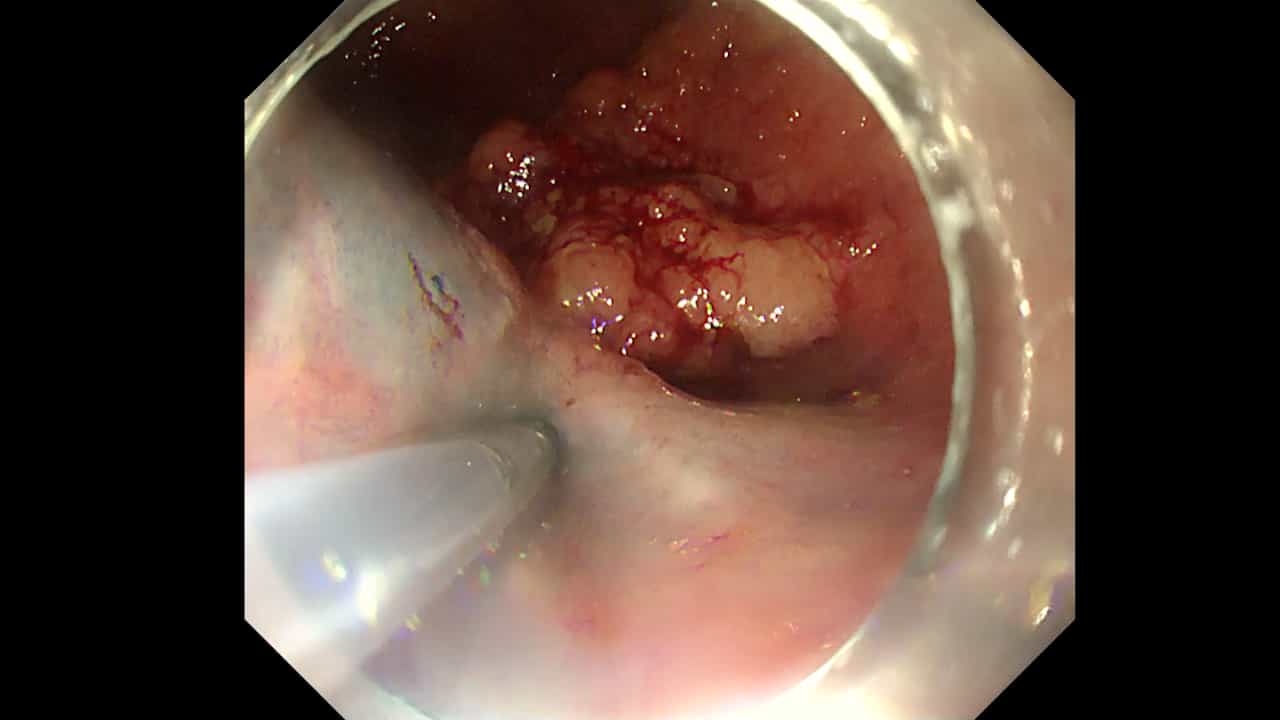

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Does a subcentimeter distal resection margin adversely influence oncologic outcomes in patients with rectal cancer
Ravi P Kiran1, Lei Lian, Ian C Lavery
1Department of Colorectal Surgery, Cleveland Clinic Foundation, Cleveland, Ohio 44195, USA. kiranp@ccf.org

Background:
A 1-cm distal clearance margin is recommended for mid/low rectal cancers.
Objective:
We evaluate whether shorter distal margins after restorative rectal resection affect oncologic outcomes for patients with a clear circumferential margin.
Design:
From a prospective cancer database, patients undergoing restorative proctectomy for mid/lower third rectal cancer from 1991 to 2006 with a distal margin of ≤ 1 cm (group A) were compared with those with >1-cm distal margin (group B) for demographics, tumor, treatment, and outcomes. The impact of a distal margin ≤ 0.5 cm was also similarly assessed.
Results:
Of 784 patients, distal resection margin was ≤ 1 cm in 198 and >1 cm in 586. Local recurrence occurred in 26 patients (3.3%). Mean distal resection margin was 2.3 ± 1.6 cm. Group A was associated with a lower level of tumor (1.3, 0.1-9 cm vs 2, 0.1-9 cm; P < .001), a higher rate of handsewn anastomosis (29.5% vs 12.9%, P < .001), and fewer T3/T4 tumors (28.2% vs 39.1%, P = .06). The 5-year local recurrence rate was 4.4% in group A and 4.3% in group B, and was 6.4% in patients with a distal margin <5 mm and 4.1% in those with a distal margin >5 mm. On multivariable analysis, local recurrence or disease-free survival was not associated with distal margin irrespective of whether this was <1 or <0.5 cm, adjusting for age, sex, use of adjuvant therapy, T stage, and differentiation.
Conclusions:
A distal resection margin of <1 cm for patients undergoing restorative radical resection for low-lying rectal cancer does not adversely influence oncologic outcomes when other factors are carefully considered and a multimodality approach is used. This factor, when carefully considered, will help avoid a permanent stoma in some circumstances.

