Related Experiment Video
Updated: Jun 5, 2026
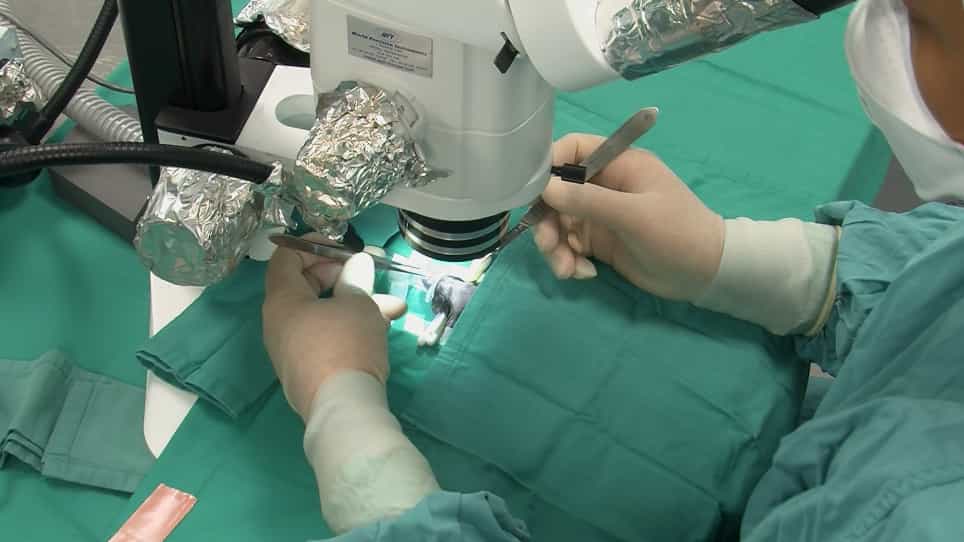

Middle Cerebral Artery Occlusion Allowing Reperfusion via Common Carotid Artery Repair in Mice
Published on: January 23, 2019
Cerebral infarct in patients with bilateral high-grade internal carotid artery stenosis: analysis by
Chien-Tai Hong1, Hoi-Fong Chan, Siu-Pak Lee
1Department of Neurology, Far Eastern Memorial Hospital, Taipei, Taiwan, ROC. b8701037@tmu.edu.tw

Insights
Patients with bilateral high-grade internal carotid artery (ICA) stenosis experienced fewer strokes on the side with milder stenosis. Both artery-to-artery emboli and reduced blood flow contribute to stroke in these patients.
Area of Science:
- Neurology
- Vascular Medicine
- Radiology
Background:
- Bilateral high-grade internal carotid artery (ICA) stenosis significantly impacts cerebral perfusion.
- Understanding infarct patterns on diffusion-weighted imaging (DWI) aids in investigating stroke mechanisms.
Purpose of the Study:
- To investigate infarct patterns in patients with bilateral high-grade ICA stenosis.
- To analyze the relationship between stenosis severity, infarct location, and stroke risk.
Main Methods:
- Retrospective analysis of 21 acute infarct patients with bilateral high-grade ICA stenosis (Jan 2006-Oct 2010).
- Classification of infarct patterns using DWI: territory, cortical border-zone, and internal border-zone.
Main Results:
- Ischemic stroke risk was lower on the side with milder ICA stenosis (4/20 patients).
- No strokes occurred ipsilateral to the milder stenosis in patients with bilateral severe ICA stenosis (70-99%).
- Cortical border-zone (10/21) was the most frequent infarct pattern, followed by internal border-zone (7/21) and territory.
Conclusions:
- Cerebral infarcts are less common on the side with milder ICA stenosis, particularly in severe bilateral cases.
- Similar frequencies and hemodynamic status across infarct patterns suggest synergistic contributions from artery-to-artery emboli and hemodynamic compromise.
Background:
Bilateral high-grade internal carotid artery (ICA) stenosis is critical for brain perfusion, and mechanisms of cerebral infarct induced by bilateral high-grade ICA stenosis can be investigated by the infarct patterns on diffusion-weighted imaging (DWI).
Methods:
From January 2006 to October 2010, we retrospectively enrolled 21 acute infarct patients with bilateral high-grade ICA stenosis. The infarct patterns were divided into territory, cortical border-zone and internal border-zone by DWI.
Results:
The milder ICA stenosis side had a lower risk of ischemic stroke (4 of 20). None of the 8 patients with bilateral severe ICA stenosis (70-99%) suffered ischemic stroke ipsilateral to the milder ICA stenosis side. No single infarct mechanism was prominent: 10 of 21 infarcts were cortical border-zone pattern, followed by internal border-zone (7 of 21) and territory. The difference in frequency of bilateral severe ICA stenosis between the three infarct mechanisms was not significant (p = 0.856).
Conclusions:
Cerebral infarcts occurred less frequently in the ipsilateral to milder ICA stenosis side, especially in bilateral severe ICA stenosis. The similar frequencies and hemodynamic status between the three infarct pattern groups indicated that both artery-to-artery emboli and being hemodynamically compromised contribute synergistically to bilateral ICA stenosis.
