Neurally adjusted ventilatory assist: a ventilation tool or a ventilation toy?
Related Experiment Video
Updated: Jun 5, 2026

Use of an Integrated Low-Flow Anesthetic Vaporizer, Ventilator, and Physiological Monitoring System for Rodents
Published on: July 9, 2020
Walter Verbrugghe1, Philippe G Jorens
1Department of Critical Care Medicine, University of Antwerp, Edegem, Belgium. walter.verbrugghe@uza.be

Abstract:
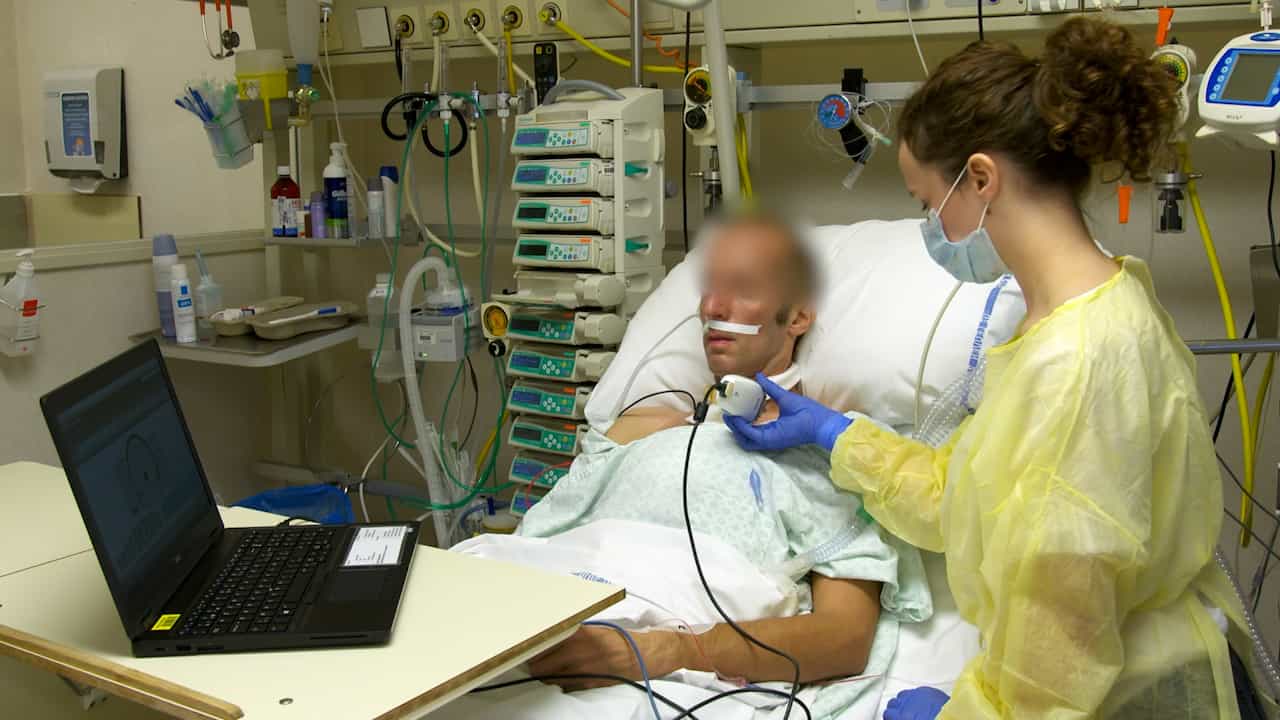
Mechanical ventilation has, since its introduction into clinical practice, undergone a major evolution from controlled ventilation to various modes of assisted ventilation. Neurally adjusted ventilatory assist (NAVA) is the newest development. The implementation of NAVA requires the introduction of a catheter to measure the electrical activity of the diaphragm (EA(di)). NAVA relies, opposite to conventional assisted ventilation modes, on the EA(di) to trigger the ventilator breath and to adjust the ventilatory assist to the neural drive. The amplitude of the ventilator assist is determined by the instantaneous EA(di) and the NAVA level set by the clinician. The NAVA level amplifies the EA(di) signal and determines instantaneous ventilator assist on a breath-to-breath basis. Experimental and clinical data suggest superior patient-ventilator synchrony with NAVA. Patient-ventilator asynchrony is present in 25% of mechanically ventilated patients in the intensive care unit and may contribute to patient discomfort, sleep fragmentation, higher use of sedation, development of delirium, ventilator-induced lung injury, prolonged mechanical ventilation, and ultimately mortality. With NAVA, the reliance on the EA(di) signal, together with an intact ventilatory drive and intact breathing reflexes, allows integration of the ventilator in the neuro-ventilatory coupling on a higher level than conventional ventilation modes. The simple monitoring of the EA(di) signal alone may provide the clinician with important information to guide ventilator management, especially during the weaning process. Although, until now, little evidence proves the superiority of NAVA on clinically relevant end points, it seems evident that patient populations (eg, COPD and small children) with major patient-ventilator asynchrony may benefit from this new ventilatory tool.
More Related Videos

Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:14
Ventilatory Modes
There are three ventilatory modes: full support, partial support, and spontaneous. These are described below.
Full Support Modes
Full support modes include controlled mechanical ventilation, continuous mandatory...
 01:29
Mechanical Ventilation I: Indication and Settings
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management