Related Experiment Video
Updated: Jun 4, 2026


Drug-Induced Sleep Endoscopy (DISE) with Target Controlled Infusion (TCI) and Bispectral Analysis in Obstructive Sleep Apnea
Published on: December 6, 2016
Impact of the O-C2 angle on the oropharyngeal space in normal patients
Masato Ota1, Masashi Neo, Tomoki Aoyama
1Department of Orthopaedic Surgery, Graduate School of Medicine, Kyoto University, Kyoto, Japan.

Study Design:
Radiographic analysis using normal patients.
Objective:
To analyze the relationship between the cervical alignment and the oropharyngeal space.
Summary Of Background Data:
Few clinical studies stress the effect of the occipito-C2 (O-C2) alignment on the oropharyngeal space. A previous study showed dysphagia and/or dyspnea after occipitocervical fusion was caused by oropharyngeal stenosis resulting from O-C2 fixation in a flexed position. Other independent researchers showed that development or improvement of obstructive sleep apnea in rheumatoid arthritis patients was related to the O-C2 alignment. However, there are limited basic data demonstrating the relationship between the O-C2 alignment and the oropharyngeal space.
Methods:
Plain lateral cervical radiographs in five tested positions--neutral, flexion, extension, protrusion, and retraction--of 40 asymptomatic volunteers were collected. The O-C2 angle, the C2-C6 angle, and the anterior-posterior distance of the narrowest oropharyngeal airway space (nPAS) were measured, and the changes in value from the neutral to the other four positions were calculated for each patient.
Results:
According to the multiple regression analysis, there was an extremely strong linear correlation of the change in the O-C2 angle with the percentage change in the nPAS. Referring to the multiple regression analysis, a decrease of 10° in the O-C2 angle caused a 37% reduction in the nPAS in the neutral position. In contrast, no significant correlation was found between the change in the C2-C6 angle and the percentage change in the nPAS.
Conclusion:
Our results show the impact of the O-C2 angle on the oropharyngeal space. This knowledge will be useful for the diagnosis and treatment of the upper cervical lesion combined with the upper airway stenosis, and for the determination of the optimal fixation angle in occipitocervical fusion.
Related Concept Videos
 01:25
Suctioning the Oropharyngeal Airway
After assembling the equipment, the nurse should practice hand hygiene and don appropriate PPE according to infection control guidelines to avoid the...
 01:11
Oral Cavity
Teeth: The teeth are the hardest structures in our bodies. Humans have two sets of teeth throughout their lifetime: deciduous (baby) teeth and permanent teeth. Each tooth consists of several parts: the crown (visible part), the root (embedded in the jaw), enamel (hard outer...
 01:29
Suctioning the Nasopharyngeal Airway
Equipment Required
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:20
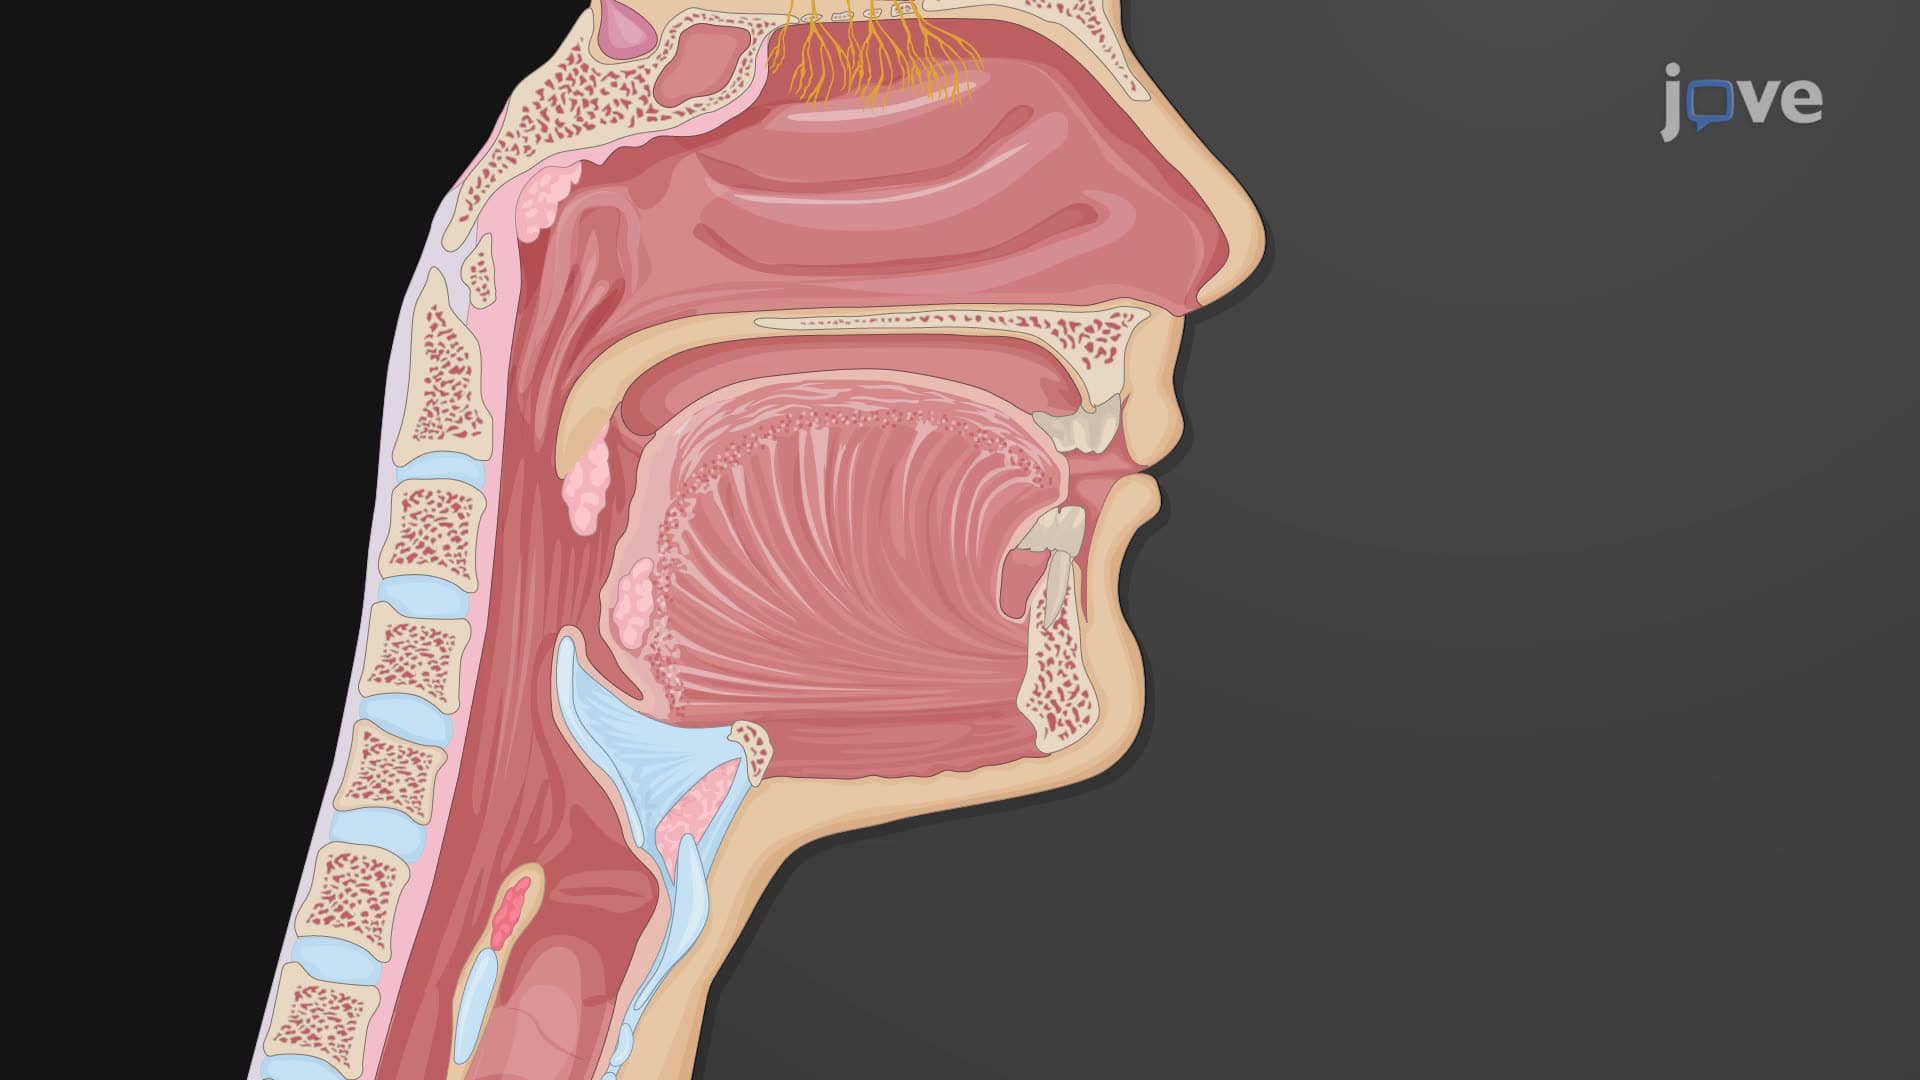
Pharynx
Nasopharynx
The nasopharynx, bordered by the conchae of the nasal cavity, serves exclusively as an air conduit. In its superior region, the pharyngeal tonsils or adenoids are located. These tonsils are clusters of lymphoid reticular tissue akin to a lymph node. The precise...