Related Experiment Videos
Best practice wound care
Melissa L O'Brien1, Joanna E Lawton, Chris R Conn
1Quality & Risk Management Unit, St Vincent's Hospital, Sydney, New South Wales, Australia.

Abstract:
This article describes the barriers, changes and achievements related to implementing one element of a wound care programme being best practice care. With the absence of a coordinated approach to wound care, clinical practice within our Area Health Service (AHS) was diverse, inconsistent and sometimes outdated. This was costly and harmful, leading to overuse of unhelpful care, underuse of effective care and errors in execution. The major aim was to improve the outcomes and quality of life for patients with wound care problems within our community. A collaborative across ten sites/services developed, implemented and evaluated policies and guidelines based on evidence-based bundles of care. Key barriers were local resistance and lack of experience in implementing structural and cultural changes. This was addressed by appointing a wound care programme manager, commissioning of a strategic oversight committee and local wound care committees. The techniques of spread and adoption were used, with early adopters making changes observable and allowing local adaption of guidelines, where appropriate. Deployment and improvement results varied across the sites, ranging from activity but no changes in practice to modest improvement in practice. Evaluating implementation of the leg ulcer guideline as an exemplar, it was demonstrated that there was a statistically significant improvement in overall compliance from 26% to 84%. However, only 7·7% of patients received all interventions to which they were entitled. Compliance with the eight individual interventions of the bundle ranged from 26% to 84%. Generic performance was evaluated against the wound assessment, treatment and evaluation plan with an average compliance of 70%. Early results identified that 20% of wounds were healed within the target of 10 days. As more standardised process are implemented, clinical outcomes should continue to improve and costs decrease.
Related Concept Videos
 01:28
Phases of Wound Repair
Formation of Blood Clot
In case of deep injuries, trauma to blood vessels results in blood loss. In the meantime, phospholipids released from the ruptured endothelial cellular membrane are converted into arachidonic...
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management
 01:26
Peripheral Artery Disease IV: Nursing Management
 01:15
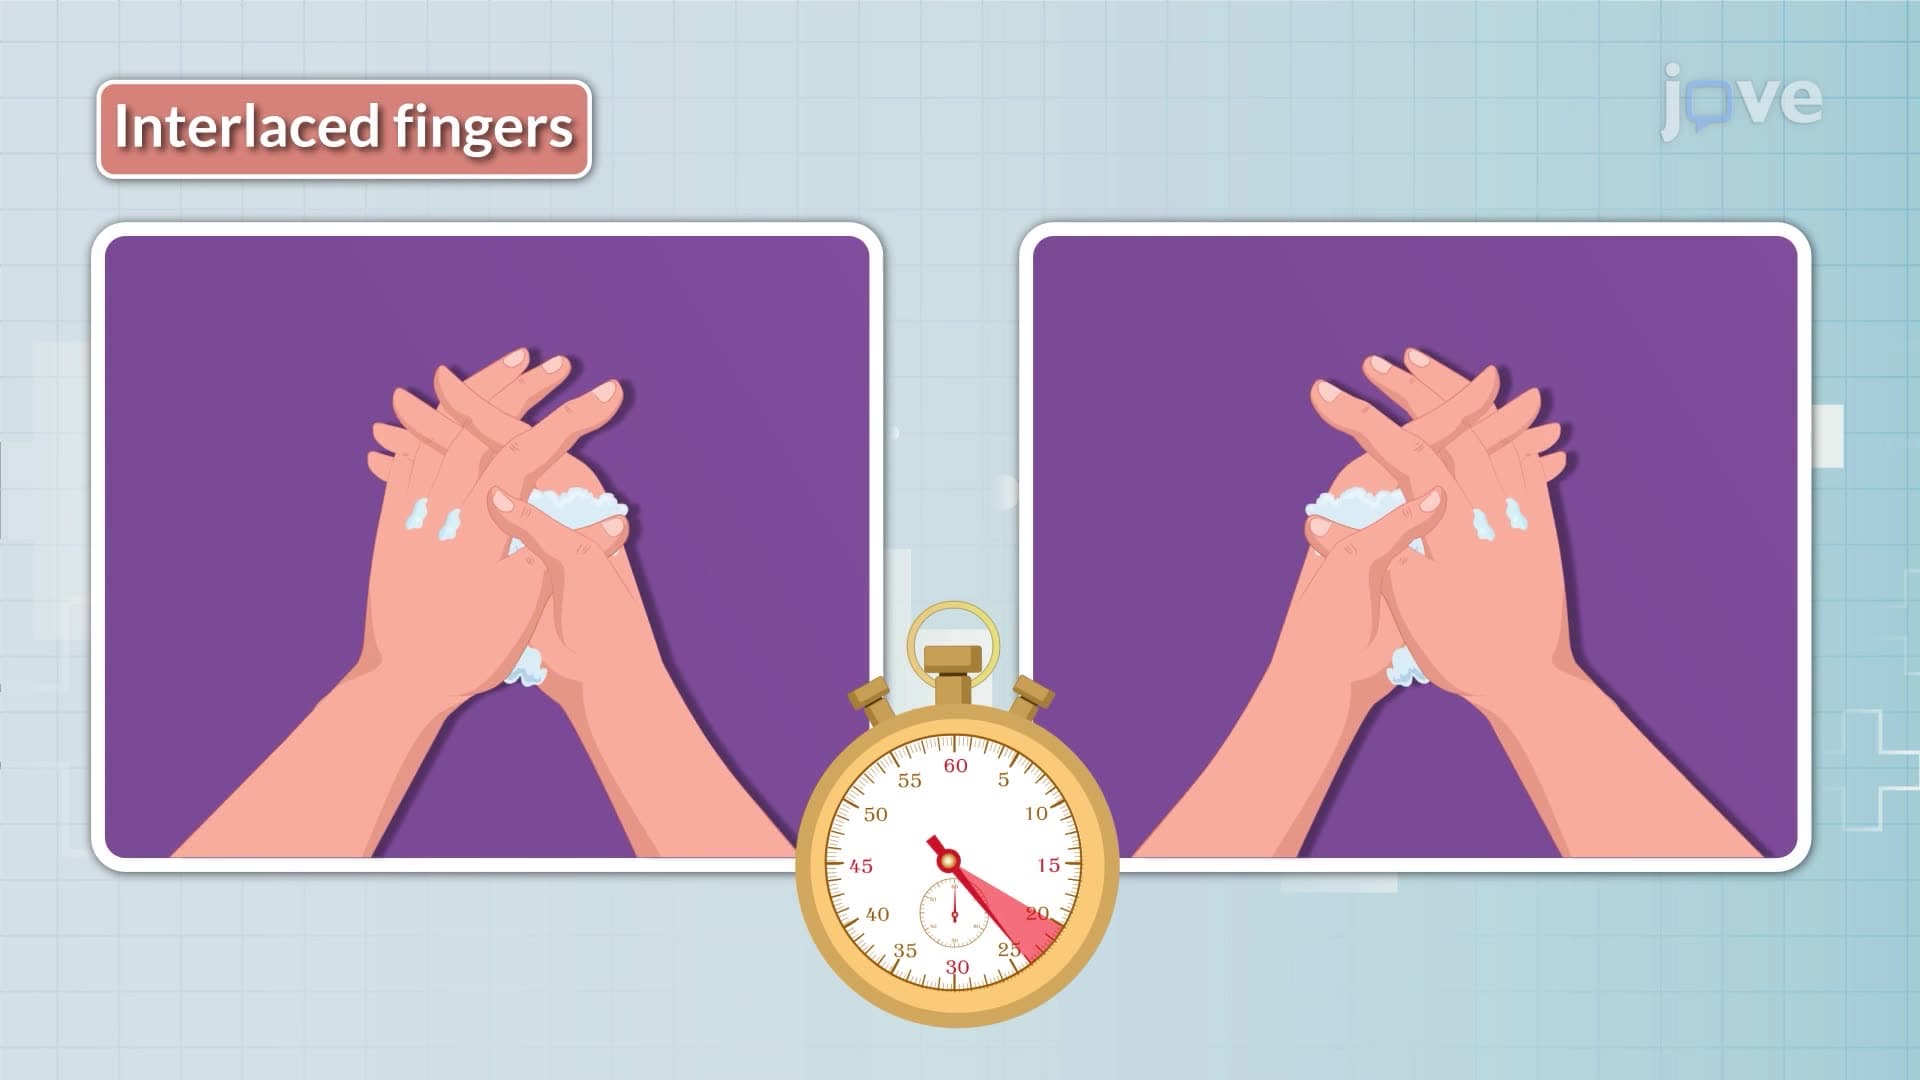
Handwashing III: During the Procedure and Post-Procedure Steps
 01:19
Handwashing II: Pre-procedure and Initial Procedure Steps
The hand washing procedure itself includes the following steps. First, cover cuts, if any, on hands with a waterproof dressing. Cuts and abrasions can become contaminated with bacteria hindering the ability to clean the area thoroughly. In addition, repeated hand washing can worsen an injury. The nails must be short and clean, without nail paint...