Related Experiment Video
Updated: Jun 4, 2026


Molecular and Immunologic Techniques in a Genetically Engineered Mouse Model of Gastrointestinal Stromal Tumor
Published on: May 2, 2022
Gastrointestinal stromal tumors: morphological, immunohistochemical and molecular changes associated with kinase
Mario Díaz Delgado1, Alicia Hernández Amate, Sofía Pereira Gallardo
1Servicio de Anatomía Patológica, Hospital de Mérida, Badajoz, Spain.

Abstract:
Recurrent or metastatic GISTs are currently treated with kinase inhibitors since they achieves disease control in 70-85% of patients but this response depend on KIT and PDGFRA gene mutation status. We review the morfological and molecular findings associated to kinase inhibitors administration in GISTs based on the literature on Medline and authors' own experience. The initial response to kinase inhibitors (imatinib mesylate, Gleevec, Novartis) usually is partial and depend on the mutational KIT or PDGFRA state. Amongst patients wih KIT mutations, the best results are achived in those harboring exon 11 (85%) and exon 9 (45%) mutations. GISTs harboring PDGFRA gene mutations generally respond favorably except those involving the Asp842Val mutation. In the absence of KIT/PDGFRA gene mutations, partial response or disease stabilization is reported in 23% and 50% of patients, respectively, and disease progression in 19%. Histological examination of tumors displaying an initial response to imatinib reveals a highly-variable reduction in the number of tumor cells, a decline in the proliferative index, myxohyaline or sclerohyaline stroma, and a varying degree of bleeding and edema, necrosis and cystification. 72% of patients with initial good response to imatinib, display metastases or new nodule growth within an existing clinically-quiescent tumor after 12-36 months of treatment. This secondary resistance is characterized by a number of well-defined morphological and molecular changes. Histologically, the new growths display increased mitotic activity, pleomorphism, an epithelioid or mixed phenotype and persistent KIT expression although more rarely, dedifferentiation and loss of KIT expression (Fig. 4), as well as trans-differentiation into a rhabdomyosarcoma or epithelial phenotype has been reported. Molecularly, 46-67% of patients present additional KIT mutations, generally in the kinase domain (exons 13, 14 and 17) but also in the ATP-binding domain (exons 15,16) of the same allele. Secondary PDGFRA mutations are very rare. Secondary mutations have not been observed in GISTs not harboring KIT/PDGFRA mutations, or in tumors displaying an unusual morphology or loss of CD117 expression. A number of studies highlight the presence of different resistance mutations within different new tumor nodules, as well as the simultaneous development of distinct resistant tumor subclones within a single lesion (acquired polyclonal resistance). Secondary mutation in genes other than KIT/PDGFRA has only been reported in BRAF (Val600Glu).
Insights
Kinase inhibitors control most gastrointestinal stromal tumors (GISTs), but response varies with KIT/PDGFRA mutations. Secondary resistance often involves new KIT mutations, leading to treatment challenges.
Area of Science:
- Oncology
- Molecular Biology
- Genetics
Background:
- Gastrointestinal stromal tumors (GISTs) are primarily treated with kinase inhibitors, achieving disease control in 70-85% of patients.
- Treatment efficacy is significantly influenced by specific KIT and PDGFRA gene mutation statuses.
- Understanding morphological and molecular changes is crucial for managing GISTs.
Purpose of the Study:
- To review morphological and molecular findings associated with kinase inhibitor administration in GISTs.
- To elucidate the mechanisms of initial response and secondary resistance to kinase inhibitors in GISTs.
- To correlate genetic mutations with treatment outcomes and resistance patterns.
Main Methods:
- Literature review of Medline database and authors' experience.
- Analysis of morphological changes in GISTs responding to imatinib.
- Molecular analysis of KIT and PDGFRA gene mutations, including secondary mutations.
Main Results:
- Initial response to imatinib depends on KIT (exon 11, 9) and PDGFRA (excluding Asp842Val) mutations.
- GISTs without KIT/PDGFRA mutations show lower response rates (23% partial response, 50% stabilization).
- Secondary resistance develops in 72% of patients within 12-36 months, often due to new KIT mutations (exons 13, 14, 17, 15, 16).
Conclusions:
- Kinase inhibitors are effective for GISTs, but mutation status dictates initial response.
- Secondary resistance, driven by acquired mutations (primarily in KIT), is a significant clinical challenge.
- Morphological and molecular monitoring is essential for effective GIST management and overcoming resistance.
More Related Videos
 06:43
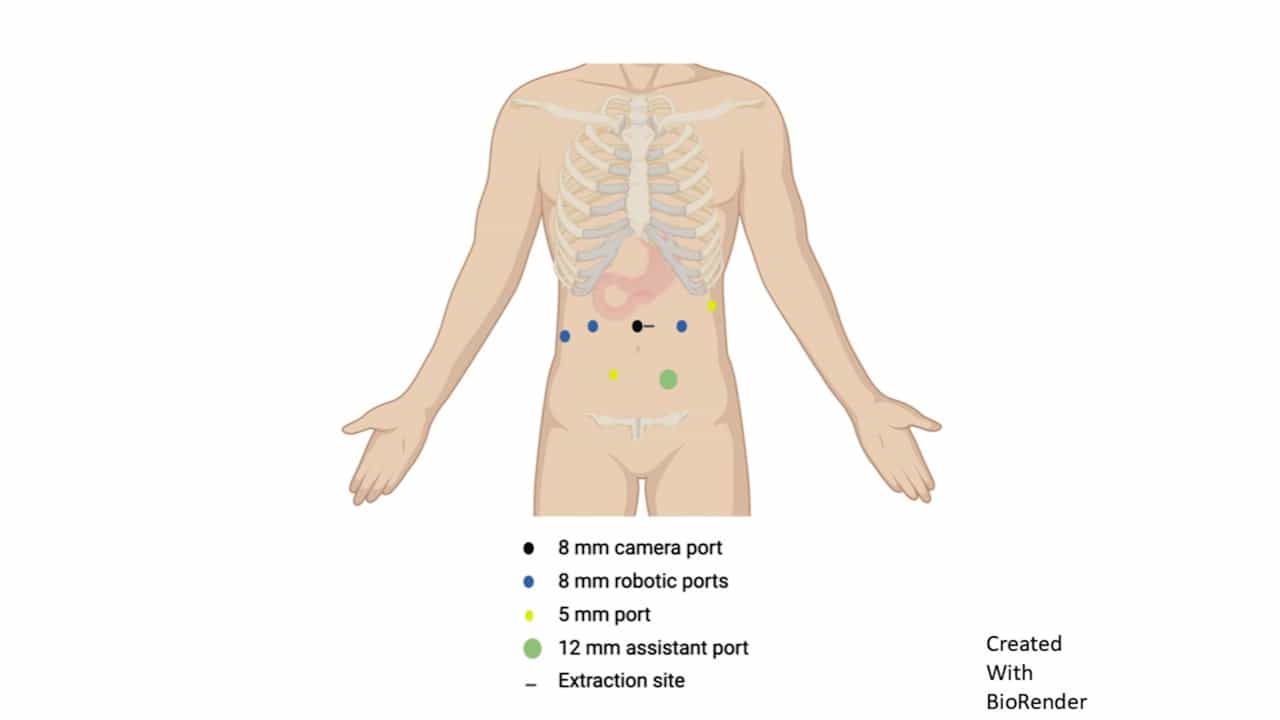
Robotic Duodenal Sleeve Resection for Gastrointestinal Stromal Tumor with Rare Exon 8 KIT Mutation Following Neoadjuvant Imatinib
Published on: April 3, 2026
 10:27
Testing Targeted Therapies in Cancer using Structural DNA Alteration Analysis and Patient-Derived Xenografts
Published on: July 25, 2020
Related Concept Videos
 01:15
Drugs that Stabilize Microtubules
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...