Corpus callosotomy in multistage epilepsy surgery in the pediatric population
Jessica S Lin1, Sean M Lew, Charles J Marcuccilli
1Department of Neurosurgery, Medical College of Wisconsin, Milwaukee, Wisconsin, USA.

Insights
Corpus callosotomy combined with invasive electroencephalography (EEG) monitoring can improve surgical outcomes for children with medically refractory epilepsy. This multistage approach helps localize seizure foci for targeted resection, leading to better seizure control.
Area of Science:
- Neurosurgery
- Epileptology
- Pediatric Neurology
Background:
- Medically refractory epilepsy in children presents significant management challenges.
- Corpus callosotomy is often considered for generalized epilepsy, but outcomes can be limited.
- Multistage epilepsy surgery aims to improve seizure control through targeted resections.
Purpose of the Study:
- To evaluate the surgical outcomes of corpus callosotomy combined with bilateral subdural electroencephalography (EEG) electrode placement.
- To assess the efficacy of this approach as an initial step in multistage epilepsy surgery for select pediatric patients.
- To determine if invasive monitoring can identify surgically amenable seizure foci.
Main Methods:
- Retrospective review of 18 children (ages 3.5-18) with medically refractory epilepsy.
- Corpus callosotomy with bilateral subdural EEG electrode placement performed as the first surgical stage.
- Patients monitored invasively for 3-14 days; follow-up ranged from 6-70 months.
Main Results:
- Twelve of 18 patients proceeded to further resection based on invasive EEG data.
- Six of 12 patients (50%) who underwent resection achieved excellent outcomes (Engel Class I or II).
- No permanent neurological deficits or deaths were reported.
Conclusions:
- Combining corpus callosotomy with invasive EEG monitoring can localize seizure foci in refractory epilepsy.
- This strategy enables targeted resections, potentially improving seizure outcomes in select pediatric cases.
- The approach offers an alternative to palliative surgery alone for complex epilepsy patients.
Object:
The object of this study was to evaluate surgical outcome in a select group of patients with medically refractory epilepsy who had undergone corpus callosotomy combined with bilateral subdural electroencephalography (EEG) electrode placement as the initial step in multistage epilepsy surgery.
Methods:
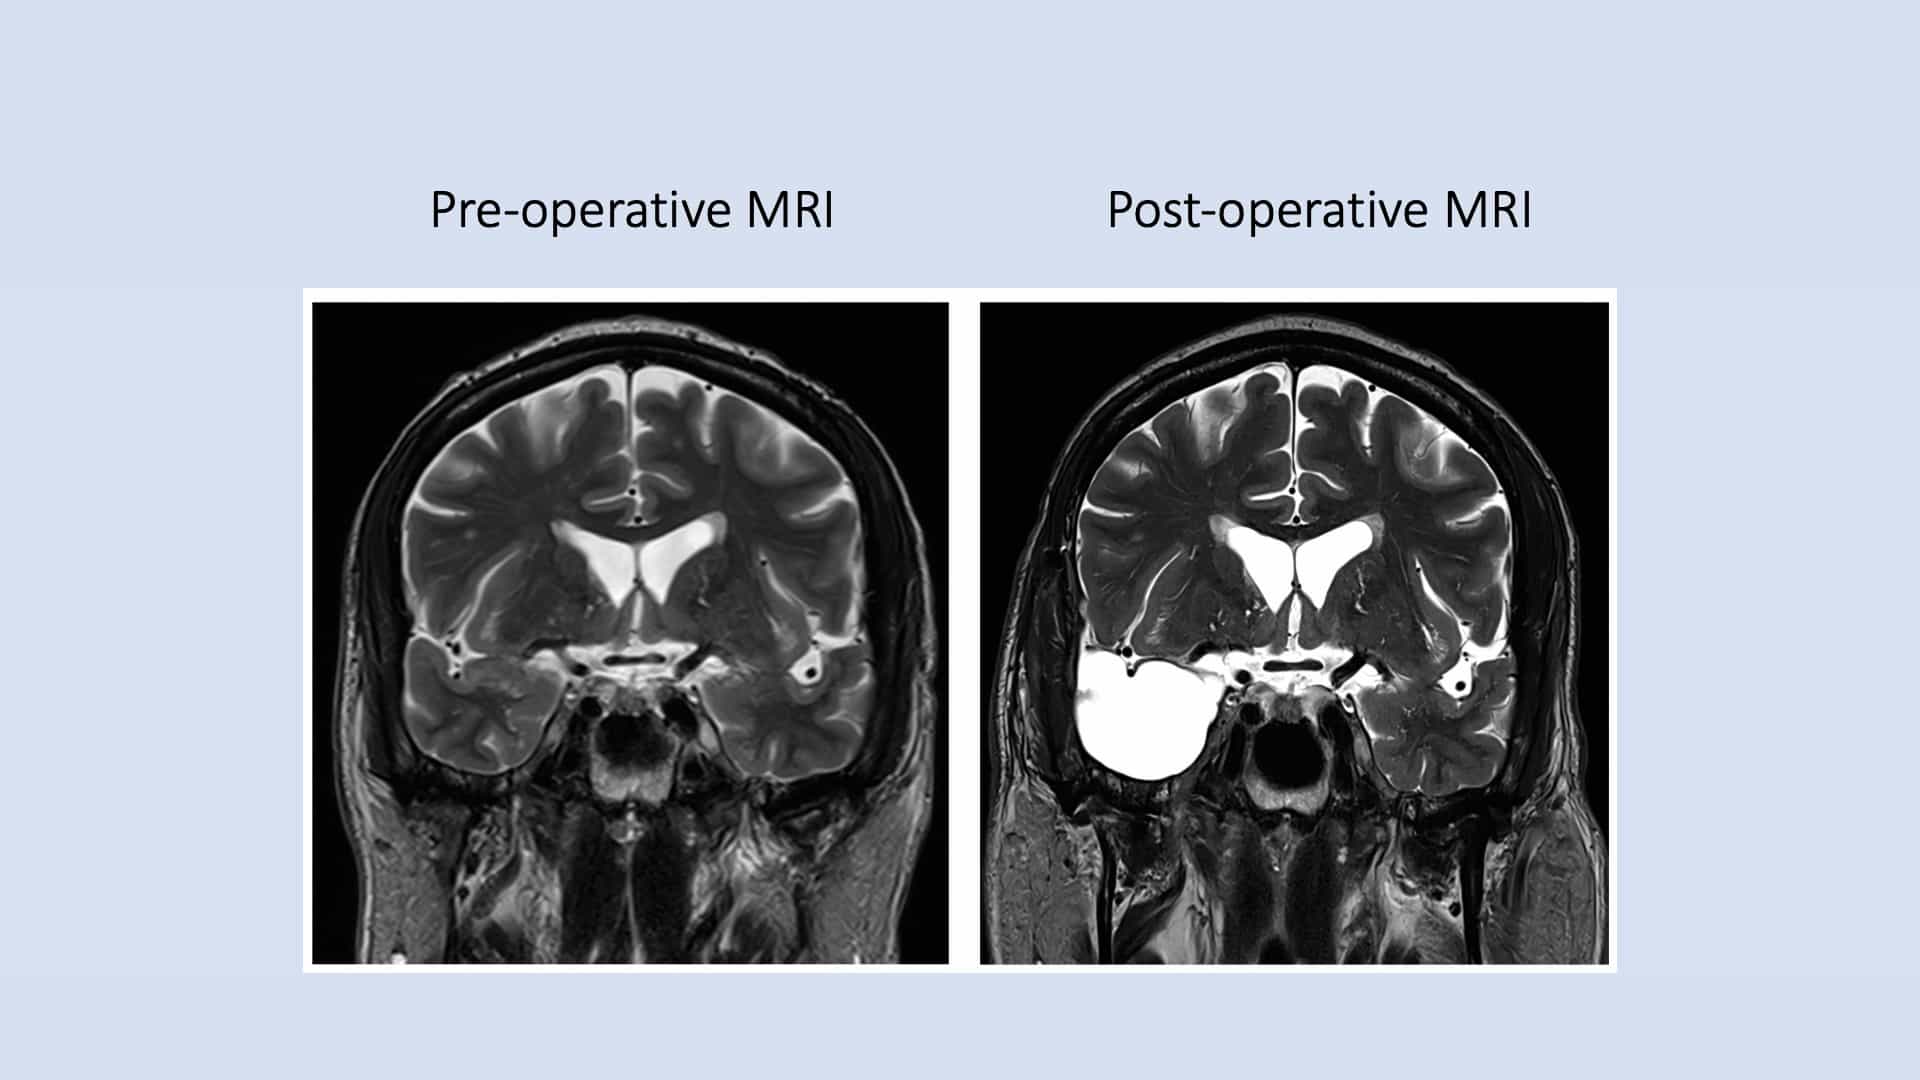
A retrospective chart review of 18 children (ages 3.5-18 years) with medically refractory symptomatic generalized or localization-related epilepsy was undertaken. A corpus callosotomy with subdural bihemispheric EEG electrode placement was performed as the initial step in multistage epilepsy surgery. All of the patients had tonic and atonic seizures; 6 patients also experienced complex partial seizures. All of the patients had frequent generalized epileptiform discharges as well as multifocal independent epileptiform discharges on surface EEG monitoring. Most of the patients (94%) had either normal (44%) MR imaging studies of the brain or bihemispheric abnormalities (50%). One patient had a suspected unilateral lesion (prominent sylvian fissure).
Results:
Of the 18 patients who underwent corpus callosotomy and placement of subdural strips and grids, 12 progressed to further resection based on localizing data obtained during invasive EEG monitoring. The mean patient age was 10.9 years. The duration of invasive monitoring ranged from 3 to 14 days, and the follow-up ranged from 6 to 70 months (mean 35 months). Six (50%) of the 12 patients who had undergone resection had an excellent outcome (Engel Class I or II). There were no permanent neurological deficits or deaths.
Conclusions:
The addition of invasive monitoring for patients undergoing corpus callosotomy for medically refractory epilepsy may lead to the localization of surgically amenable seizure foci, targeted resections, and improved seizure outcomes in a select group of patients typically believed to be candidates for palliative surgery alone.