Related Experiment Video
Updated: Jun 4, 2026
Laparoscopic Posterior Radical Antegrade Modular Pancreatosplenectomy for Distal Pancreatic Carcinoma
Published on: December 29, 2023
Multimedia article. Laparoscopic modified anterior RAMPS in well-selected left-sided pancreatic cancer: technical
Sung Hoon Choi1, Chang Moo Kang, Woo Jung Lee
1Division of Biliopancreas, Department of Surgery, Yonsei University College of Medicine, Ludlow Faculty Research Building #204, 250 Seongsanno, Seodaemun-gu, Seoul, 120-752, Korea.

Background:
Laparoscopic distal pancreatectomy with splenectomy is regarded as a safe and effective treatment for benign and borderline malignant pancreatic lesions [1, 2]. However, its application for left-sided pancreatic cancer is still debatable [3, 4]. No general consensus, no standardized technique, and no surgical indication exist in applying the laparoscopic approach to left-sided pancreatic cancer.
Methods:
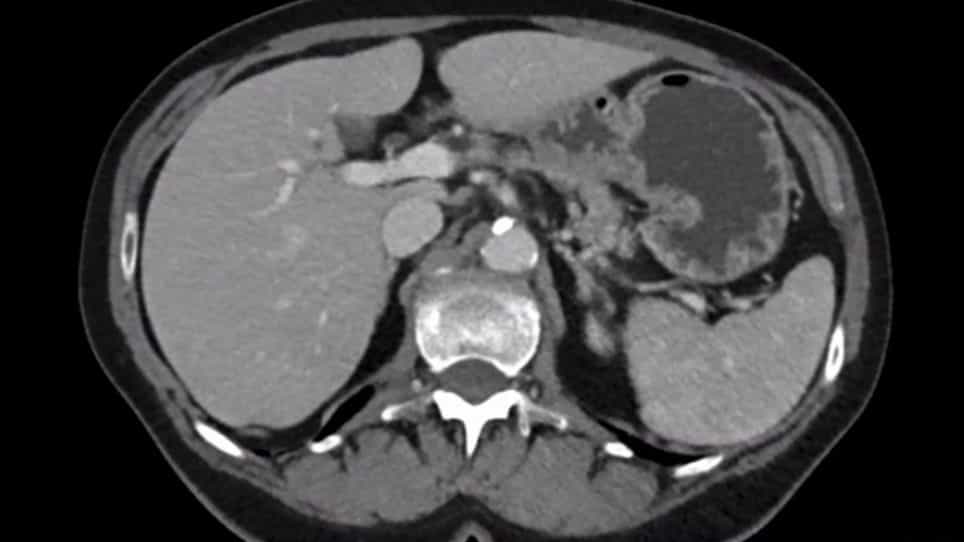
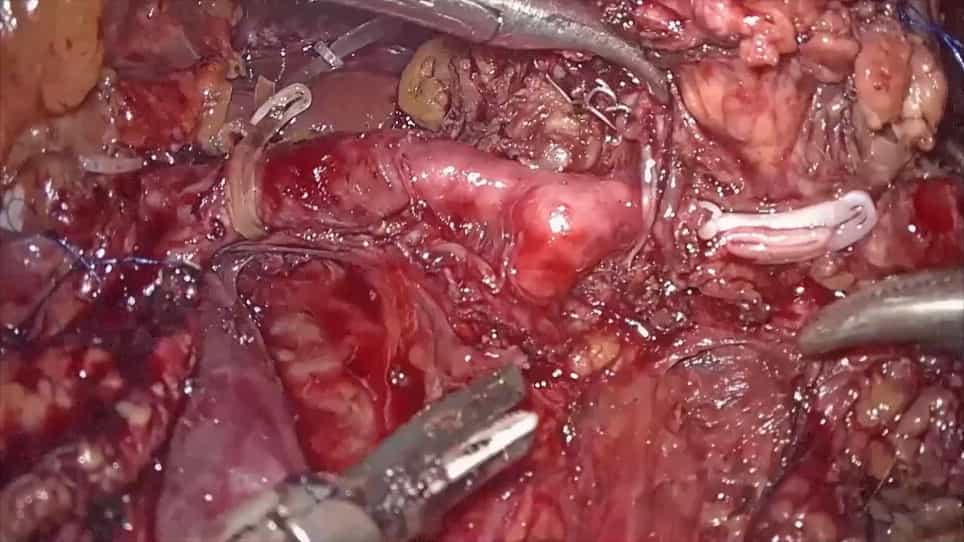
According to our institutional experiences of treating left-sided pancreatic cancer, bloodless and margin-negative resection was found to be important. Bloodless and margin-negative laparoscopic distal pancreatosplenectomy would be technically possible in suspicious pancreatic cancers with these tentative conditions: (1) pancreas-confined suspicious pancreatic cancer on preoperative image study (cT2), (2) intact fascia layer between the pancreas and left adrenal gland/left kidney, and (3) tumor more than 1 cm from the celiac axis. A 59-year-old female patient was found to have suspicious left-sided pancreatic cancer. Therefore, we performed laparoscopic anterior radical antegrade modular pancreatosplenectomy (RAMPS) [5, 6] with a curative intent based on selection criteria.
Results:
The margin-negative (resectional and tangential) curative resection could be obtained by applying laparoscopic anterior RAMPS in well-selected left-sided pancreatic cancer. The operation time was 180 min and estimated blood loss was 100 ml. The diagnosis from pathology was that the tumor was ductal adenocarcinoma of the pancreas (pT3) with lymph node metastasis (pN1, 2 of 23 lymph nodes). The patient went home on the 7th postoperative day. Adjuvant chemotherapy began within 2 weeks after surgery. From June 2007 to August 2010, nine patients underwent minimally invasive (5 laparoscopic and 4 robot-assisted) anterior RAMPS based on the selection criteria. The perioperative outcomes and short-term oncologic results are summarized.
Conclusion:
Laparoscopic modified anterior RAMPS is thought to be technically feasible for curative resection in well-selected pancreatic cancer. The oncologic feasibility of this technique needs to be investigated based on long-term follow-up. More careful study is necessary.