Related Experiment Video
Updated: Jun 4, 2026
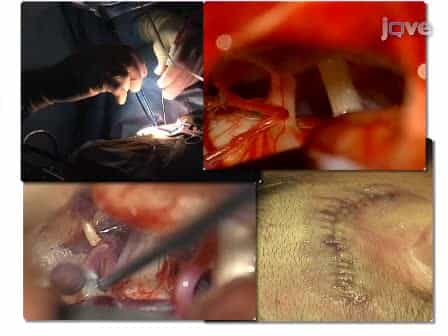
Microvascular Decompression: Salient Surgical Principles and Technical Nuances
Published on: July 5, 2011
Operative strategies for minimizing hearing loss and other major complications associated with microvascular
Aaron E Bond1, Gabriel Zada, Andres A Gonzalez
1Department of Neurosurgery, Keck School of Medicine, University of Southern California, Los Angeles, USA.

Objective:
To retrospectively assess the surgical outcomes and complication rates following microvascular decompression (MVD) for trigeminal neuralgia, using a targeted, restricted retrosigmoid approach.
Methods:
During the period 1994-2009, a total of 119 patients underwent MVD for trigeminal neuralgia. A retrospective review was conducted in order to assess pain outcomes following surgery and at most recent follow-up. The intraoperative findings, Barrow Neurologic Institute (BNI) pain scores, medication usage, brainstem auditory evoked potential records, and complication rates (including postoperative hearing status) were reviewed and subsequently analyzed.
Results:
Of the 119 patients who underwent MVD, 61 (51%) were male and 58 (49%) were female. The mean age was 60 years (range 22-86 years). Operative findings included 94 patients (79%) with arterial compression, 16 patients (13%) with isolated venous compression, 1 patient (1%) with a small arteriovenous malformation, and 8 patients (7%) with no obvious source of compression. No perioperative deaths or major complications, including hearing loss, occurred in any patients. Minor complications occurred in 9 patients (8%), including a transient trochlear nerve palsy in 1 patient, transient nystagmus in 1 patient, cerebrospinal fluid leak requiring revision in 1 patient, wound infections requiring revision in 3 patients, and wound infections requiring antibiotics alone in 3 patients. Follow-up data were available for 109 patients, of whom 88 (81%) had excellent outcomes (BNI Score I-II). Ninety-eight patients (90%) had good outcomes (BNI scores I-IIIb), 7 patients (6%) had persistent pain that was not controlled with medications (BNI Score IV), and 4 patients (4%) experienced no relief following surgery (BNI Score V).
Conclusion:
The use of a small craniectomy (<20 mm) in conjunction with a restricted retrosigmoid approach, inferolateral cerebellar retraction, and maintenance of the vestibular nerve arachnoid may minimize complications and optimize surgical outcomes associated with microvascular decompression for trigeminal neuralgia.
Related Concept Videos
 01:29
Venous Thrombosis III: Interprofessional Care
 01:23
Peripheral Artery Disease V: Postoperative Nursing Management