Related Experiment Video
Updated: Jun 4, 2026


Cardiac Stress Test Induced by Dobutamine and Monitored by Cardiac Catheterization in Mice
Published on: February 10, 2013
Effect of the ADRB1 1165C>G and 145A>G polymorphisms on hemodynamic response during dobutamine stress
Anna Banaś1, Edyta Płońska, Mateusz Kurzawski
1Department of Experimental and Clinical Pharmacology, Pomeranian Medical University, Szczecin, Poland.

Insights
The ADRB1 1165C>G and 145A>G gene variations do not impact hemodynamic responses during dobutamine stress echocardiography. This study found no association between these ADRB1 polymorphisms and heart rate or blood pressure changes in Polish patients.
Area of Science:
- Cardiovascular Genetics
- Pharmacogenomics
- Clinical Echocardiography
Background:
- The ADRB1 gene encodes the beta-1 adrenergic receptor, a key regulator of cardiac function.
- Genetic variations in ADRB1 may influence individual responses to cardiovascular medications and stress tests.
- Dobutamine stress echocardiography (DSE) is a standard diagnostic tool for assessing cardiac function under stress.
Purpose of the Study:
- To investigate the association between ADRB1 1165C>G and 145A>G polymorphisms and hemodynamic responses during DSE.
- To determine if these specific ADRB1 gene variants affect heart rate (HR) and blood pressure (BP) changes in response to dobutamine.
- To analyze the impact of these polymorphisms on patients requiring atropine during DSE.
Main Methods:
- Genotyping of ADRB1 1165C>G and 145A>G polymorphisms using PCR-restriction fragment length polymorphism.
- Inclusion of 144 patients with clinical indications for DSE.
- Monitoring of hemodynamic parameters (HR, systolic BP, diastolic BP) throughout the DSE procedure.
Main Results:
- No significant differences in HR, systolic BP, or diastolic BP were observed between different genotypes of ADRB1 1165C>G and 145A>G.
- The magnitude of hemodynamic response (e.g., change in HR) to dobutamine was comparable across all analyzed genotypes.
- These findings held true even for the subgroup of patients who required atropine during DSE.
Conclusions:
- The studied ADRB1 1165C>G and 145A>G polymorphisms are not associated with hemodynamic responses to dobutamine.
- These genetic variations do not appear to influence HR, SBP, or DBP changes during diagnostic DSE in the studied Polish Caucasian population.
- The results suggest that routine genotyping for these specific ADRB1 polymorphisms may not be necessary for predicting DSE outcomes.
Purpose:
The aim of this study was to determine an association between the ADRB1 1165C>G and 145A>G polymorphisms and hemodynamic response [heart rate (HR), systolic (SBP) and diastolic (DBP) blood pressure] to dobutamine during dobutamine stress echocardiography (DSE).
Methods:
The study involved 144 patients with clinical indications for DSE. The PCR-restriction fragment length polymorphism method was used to identify the ADRB1 1165C>G and 145A>G polymorphisms.
Results:
Heart rate during DSE increased in all analyzed study groups. Patients with the ADRB1 1165CC and 1165CG+GG polymorphisms demonstrated similar HR, including magnitude of response [change in heart rate (ΔHR 0-30): 42.1 ± 17.5 vs. 46.1 ± 15.5 bpm, respectively]. HR and ΔHR 0-30 were comparable in ADRB1145AA and 145AG subjects in the course of DSE. SBP and DBP at all stages of DSE were similar in subjects with either polymorphism and did not differentiate patients with the ADRB1 145AA polymorphism from those with the ADRB1 145AG polymorphism, nor those with the ADRB1 1165CC polymorphism from those with the ADRB1 1165CG+GG polymorphism. No differences were noted in the magnitude of response, with the increase in SBP and DBP comparable in all genotypes. Similar observations were made in patients (25/144 studied) with atropine requirements during DSE.
Conclusion:
The ADRB1 1165C>G and 145A>G polymorphisms are not associated with the HR, SBP and DBP responses in Polish Caucasian patients requiring diagnostic dobutamine stress echocardiography.
Related Concept Videos
 01:26
Adrenergic Receptors: β Subtype
Isoprenaline > Adrenaline > Noradrenaline
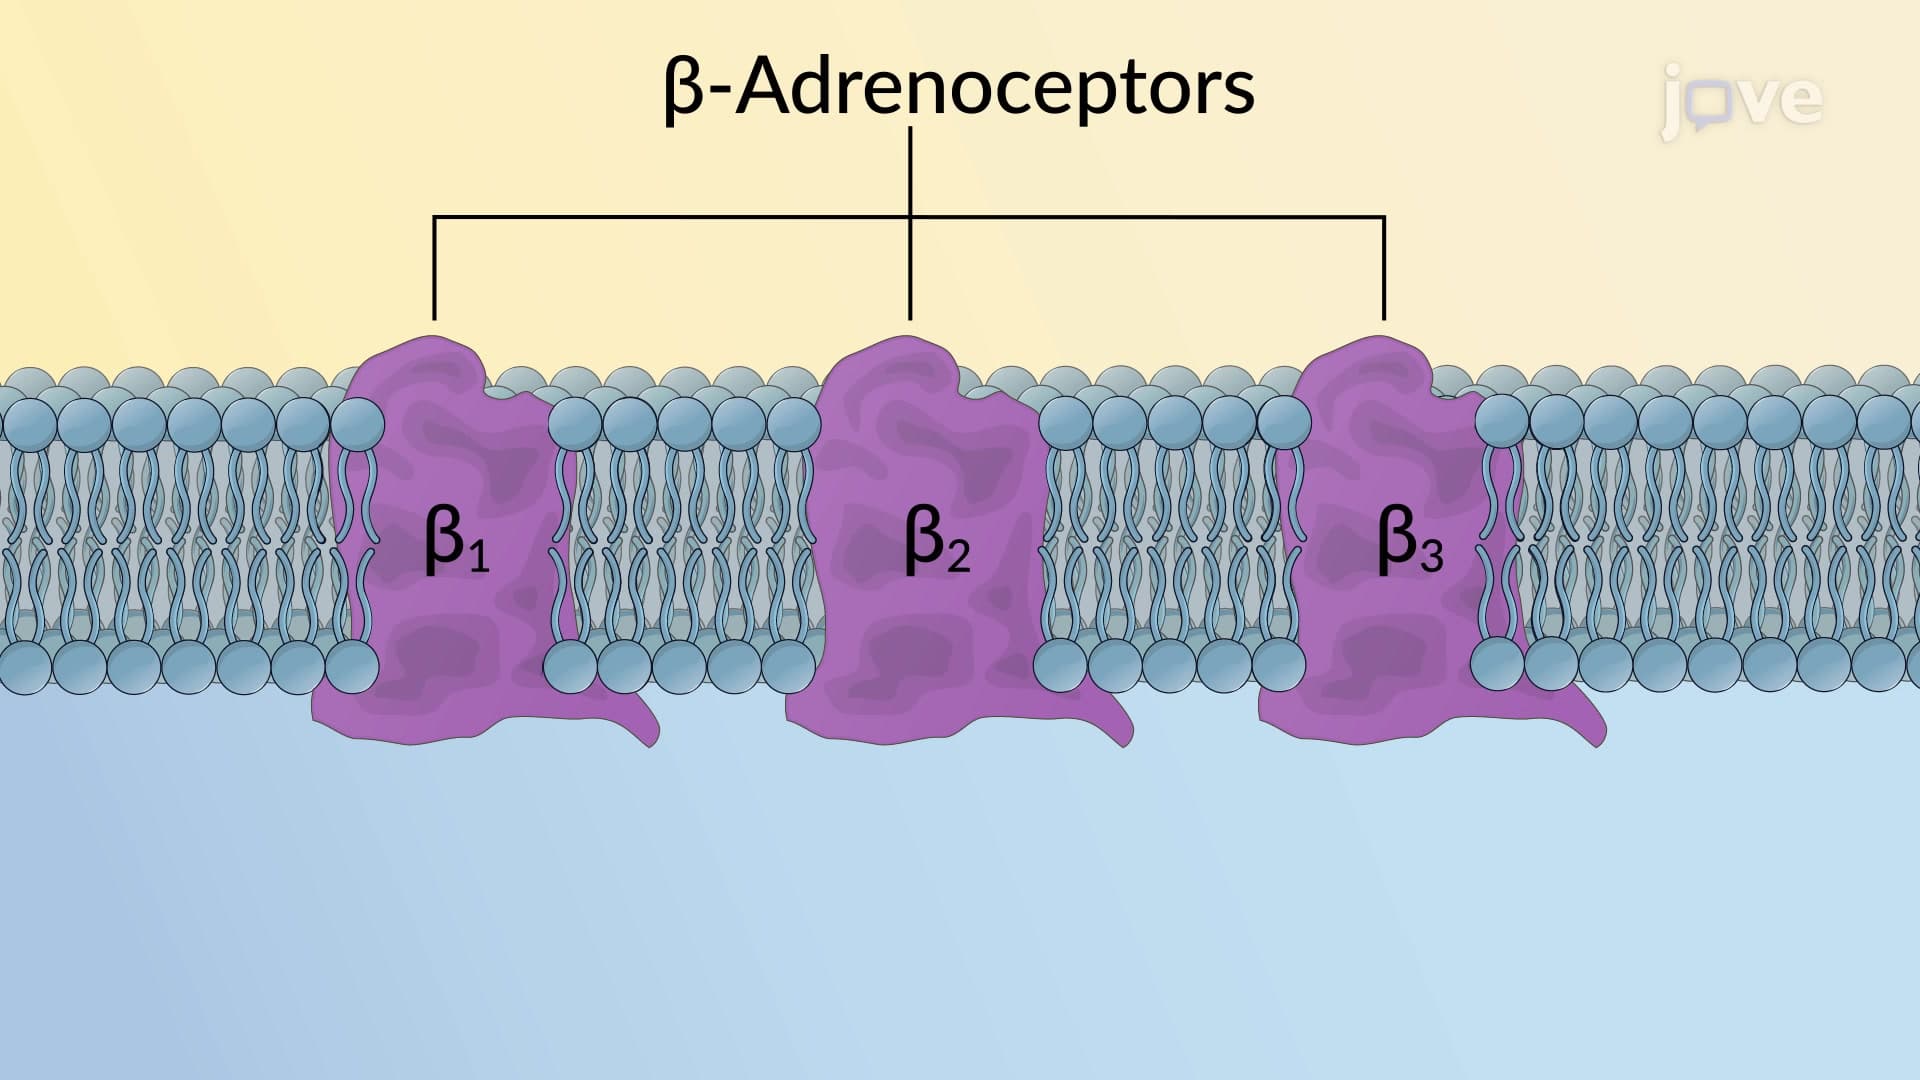
Neurotransmitter binding to these receptors causes activation of adenylyl cyclase resulting in increased concentrations of cAMP and modulation of calcium ion channels within the cell. They are further classified into β1, β2, and β3 subtypes.
β1-adrenoceptors: β1-adrenoceptors have equal affinities for...
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:29
Heart Failure II: Pathophysiology
 01:22
Heart Failure Drugs: β-Blockers
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:31
Adrenergic Receptors: ɑ Subtype
Adrenaline ≥ Noradrenaline >> Isoprenaline
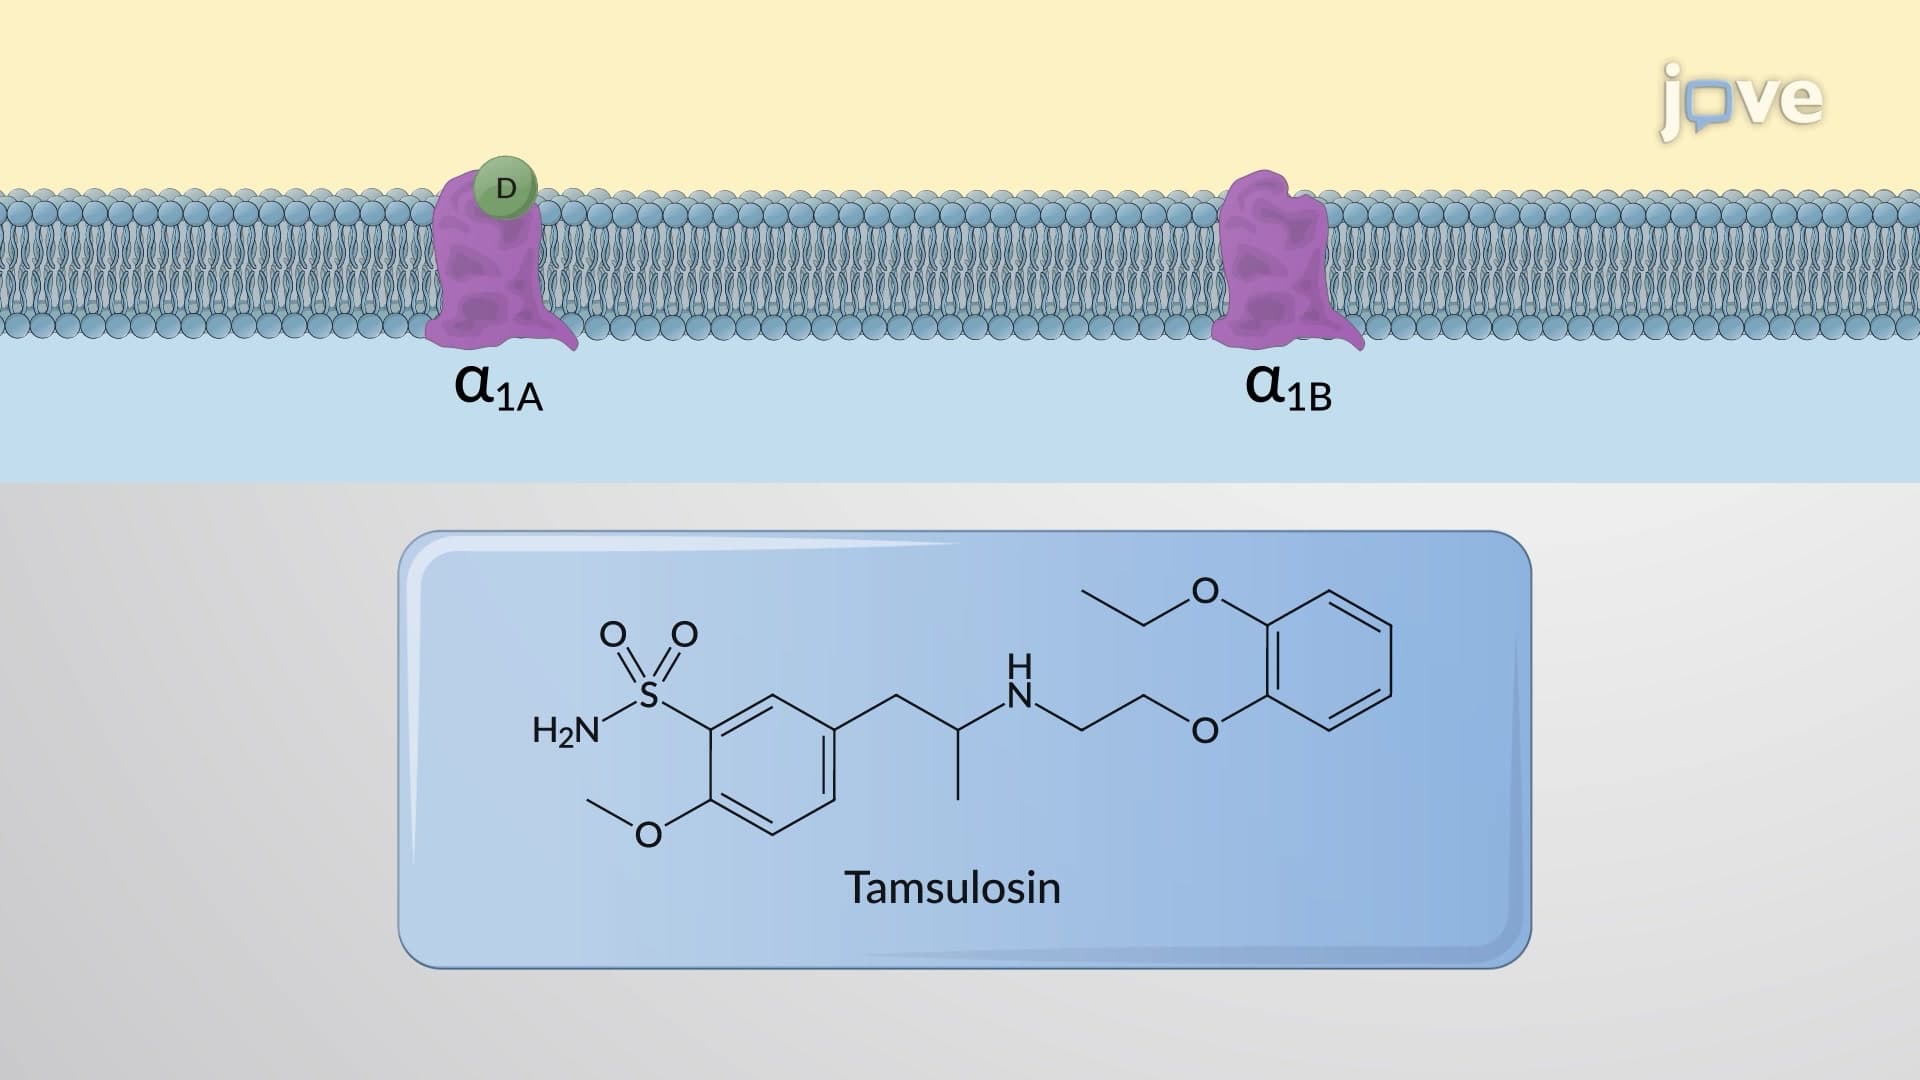
α-adrenoceptors are further divided into α1 and α2-adrenoceptors.
α1-Adrenoceptors: These receptors are located postsynaptically on the effector organs and cause constriction of smooth muscle mediated by activation of phospholipase C—inositol-1,4,5-trisphosphate...