Related Experiment Video
Updated: Jun 4, 2026
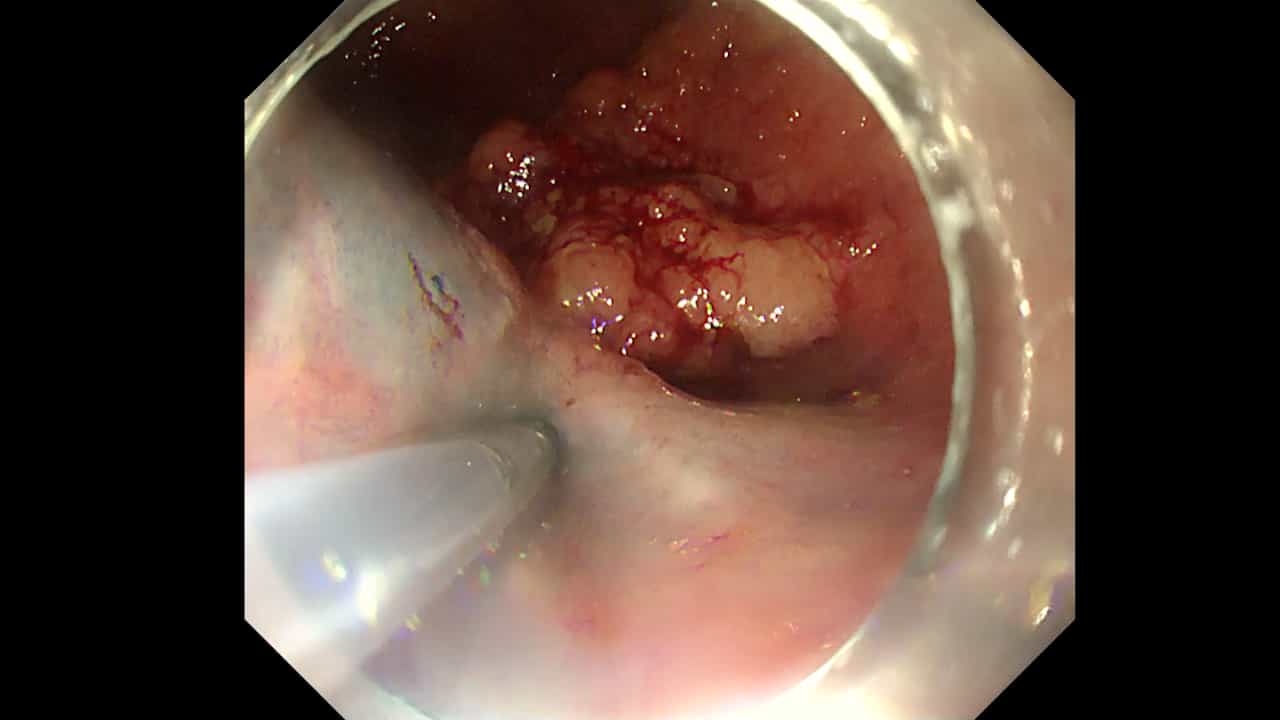

The Pocket-Creation Procedure of Endoscopic Submucosal Dissection for Large Rectal Laterally Spreading Tumors
Published on: February 13, 2026
Feasibility of salvage endoscopic mucosal resection by using a cap for remnant rectal carcinoids after primary EMR
Soung Min Jeon1, Jin Ha Lee, Sung Pil Hong
1Department of Internal Medicine and Institute of Gastroenterology, Yonsei University College of Medicine, Seoul, South Korea.

Background:
Secondary endoscopic treatment for remnant lesions of rectal carcinoid tumors after primary EMR or polypectomy is technically difficult because of fibrosis of residual tissues. EMR by using a cap (EMR-C), a method to resect the submucosal layer by suction by using a transparent cap, may be feasible as a salvage treatment.
Objective:
To assess the feasibility of salvage EMR-C.
Design:
Retrospective analysis.
Setting:
Tertiary academic health care system.
Patients:
Thirty-one patients who were referred for salvage treatment of a failed en bloc excision of rectal carcinoid tumors after primary EMR or polypectomy between January 2007 and December 2009.
Interventions:
Salvage EMR-C for remnant carcinoid tumors in the rectum.
Main Outcome Measurements:
Rate of complete resection, complications, length of procedure, and recurrence rate.
Results:
The mean age of the patients was 52.0±11.8 years (range 30-78 years). The mean tumor size was 8.9±3.2 mm (range 5.0-13.0 mm). The mean procedure time was 9.1±3.7 minutes, and clear resection margins were pathologically confirmed in all 31 patients. The most common complication of salvage EMR-C was bleeding (7 patients, 22.6%), which was successfully treated by hemoclipping in all cases. The 1-year follow-up colonoscopy and CT results for all patients were negative for recurrence.
Limitations:
Retrospective design and limited cases at a single center.
Conclusions:
EMR-C is a feasible salvage therapeutic option for failed en bloc excision after primary endoscopic treatment of rectal carcinoid tumors.