Related Experiment Video
Updated: Jun 4, 2026

Single-Port Robotic-assisted Transaxillary Breast-conserving Surgery: A Prospective, Single-arm, Non-randomized Phase IIa Clinical Trial
Published on: August 19, 2025
Systematic review of radioguided surgery for non-palpable breast cancer
P J Lovrics1, S D Cornacchi, R Vora
1Department of Surgery, McMaster University, Hamilton Health Sciences and St. Joseph's Healthcare Hamilton, Hamilton, ON, Canada. lovricsp@mcmaster.ca

Background:
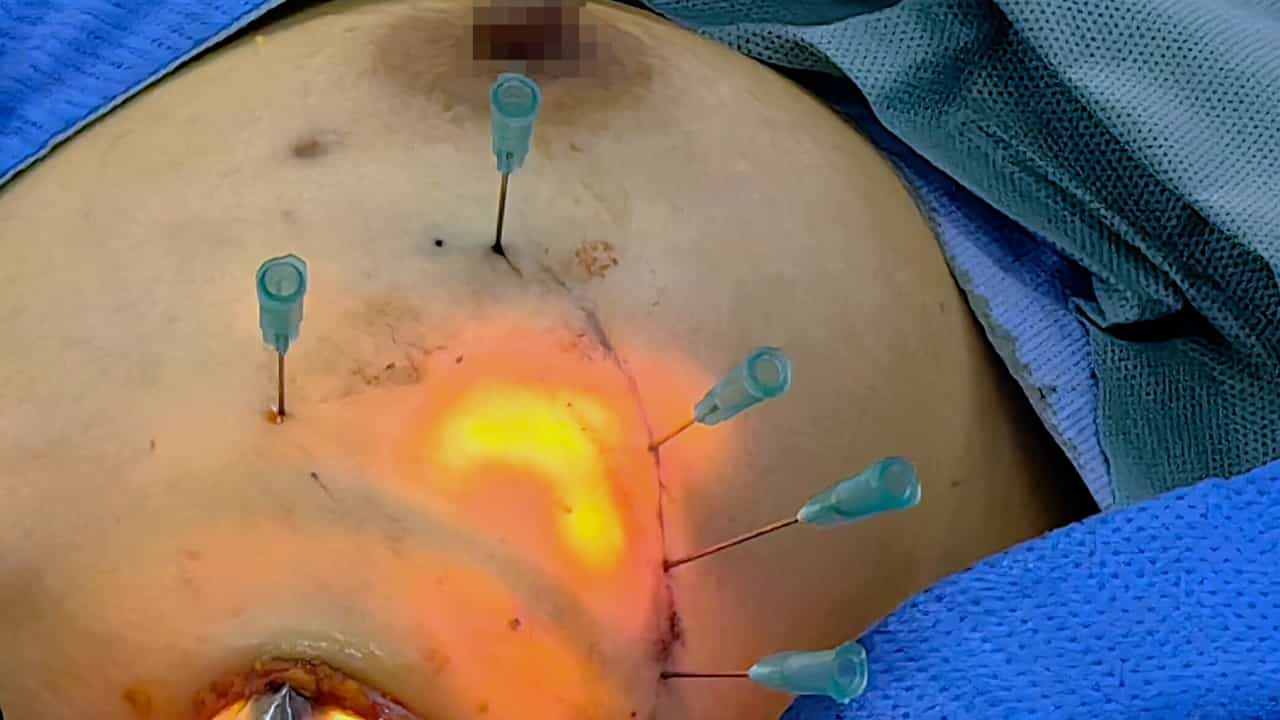
This systematic review examines whether radioguided localization surgery (RGL) (radioguided occult lesion localization - ROLL and radioguided seed localization - RSL) for non-palpable breast cancer lesions produces lower positive margin rates than standard wire-guided localization surgery.
Methods:
We performed a comprehensive literature review to identify clinical studies using either ROLL or RSL. Included studies examined invasive or in situ BC and reported pathologically assessed margin status or specimen volume/weight. Two reviewers independently assessed study eligibility and quality and abstracted relevant data on patient and surgical outcomes. Quantitative data analyses were performed.
Results:
Fifty-two clinical studies on ROLL (n = 46) and RSL (n = 6) were identified. Twenty-seven met our inclusion criteria: 12 studies compared RGL to WGL and 15 studies were single cohorts using RGL. Ten studies were included in the quantitative analyses. Data for margin status and re-operation rates from 4 randomized controlled trials (RCT; n = 238) and 6 cohort studies were combined giving a combined odds ratio (OR) of 0.367 and 95% confidence interval (CI): 0.277 to 0.487 (p < 0.001) for margins status and OR 0.347, 95% CI: 0.250 to 0.481 (p < 0.001) for re-operation rates.
Conclusions:
The results of this systematic review of RGL versus WGL demonstrate that RGL technique produces lower positive margins rates and fewer re-operations. While this review is limited by the small size and quality of RCTs, the odds ratios suggest that RGL may be a superior technique to guide surgical resection of non-palpable breast cancers. These results should be confirmed by larger, multi-centered RCTs.
