Related Experiment Video
Updated: Jun 4, 2026
Cytosolic Calcium Measurements in Renal Epithelial Cells by Flow Cytometry
Published on: October 28, 2014
Calcium mass balances during standard bicarbonate hemodialysis and long-hour slow-flow bicarbonate hemodialysis
Carlo Basile1, Pasquale Libutti, Anna Lucia Di Turo
1Miulli General Hospital, Acquaviva delle Fonti, Italy. basile.miulli@libero.it

Background:
Dialysate calcium (Ca) concentration should be viewed as part of the integrated therapeutic regimen to control renal osteodystrophy and maintain normal mineral metabolism. Thus, a correct ionized calcium mass balance (Ca++MB) during hemodialysis (HD) is crucial in the treatment of renal osteodystrophy. The GENIUS single-pass batch dialysis system (Fresenius Medical Care, Germany) consists of a closed dialysate tank of 90 L; it offers the opportunity of effecting mass balances of any solute in a very precise way.
Methods:
The present study has a crossover design: 11 stable anuric HD patients underwent 2 bicarbonate HD sessions, 1 of 4 hours (4h) and the other of 8 hours (8h) in a random sequence, always at the same interdialytic interval, at least 1 week apart. The GENIUS system and high-flux FX80 dialyzers (Fresenius Medical Care, Germany) were used. The volume of blood and dialysate processed, volume of ultrafiltration and dialysate Ca concentrations (1.50 mmol/L) were prescribed to be the same. Trends of plasma Ca++, blood pH and bicarbonates during dialysis, as well as Ca++MBs were determined. Plasma parathyroid hormone (PTH) levels at the start and end of the 2 treatments were measured.
Results:
Ca++MBs (mean ± SD) were +284.6 ± 137.4 mg and +297.7 ± 131.6 mg (p=0.307) in the 4h and 8h treatments, respectively. No single session out of the 22 had a negative Ca++MB for the patient. Mean plasma Ca++, blood pH and bicarbonate levels were not statistically significantly different when comparing the start and end of the sessions of the 2 treatments. Mean plasma Ca++, blood pH and bicarbonate levels increased significantly along the time points in both 4h and 8h HD sessions (repeated measures ANOVA: p<0.0001). Mean plasma PTH levels were not statistically significantly different when comparing the start and end of the sessions of the 2 treatments. The differences between predialysis and postdialysis plasma PTH levels were not statistically significantly different either in 4h or 8h sessions (Wilcoxon's test: p=NS), even though a trend toward lower postdialysis plasma PTH levels was observed in both 4h and 8h treatments.
Conclusions:
Our data show incontrovertibly that, when dialyzing with a dialysate Ca concentration of 1.50 mmol/L, 4h standard bicarbonate HD and 8h slow-flow bicarbonate HD always achieve a quite similar positive Ca++MB for the patients.
Related Concept Videos
 01:25
Hemodialysis III: Nursing Management
 01:24
Hemodialysis II: Procedure and Complications
 01:22
Bicarbonate-Carbonic Acid Buffer
 01:29
Roles of Electrolytes: Chloride and Bicarbonate
Conditions such as hypochloremia can arise from insufficient chloride reabsorption by the kidneys, often compounded by extended bouts of diarrhea, vomiting, or...
 01:29
Renal Regulation of Acid-Base Balance
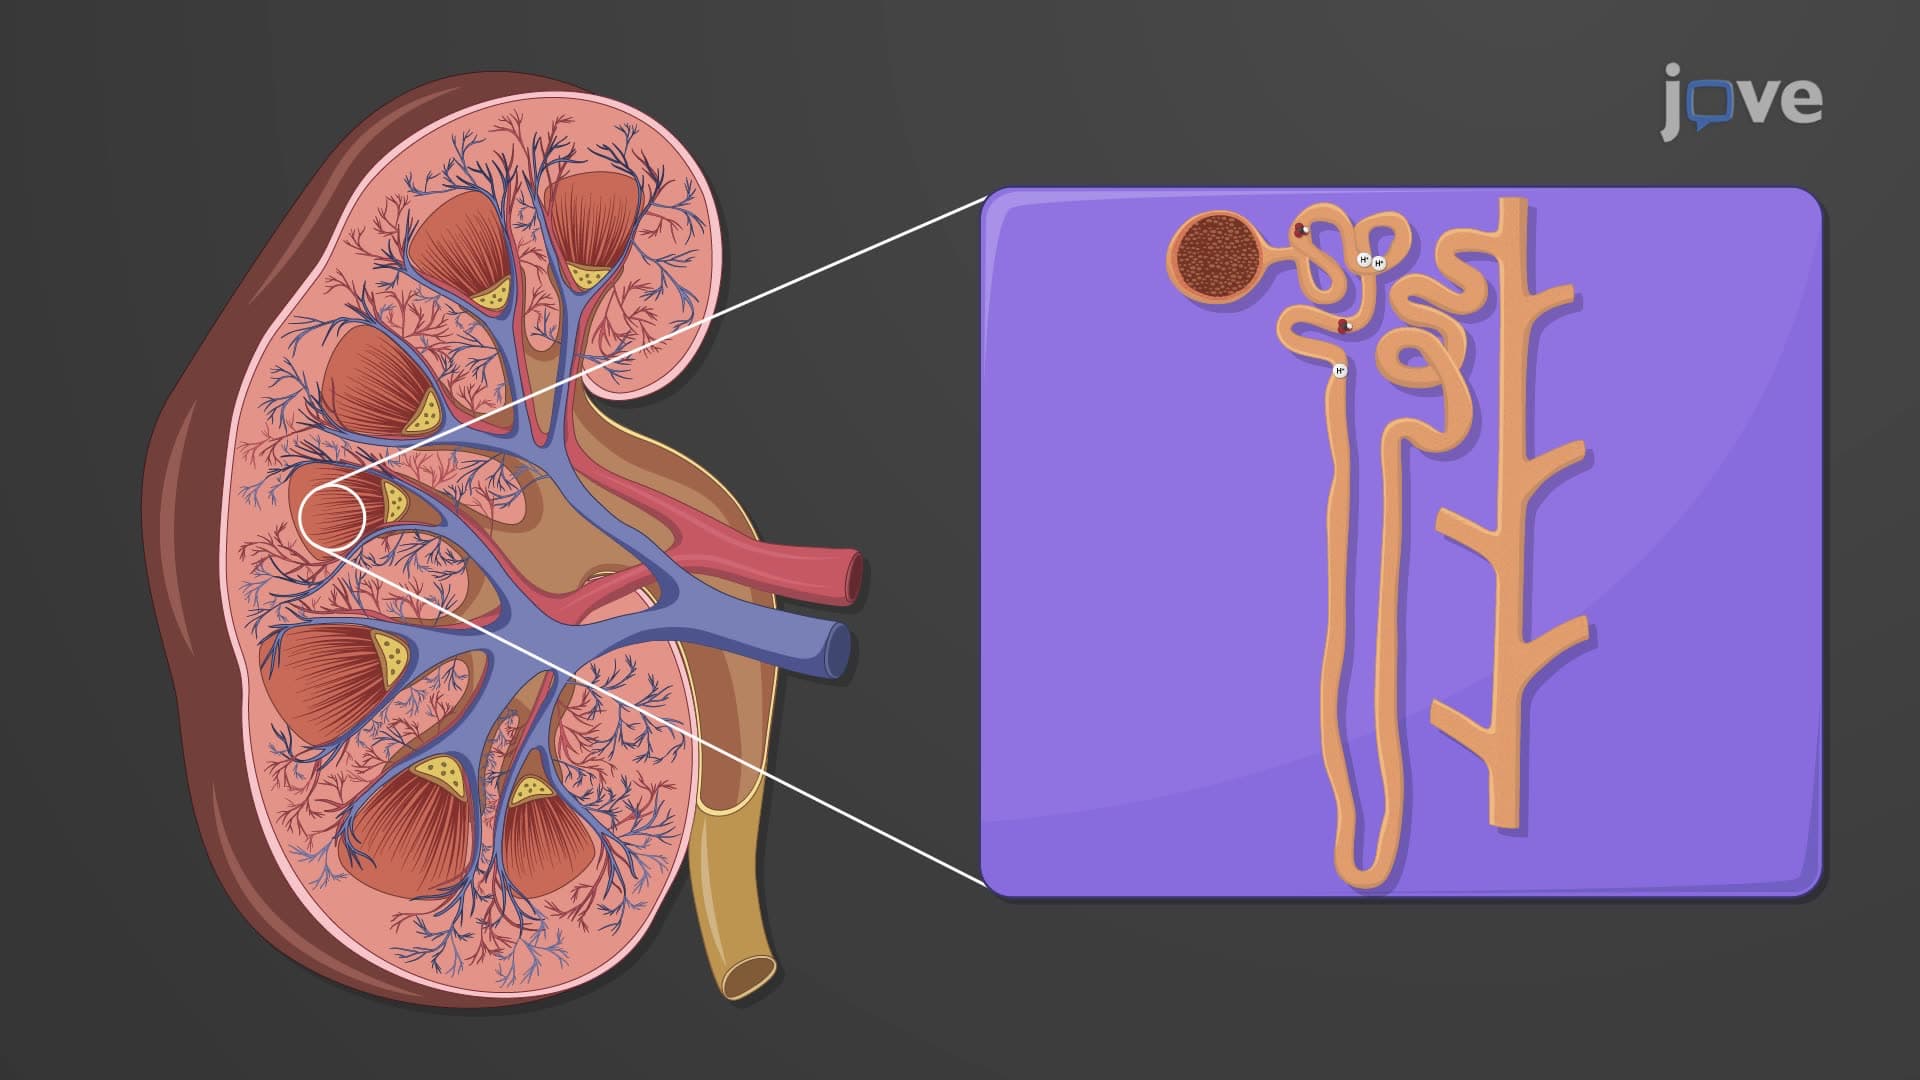
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...
 01:21
Skeleton and Calcium Homeostasis