Related Experiment Video
Updated: Jun 4, 2026
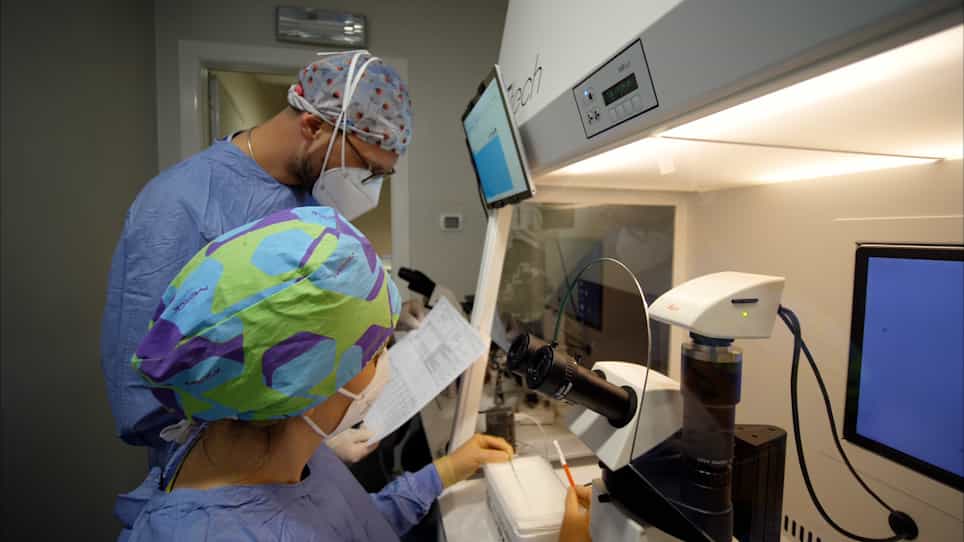
Fertility Preservation Through Oocyte Vitrification: Clinical and Laboratory Perspectives
Published on: September 16, 2021
Differences between the non-steroidal aromatase inhibitors anastrozole and letrozole--of clinical importance?
1Institute of Clinical Medicine, University of Oslo, Faculty Division at Akershus University Hospital, Sykehusveien 27, Lørenskog N-1478, Norway. juergen.geisler@medisin.uio.no

Abstract:
Aromatase inhibition is the gold standard for treatment of early and advanced breast cancer in postmenopausal women suffering from an estrogen receptor-positive disease. The currently established group of anti-aromatase compounds comprises two reversible aromatase inhibitors (anastrozole and letrozole) and on the other hand, the irreversible aromatase inactivator exemestane. Although exemestane is the only widely used aromatase inactivator at this stage, physicians very often have to choose between either anastrozole or letrozole in general practice. These third-generation aromatase inhibitors (letrozole/Femara (Novartis Pharmaceuticals, Basel, Switzerland) and anastrozole/Arimidex (AstraZeneca, Pharmaceuticals, Macclesfield, Cheshire, UK)), have recently demonstrated superior efficacy compared with tamoxifen as initial therapy for early breast cancer improving disease-free survival. However, although anastrozole and letrozole belong to the same pharmacological class of agents (triazoles), an increasing body of evidence suggests that these aromatase inhibitors are not equipotent when given in the clinically established doses. Preclinical and clinical evidence indicates distinct pharmacological profiles. Thus, this review focuses on the differences between the non-steroidal aromatase inhibitors allowing physicians to choose between these compounds based on scientific evidence. Although we are waiting for the important results of a still ongoing head-to-head comparison in patients with early breast cancer at high risk for relapse (Femara Anastrozole Clinical Evaluation trial; 'FACE-trial'), clinicians have to make their choices today. On the basis of available evidence summarised here and until FACE-data become available, letrozole seems to be the best choice for the majority of breast cancer patients whenever a non-steroidal aromatase inhibitor has to be chosen in a clinical setting. The background for this recommendation is discussed in the following chapters.
Insights
Letrozole and anastrozole are third-generation aromatase inhibitors used for estrogen receptor-positive breast cancer. Evidence suggests letrozole may be a better choice than anastrozole for most patients.
Area of Science:
- Oncology
- Pharmacology
Background:
- Aromatase inhibitors are standard treatment for postmenopausal women with estrogen receptor-positive breast cancer.
- Current options include reversible inhibitors (anastrozole, letrozole) and irreversible inactivator (exemestane).
- Anastrozole and letrozole, both triazoles, have shown superior efficacy to tamoxifen in early breast cancer.
Purpose of the Study:
- To review the differences between non-steroidal aromatase inhibitors, anastrozole and letrozole.
- To provide evidence-based guidance for physicians choosing between these agents.
- To discuss the distinct pharmacological profiles of anastrozole and letrozole.
Main Methods:
- Review of preclinical and clinical evidence comparing anastrozole and letrozole.
- Analysis of pharmacological profiles and clinical efficacy data.
- Discussion of ongoing head-to-head trials like the FACE-trial.
Main Results:
- Evidence suggests anastrozole and letrozole are not equipotent despite similar clinical doses.
- Distinct pharmacological profiles exist between these two non-steroidal aromatase inhibitors.
- Letrozole appears to be the preferred choice for most breast cancer patients based on current data.
Conclusions:
- Physicians must choose between anastrozole and letrozole based on available scientific evidence.
- While awaiting definitive head-to-head trial results, letrozole is recommended for most patients.
- Understanding the differences in efficacy and pharmacology is crucial for optimal breast cancer treatment.
More Related Videos
 07:25
A Bioluminescent and Fluorescent Orthotopic Syngeneic Murine Model of Androgen-dependent and Castration-resistant Prostate Cancer
Published on: March 6, 2018
 06:18
An In Vivo Estrogen Deficiency Mouse Model for Screening Exogenous Estrogen Treatments of Cardiovascular Dysfunction After Menopause
Published on: August 13, 2019
Related Concept Videos
 01:11
Pharmacogenetics of Drug Targets: β₂-Adrenergic Receptors, Apo E, Thymidylate Synthase
 01:22
Pharmaceutical Alternatives: Stability-Related Therapeutic Nonequivalence
 01:22
Adrenergic Antagonists: Pharmacological Actions of ɑ-Receptor Blockers
α1-blockers: These drugs inhibit α1-adrenoceptors on smooth muscle cells, resulting in vasodilation. This vasodilation lowers blood pressure, making α1-blockers valuable in treating hypertension. Additionally, α1-blockers effectively address urinary obstruction...
 01:25
Dose-Response Relationship: Selectivity and Specificity
 01:31
Adrenergic Antagonists: ɑ and β-Receptor Blockers
 01:24
Tissue-Drug Binding: Localization of Drugs and its Significance
Drugs can bind to different tissue components, enhancing their distribution and localization. The factors influencing drug localization in tissues include the drug's lipophilicity, structural characteristics, tissue perfusion rate, and pH differences. These factors determine the...