Related Experiment Video
Updated: Jun 4, 2026


A Mouse Model of Ankle-Subtalar Complex Joint Instability
Published on: October 28, 2022
Body structure versus body function in haemophilia: the case of haemophilic ankle arthropathy
1Haemostasis and Thrombosis Unit, Cliniques Universitaires Saint-Luc, Université Catholique de Louvain, Brussels, Belgium. Sebastien.lobet@uclouvain.be

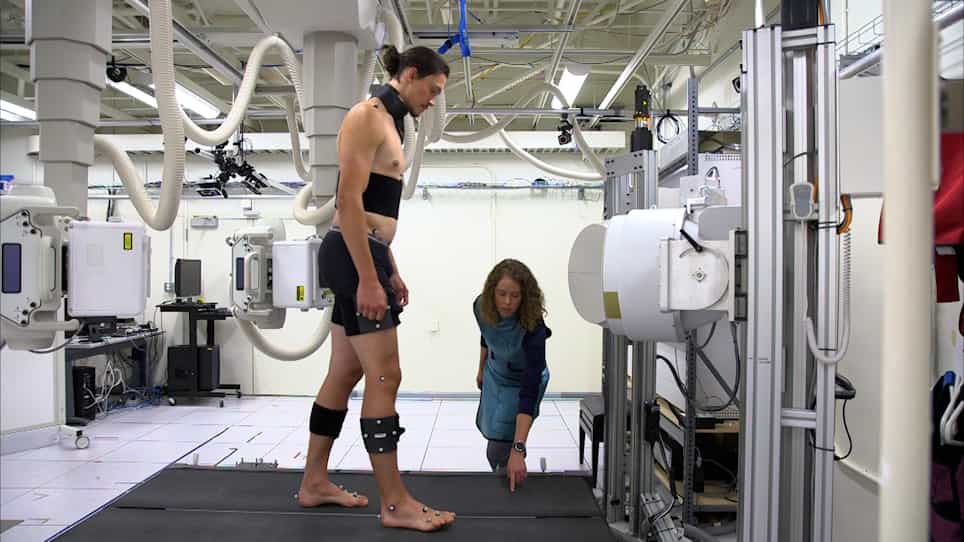
Imaging and clinical scores are the main tools used to evaluate the progression of haemophilic arthropathy (HA). Based on haemophilic ankle arthropathy, this study aimed to explore the concordances between structural and clinical alterations, determined by standard radiological and clinical scores, and functional alterations assessed by three-dimensional gait analysis (3DGA). In total, 21 adult haemophilia patients underwent extensive ankle evaluation using the physical examination part of the World Federation of Haemophilia joint score, the Arnold-Hilgartner and the Pettersson radiological scores, and self-reported ankle function assessment using the revised Foot Function Index. Significant associations were found between self-reported ankle function assessment and the three 3DGA variables representative of joint function (range of motion, peak plantar flexion moment, and peak power generated at the push-off phase). Radiological and clinical scores were compared with ankle muscle peak power measurement, the most reliable 3DGA gait variable for ankle function. No significant associations were found between both clinical and functional scores and the 3DGA functional assessment. This discordance may be explained by the lack of a direct relationship between functional alterations detected by 3DGA and the structural changes assessed using X-ray or clinical scoring. Another explanation may be the limitation of clinical and radiological scoring systems in properly determining the severity of HA. Functional assessments such as 3DGA should be used more frequently when monitoring the progression of ankle arthropathy or the effects of therapeutic interventions in adult haemophilia patients.
Imaging and clinical scores are the main tools used to evaluate the progression of haemophilic arthropathy (HA). Based on haemophilic ankle arthropathy, this study aimed to explore the concordances between structural and clinical alterations, determined by standard radiological and clinical scores, and functional alterations assessed by three-dimensional gait analysis (3DGA). In total, 21 adult haemophilia patients underwent extensive ankle evaluation using the physical examination part of the World Federation of Haemophilia joint score, the Arnold-Hilgartner and the Pettersson radiological scores, and self-reported ankle function assessment using the revised Foot Function Index. Significant associations were found between self-reported ankle function assessment and the three 3DGA variables representative of joint function (range of motion, peak plantar flexion moment, and peak power generated at the push-off phase). Radiological and clinical scores were compared with ankle muscle peak power measurement, the most reliable 3DGA gait variable for ankle function. No significant associations were found between both clinical and functional scores and the 3DGA functional assessment. This discordance may be explained by the lack of a direct relationship between functional alterations detected by 3DGA and the structural changes assessed using X-ray or clinical scoring. Another explanation may be the limitation of clinical and radiological scoring systems in properly determining the severity of HA. Functional assessments such as 3DGA should be used more frequently when monitoring the progression of ankle arthropathy or the effects of therapeutic interventions in adult haemophilia patients.
Related Concept Videos
 01:10
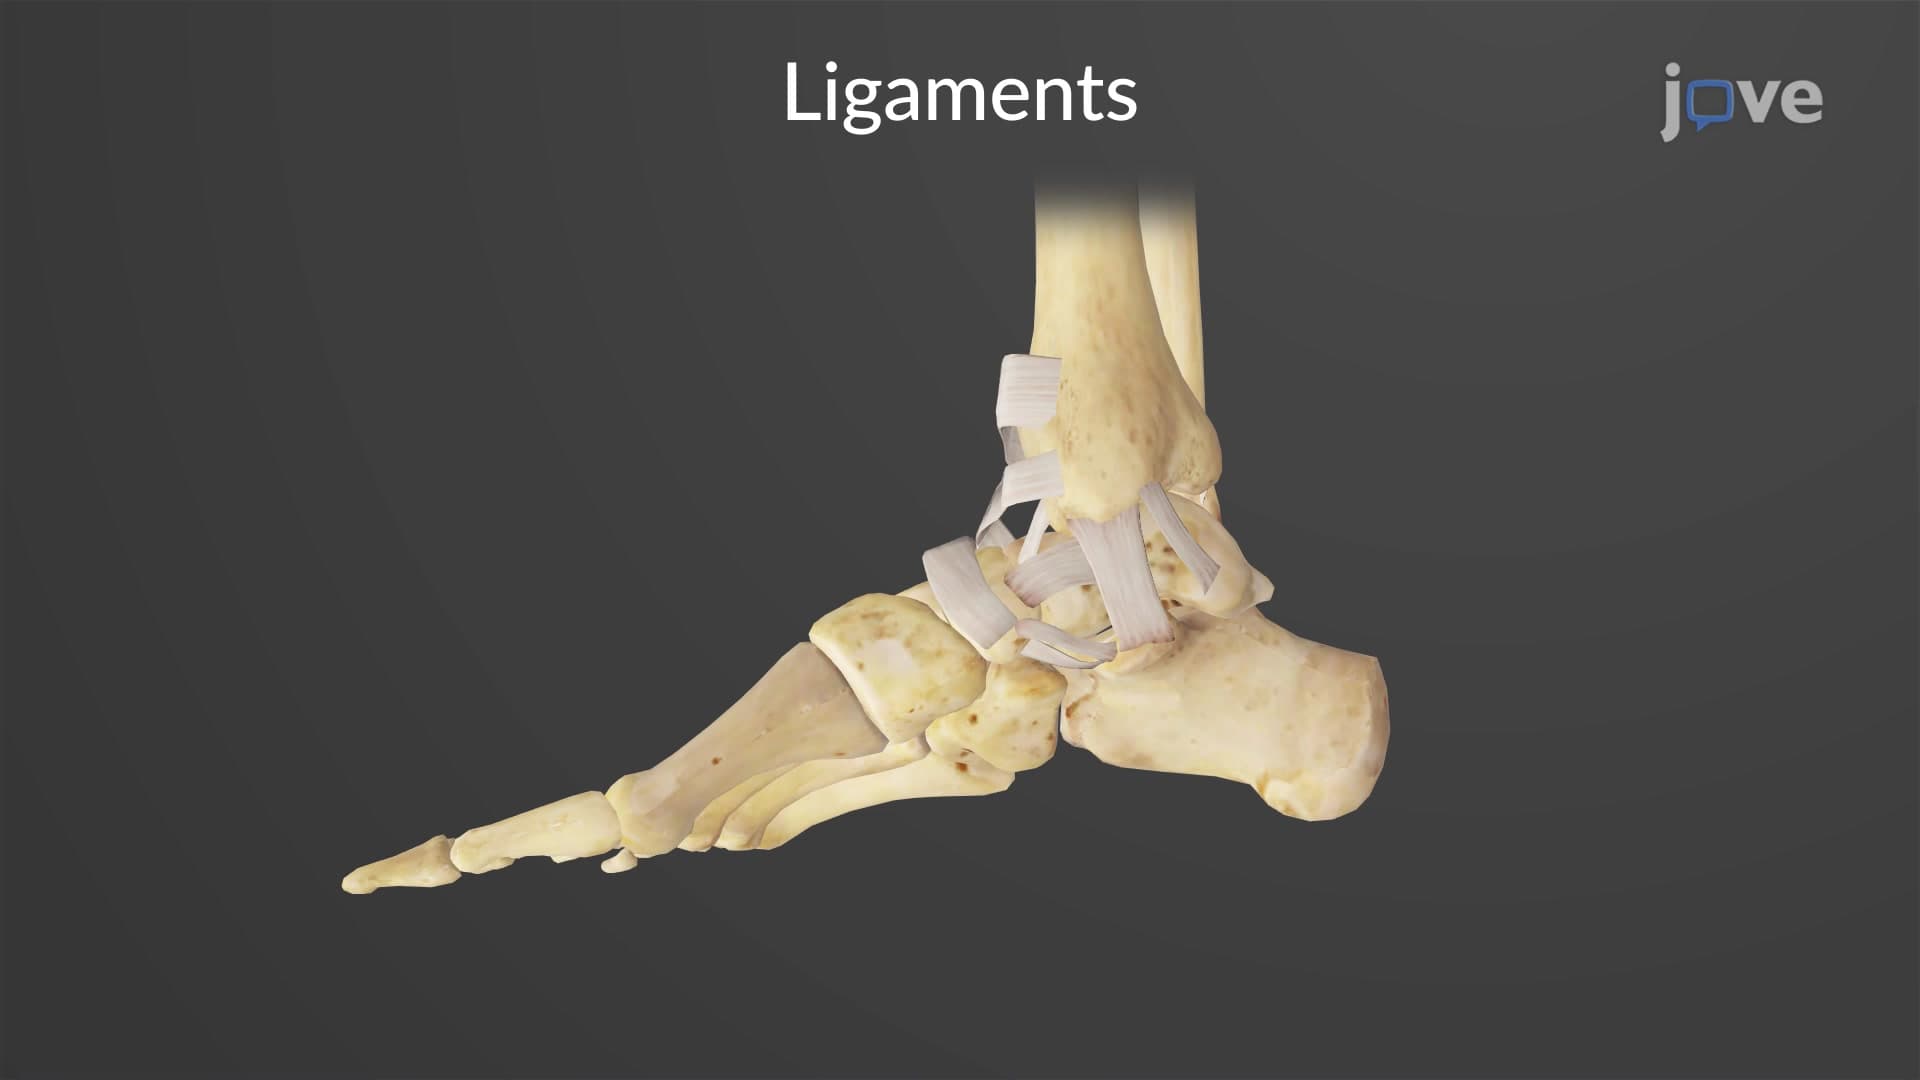
Ankle Joint
 01:09
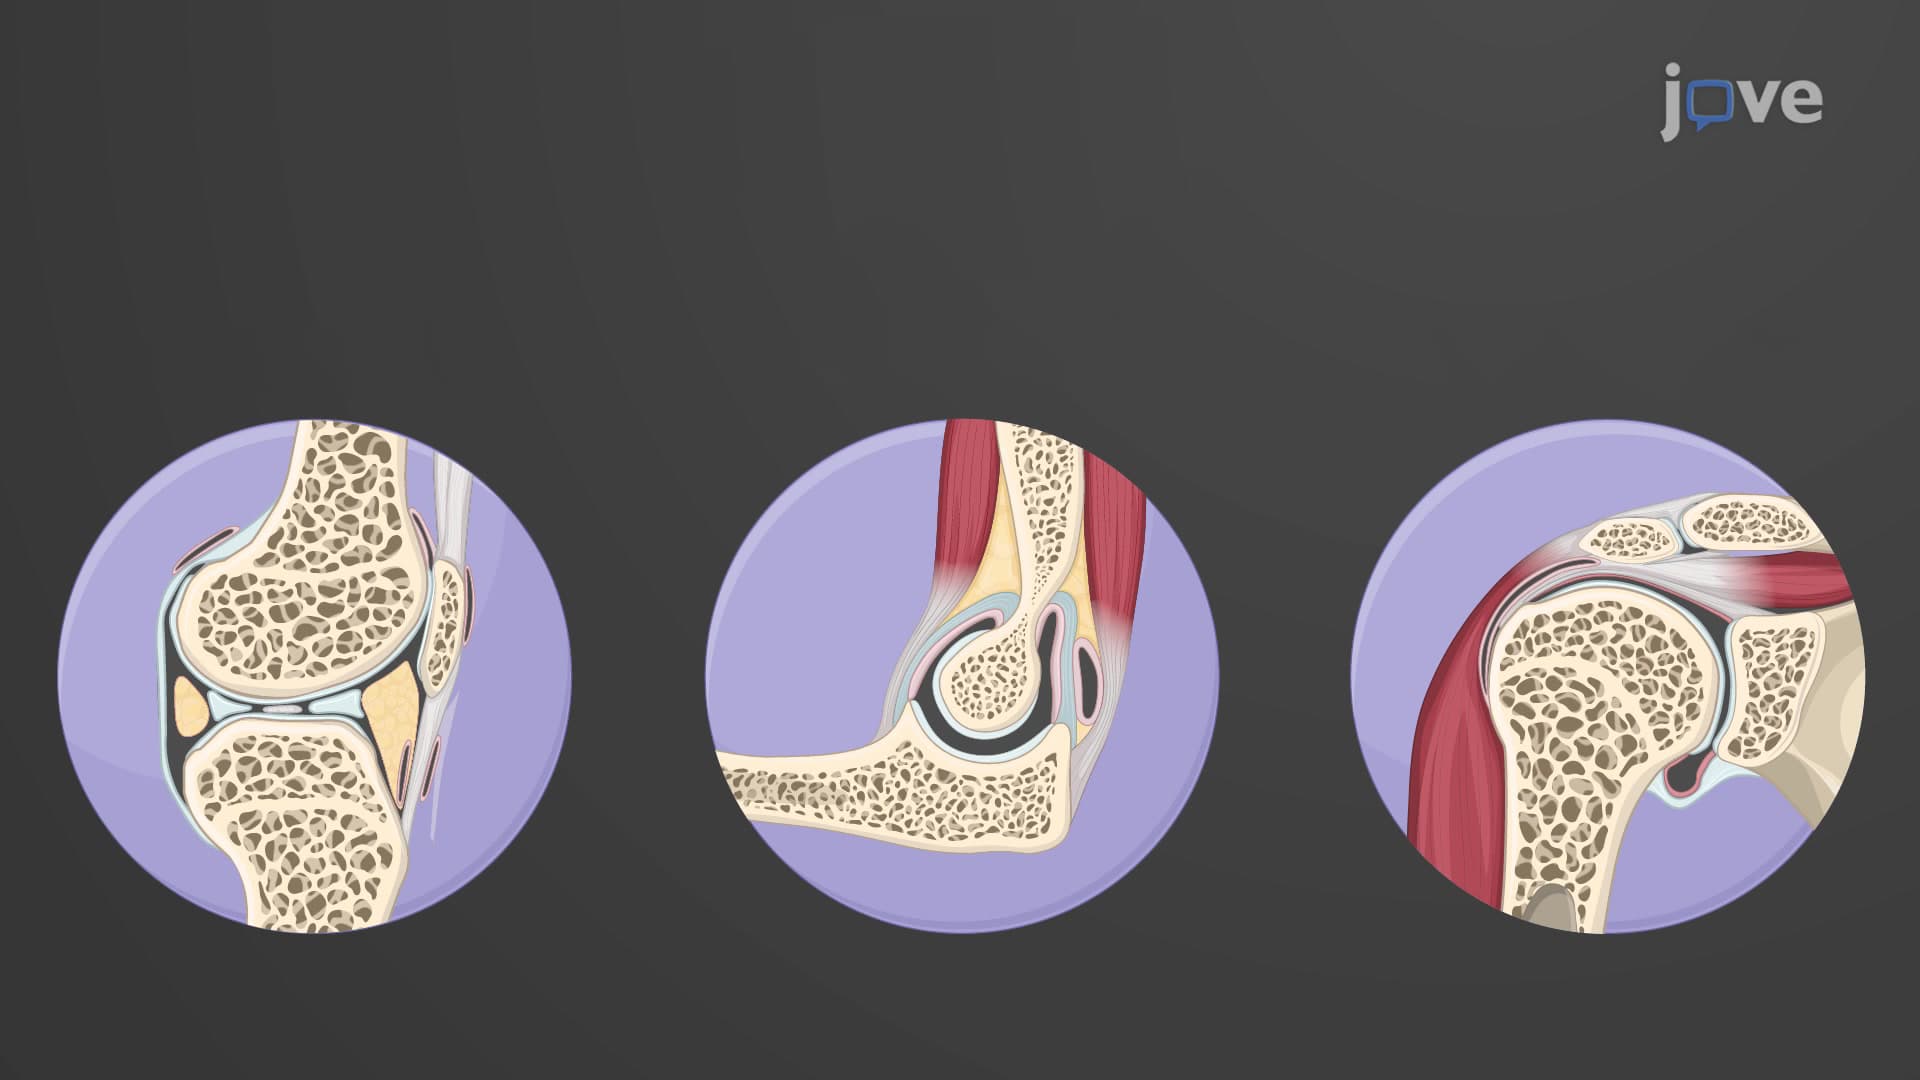
Functional Classification of Joints
The functional classification of joints is determined by the amount of mobility between the adjacent bones. Joints are functionally classified as a synarthrosis or immobile joint, an amphiarthrosis or slightly moveable joint, or as a diarthrosis, a freely moveable joint. Fibrous and cartilaginous joints can be functionally classified as either synarthroses or amphiarthroses, whereas all synovial joints are classified as diarthroses.
Synarthrosis
An immobile...
 01:10
Bones of the Lower Limb: Tibia and Fibula
 00:58
Introduction to Joints
 01:22
The Functions of the Skeletal System
 01:16
Structural Joints: Synovial Joints