Related Experiment Video
Updated: Jun 3, 2026


Methods for Quantitative Detection of Antibody-induced Complement Activation on Red Blood Cells
Published on: January 29, 2014
[Atypical hemolytic-uremic syndrome related to abnormalities within the complement system]
V Frémeaux-Bacchi1, F Fakhouri, L Roumenina
1Service d'immunologie biologique, hôpital Européen Georges-Pompidou, Assistance publique-Hôpitaux de Paris, 20-40, rue Leblanc, 75908 Paris cedex 15, France. veronique.fremeaux-bacchi@egp.aphp.fr

Hemolytic uremic syndrome (HUS) is a thrombotic microangiopathy (TMA) disorder characterised by the association of haemolytic anaemia, thrombocytopenia and acute renal failure. Atypical forms (non-shigatoxin related forms) may be familial or sporadic, frequently with relapses and most of them lead to end stage renal failure. During the last years, different groups have demonstrated genetic predisposition to atypical HUS (aHUS) involving five genes encoding for complement components which play a role in the activation or control of the alternative pathway: encoding factor H (CFH), accounting for 30% of aHUS; CD46 (encoding membrane cofactor protein [MCP]) accounting for approximately 10% of aHUS; CFI (encoding factor I) accounting for an estimated 5-15% of patients; C3 (encoding C3) accounting for approximately 10% of aHUS; and rarely CFB (encoding factor B). Predisposition to aHUS is inherited with incomplete penetrance. It is admitted that mutations confer a predisposition to develop aHUS rather than directly causing the disease and that a second event (genetic or environmental) is required for disease manifestation. HUS onset follows a triggering event in most cases (frequently banal seasonal infection and pregnancy). Uncontrolled C3 convertase leads to increased deposition of C3b on vascular endothelium and participates to the prothrombotic state. The phenotype of aHUS is variable ranging from mild forms, with complete recovery of renal function to severe forms with end stage renal disease within the first year after the onset. Overall, the outcome is severe with a mortality rate of 10% and with more than 60% of patients on dialysis. The most severe prognosis was in the CFH mutation group. There is a high risk of recurrence of the disease after renal transplantation in patients with mutations in CFH, CFI, CFB and C3. Plasma therapy may allow complete haematological remission but frequently with persistent renal damage. Some patients are plasma resistant and some are plasma dependent. The recent progress in the determination of the susceptibility factors for aHUS, have allowed to propose new diagnostic tests including a molecular genetic testing and may permit to consider some new specific treatments in this disease (human plasma-derived CFH or complement inhibitors).
Hemolytic uremic syndrome (HUS) is a thrombotic microangiopathy (TMA) disorder characterised by the association of haemolytic anaemia, thrombocytopenia and acute renal failure. Atypical forms (non-shigatoxin related forms) may be familial or sporadic, frequently with relapses and most of them lead to end stage renal failure. During the last years, different groups have demonstrated genetic predisposition to atypical HUS (aHUS) involving five genes encoding for complement components which play a role in the activation or control of the alternative pathway: encoding factor H (CFH), accounting for 30% of aHUS; CD46 (encoding membrane cofactor protein [MCP]) accounting for approximately 10% of aHUS; CFI (encoding factor I) accounting for an estimated 5-15% of patients; C3 (encoding C3) accounting for approximately 10% of aHUS; and rarely CFB (encoding factor B). Predisposition to aHUS is inherited with incomplete penetrance. It is admitted that mutations confer a predisposition to develop aHUS rather than directly causing the disease and that a second event (genetic or environmental) is required for disease manifestation. HUS onset follows a triggering event in most cases (frequently banal seasonal infection and pregnancy). Uncontrolled C3 convertase leads to increased deposition of C3b on vascular endothelium and participates to the prothrombotic state. The phenotype of aHUS is variable ranging from mild forms, with complete recovery of renal function to severe forms with end stage renal disease within the first year after the onset. Overall, the outcome is severe with a mortality rate of 10% and with more than 60% of patients on dialysis. The most severe prognosis was in the CFH mutation group. There is a high risk of recurrence of the disease after renal transplantation in patients with mutations in CFH, CFI, CFB and C3. Plasma therapy may allow complete haematological remission but frequently with persistent renal damage. Some patients are plasma resistant and some are plasma dependent. The recent progress in the determination of the susceptibility factors for aHUS, have allowed to propose new diagnostic tests including a molecular genetic testing and may permit to consider some new specific treatments in this disease (human plasma-derived CFH or complement inhibitors).
More Related Videos
Related Concept Videos
 01:27
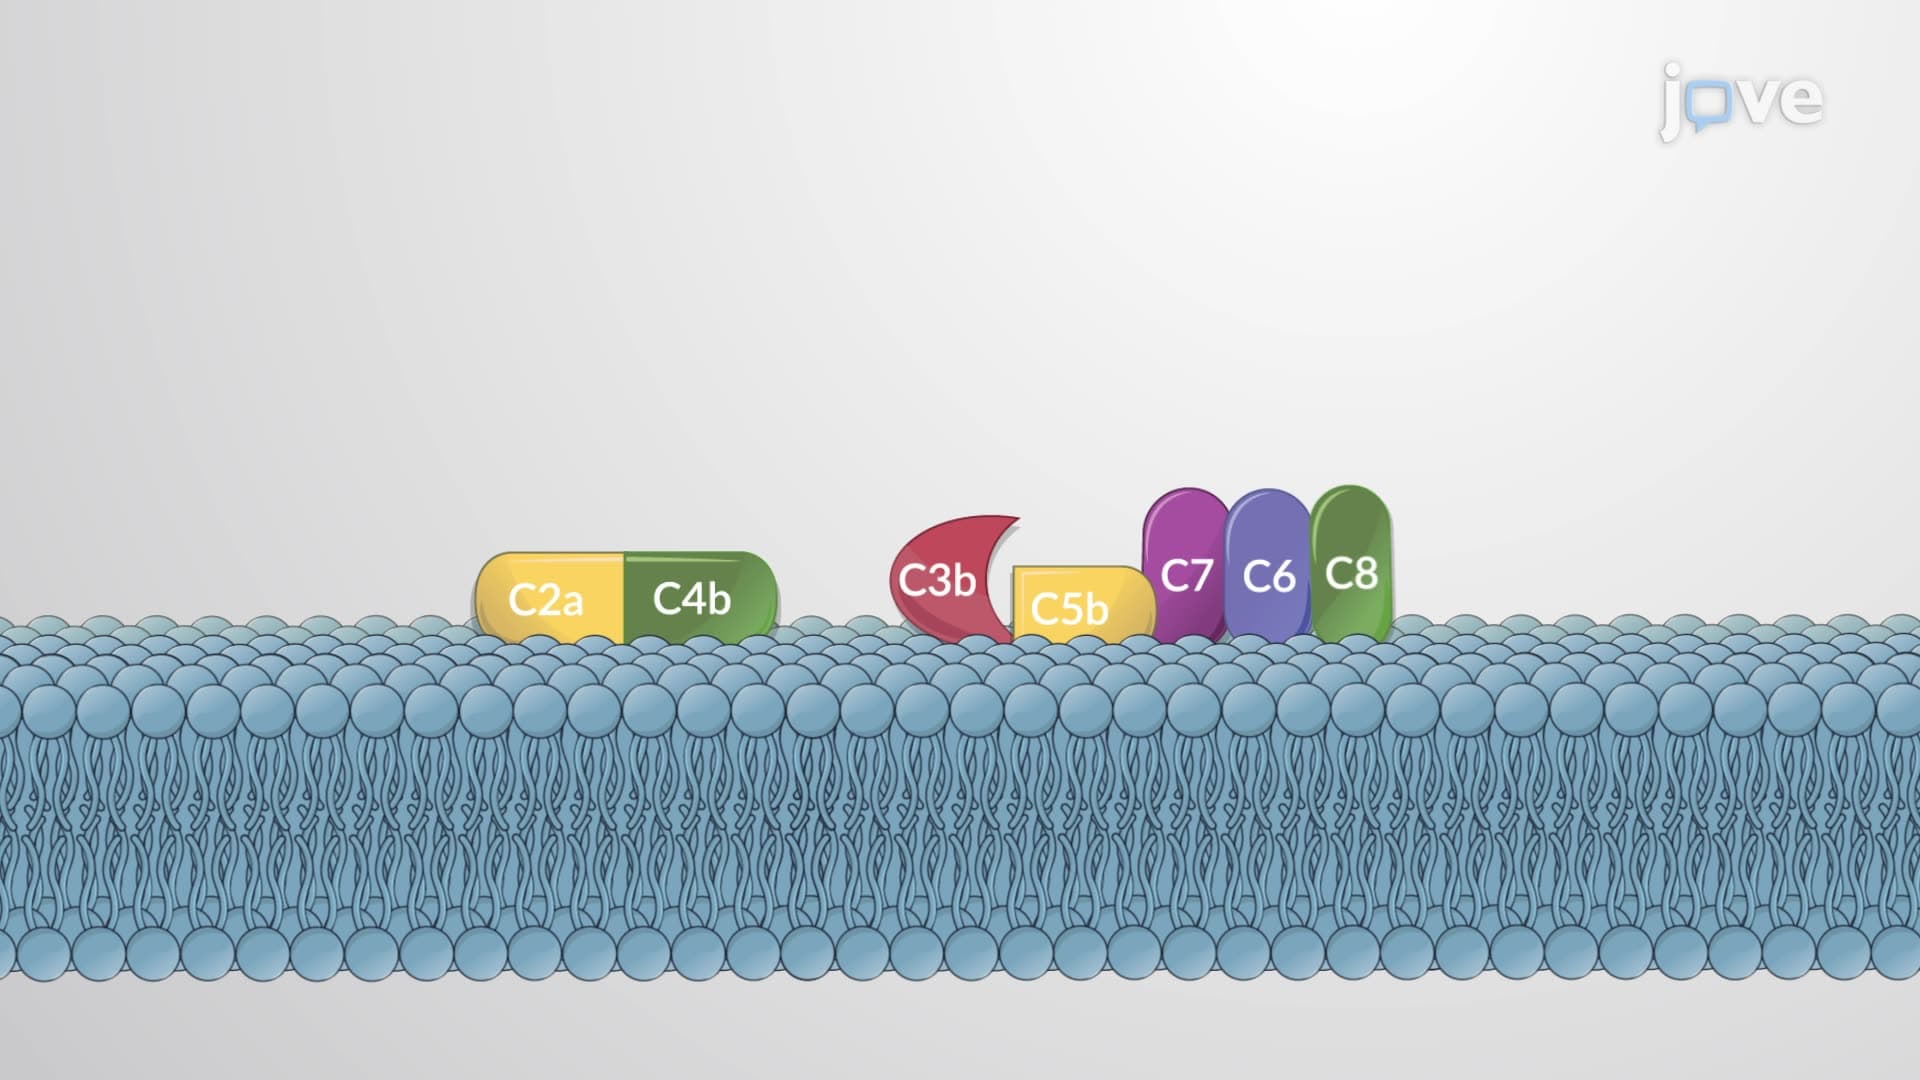
Complement System
 01:19
Hypersensitivity Reactions: Immune-Complex Reactions
 01:01
Hypersensitivity Reactions: Cytolytic Reactions
 01:24
Nephrotic Syndrome I : Introduction
 01:36
Humoral Immune Responses
 02:45
Blood Transfusion and Agglutination
History
The history of blood transfusion dates back to the 17th century, when early attempts were made in animals. In 1818 James Blundell, a British doctor, performed the first successful human blood transfusion. Later in 1900, Karl...