Related Experiment Video
Updated: Jun 3, 2026
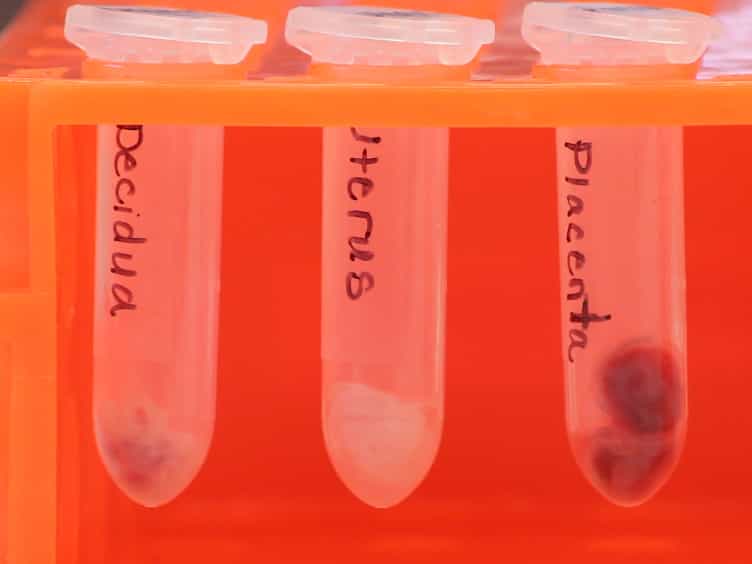

Isolation of Leukocytes from the Murine Tissues at the Maternal-Fetal Interface
Published on: May 21, 2015
HLA-G and pregnancy adverse outcomes
Monia Cecati1, Stefano R Giannubilo, Monica Emanuelli
1Dipartimento di Biochimica, Biologia e Genetica, Università Politecnica delle Marche, via Ranieri 65, Ancona 60131, Italy. moniacecati@interfree.it

There is growing evidence that pregnancy complications such as preeclampsia, recurrent pregnancy loss (RPL), IUGR, and premature birth could be associated with abnormal immunologic interactions at the fetal-maternal interface. The restricted expression of HLA-G to the subpopulation of trophoblast cells which invade the uterus has generated much interest. The alternative splicing of HLA-G primary transcript, gives origin to seven isoforms, including both membrane-bound forms (HLA-G1, G2, G3, G4) and soluble forms (sHLA-G: sHLA-G5, G6, G7). sHLA-G consists predominantly of sHLA-G1 after its shedding by metalloproteinases, and secreted sHLA-G5 representing the quantitatively dominating and full-length isoforms. HLA-G expression and HLA-G genetic variations in both the mother and the embryo/fetus may be important for pregnancy outcome. It is also intuitively apparent that a gene with putative immunosuppressive and immunotolerant potential might be functional in both the mother and the embryo/fetus/placenta. Reduced or aberrant HLA-G expression seems to be associated with certain complications of pregnancy, among which preeclampsia and possibly the risk of miscarriage, and that this may be further linked to HLA-G polymorphisms. Most of the studies aimed at assessing the role of HLA-G in pregnant diseases have considered only the maternal genotype and ignored the contribution of the fetus. In this regard, the mother, placenta and the fetus form a synthesis. Therefore, studies on placental diseases should address HLA-G expression and genetic variations also to the fetus/placenta.
There is growing evidence that pregnancy complications such as preeclampsia, recurrent pregnancy loss (RPL), IUGR, and premature birth could be associated with abnormal immunologic interactions at the fetal-maternal interface. The restricted expression of HLA-G to the subpopulation of trophoblast cells which invade the uterus has generated much interest. The alternative splicing of HLA-G primary transcript, gives origin to seven isoforms, including both membrane-bound forms (HLA-G1, G2, G3, G4) and soluble forms (sHLA-G: sHLA-G5, G6, G7). sHLA-G consists predominantly of sHLA-G1 after its shedding by metalloproteinases, and secreted sHLA-G5 representing the quantitatively dominating and full-length isoforms. HLA-G expression and HLA-G genetic variations in both the mother and the embryo/fetus may be important for pregnancy outcome. It is also intuitively apparent that a gene with putative immunosuppressive and immunotolerant potential might be functional in both the mother and the embryo/fetus/placenta. Reduced or aberrant HLA-G expression seems to be associated with certain complications of pregnancy, among which preeclampsia and possibly the risk of miscarriage, and that this may be further linked to HLA-G polymorphisms. Most of the studies aimed at assessing the role of HLA-G in pregnant diseases have considered only the maternal genotype and ignored the contribution of the fetus. In this regard, the mother, placenta and the fetus form a synthesis. Therefore, studies on placental diseases should address HLA-G expression and genetic variations also to the fetus/placenta.
Related Concept Videos
 01:19
Rh Blood Group
 01:07
Teratogenicity
 01:22
Development of Immunocompetence
The initial cells that migrate from the fetal thymus settle within the skin and epithelial tissues lining the mouth, digestive tract, and in females, the uterus and vagina. These cells, including skin-based dendritic cells, serve as antigen-presenting cells, playing a key role in T cell activation.
Subsequent T...
 01:15
Transcytosis of IgG
IgG molecules from a mother undergo transcytosis starting around 13 weeks of gestation. The amount of IgG transferred and entering the fetal blood circulation increases with...