Related Experiment Video
Updated: Jun 3, 2026
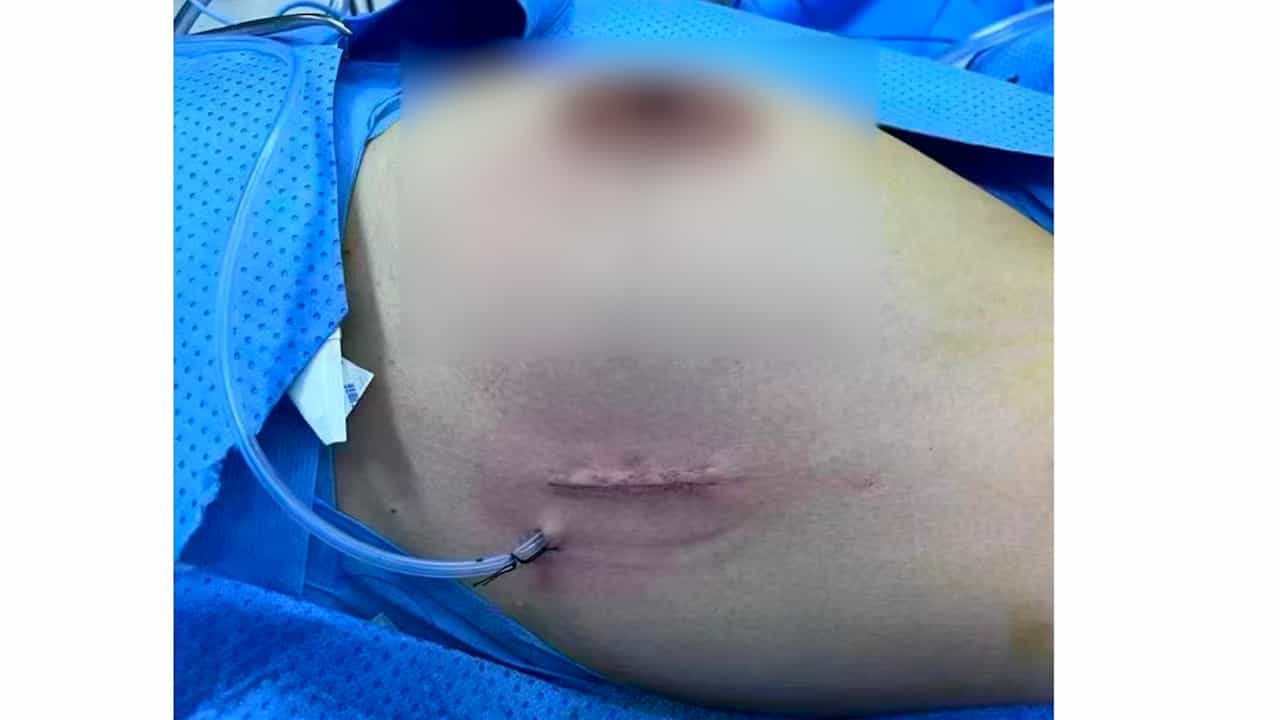

Single-port Non-liposuction Endoscopic Axillary Lymph Node Dissection in Breast Cancer Surgery
Published on: April 3, 2026
Premenopausal hormone-responsive breast cancer with extensive axillary nodes involvement: total estrogen blockade and
Francesco Recchia1, Giampiero Candeloro, Stefano Necozione
1Civilian Hospital, Oncology Department, Avezzano, Italy. frecchia1946@libero.it

Background:
Poor prognosis is associated with estrogen- and/or progesterone receptor-positive (ER(+), PGR(+)) premenopausal breast cancer (PM-BC) with high Ki-67 labeling index and extensive axillary lymph node involvement. The role of adjuvant chemotherapy (CT) and hormonal therapy have not yet been established in these patients.
Patients And Methods:
Twenty-five PM-BC patients received, in sequence, leuprorelin, taxane-anthracycline induction chemotherapy, radiation therapy, a platinum-based intensification high-dose CT, followed by leuprorelin and anastrazole for five years. Vascular endothelial growth factor (VEGF) levels were measured as the primary end-point; secondary end-points were 10-year relapse-free survival (RFS) and overall survival (OS) rates.
Results:
The median patient age was 44 years, and the mean number of positive axillary nodes was 14. All patients were ER(+) and/or PGR(+), with a median Ki-67 index of 33%. Five patients were Cerb-B2 positive. Grade 4 hematologic toxicity was observed in all patients, no patient showed a decrease of cardiac ejection fraction and hot flashes and arthralgias were of moderate intensity. After a median follow-up of 70 months, VEGF levels significantly decreased (p<0.001); 10-year RFS and OS were 76% and 78%, respectively.
Conclusion:
Total estrogen blockade and high-dose CT in PM-BC patients is feasible, has moderate toxicity, significantly reduces VEGF levels, and seems to improve the expected RFS and OS.
Related Concept Videos
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:28
Chemotherapy-Induced Nausea and Vomiting: Neurokinin-1 Receptor Antagonists