Related Experiment Video
Updated: Jun 3, 2026
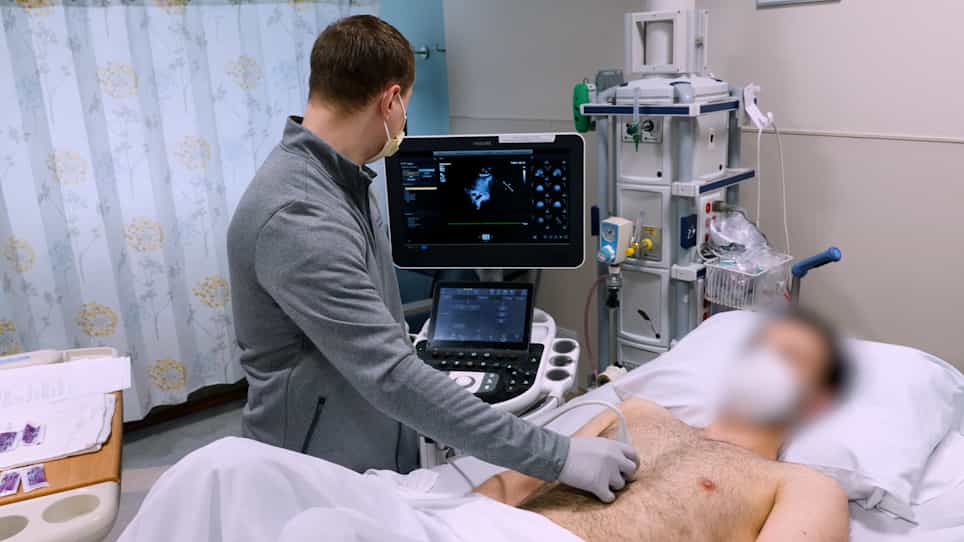

Image Acquisition Method for the Sonographic Assessment of the Inferior Vena Cava
Published on: January 13, 2023
Vascular pedicle width in acute lung injury: correlation with intravascular pressures and ability to discriminate
Todd W Rice1, Lorraine B Ware, Edward F Haponik
1Division of Allergy, Pulmonary, and Critical Care Medicine, Vanderbilt University School of Medicine, T-1218 MCN Nashville, TN 37221, USA. todd.rice@vanderbilt.edu

Introduction:
Conservative fluid management in patients with acute lung injury (ALI) increases time alive and free from mechanical ventilation. Vascular pedicle width (VPW) is a non-invasive measurement of intravascular volume status. The VPW was studied in ALI patients to determine the correlation between VPW and intravascular pressure measurements and whether VPW could predict fluid status.
Methods:
This retrospective cohort study involved 152 patients with ALI enrolled in the Fluid and Catheter Treatment Trial (FACTT) from five NHLBI ARDS (Acute Respiratory Distress Syndrome) Network sites. VPW and central venous pressure (CVP) or pulmonary artery occlusion pressure (PAOP) from the first four study days were correlated. The relationships between VPW, positive end-expiratory pressure (PEEP), cumulative fluid balance, and PAOP were also evaluated. Receiver operator characteristic (ROC) curves were used to determine the ability of VPW to detect PAOP < 8 mmHg and PAOP ≥ 18 mm Hg.
Results:
A total of 71 and 152 patients provided 118 and 276 paired VPW/PAOP and VPW/CVP measurements, respectively. VPW correlated with PAOP (r = 0.41; P < 0.001) and less well with CVP (r = 0.21; P = 0.001). In linear regression, VPW correlated with PAOP 1.5-fold better than cumulative fluid balance and 2.5-fold better than PEEP. VPW discriminated achievement of PAOP < 8 mm Hg (AUC = 0.73; P = 0.04) with VPW ≤67 mm demonstrating 71% sensitivity (95% CI 30 to 95%) and 68% specificity (95% CI 59 to 75%). For discriminating a hydrostatic component of the edema (that is, PAOP ≥ 18 mm Hg), VPW ≥ 72 mm demonstrated 61.4% sensitivity (95% CI 47 to 74%) and 61% specificity (49 to 71%) (area under the curve (AUC) 0.69; P = 0.001).
Conclusions:
VPW correlates with PAOP better than CVP in patients with ALI. Due to its only moderate sensitivity and specificity, the ability of VPW to discriminate fluid status in patients with acute lung injury is limited and should only be considered when intravascular pressures are unavailable.
More Related Videos
 07:59
Bedside Ultrasound for Guiding Fluid Removal in Patients with Pulmonary Edema: The Reverse-FALLS Protocol
Published on: July 28, 2018
 09:28
Intravital Widefield Fluorescence Microscopy of Pulmonary Microcirculation in Experimental Acute Lung Injury Using a Vacuum-Stabilized Imaging System
Published on: April 6, 2022
