Related Experiment Videos
Variability in vitamin D assays impairs clinical assessment of vitamin D status
J K C Lai1, R M Lucas, E Banks
1National Centre for Epidemiology and Population Health, The Australian National University, Canberra, Australian Capital Territory, Australia. jeffrey.lai@anu.edu.au

Background:
Measuring serum 25(OH)D concentration is common in clinical practice despite the questionable reliability of assays.
Aims:
The aim of the present study was to examine agreement in 25(OH)D concentrations measured by different assays and laboratories, and consider related clinical implications.
Methods:
Serum samples from 813 participants in the Australian Multicentre Study of Environment and Immune Function (the Ausimmune Study) were assayed for 25(OH)D concentration. Duplicate samples from subsets of subjects were sent to different laboratories, two using DiaSorin Liaison (Laboratory A and B) and one using Liquid Chromatography-Tandem Mass Spectrometry (LC-MS/MS - selected here as the nominal gold standard). Pairwise within-assay (both within-laboratory and between-laboratories) and between-assay agreement was examined using Deming regression and Bland-Altman plots. Common 25(OH)D cut-points for classification of vitamin D deficiency were used to compare the different assays.
Results:
25(OH)D concentrations measured using Liaison were substantially lower at Laboratory A than at Laboratory B (mean bias -11.60 nmol/L, 95% limits of agreement -46.39, 23.18). Both Liaison assays returned much lower 25(OH)D concentrations than LC-MS/MS (mean bias up to -26.05 nmol/L, 95% limits of agreement of -13.21, 65.31). For Laboratory A participants, 46% (355/765) were classified as vitamin D deficient (25(OH)D <50 nmol/L) using Liaison compared with 17% (128/765) using LC-MS/MS. For Laboratory B participants, the respective figures were 36% (76/209) and 20% (41/209). Hence, between 1-in-5 and 1-in-3 participants were misclassified as 'deficient'.
Conclusion:
Bias and variability in 25(OH)D measurements sufficient to affect significantly clinical decision-making were found both between-laboratories and between-assays. The adoption of common standards to allow assay calibration is required urgently.
Related Concept Videos
 01:23
Role of Skin in Vitamin D Synthesis
The solar UV B rays (290-315 nm) are absorbed by the skin, and 7-dehydrocholesterol (provitamin D3) photolyzes it to previtamin D3, which undergoes a rapid transformation to vitamin D3(cholecalciferol).
 01:11
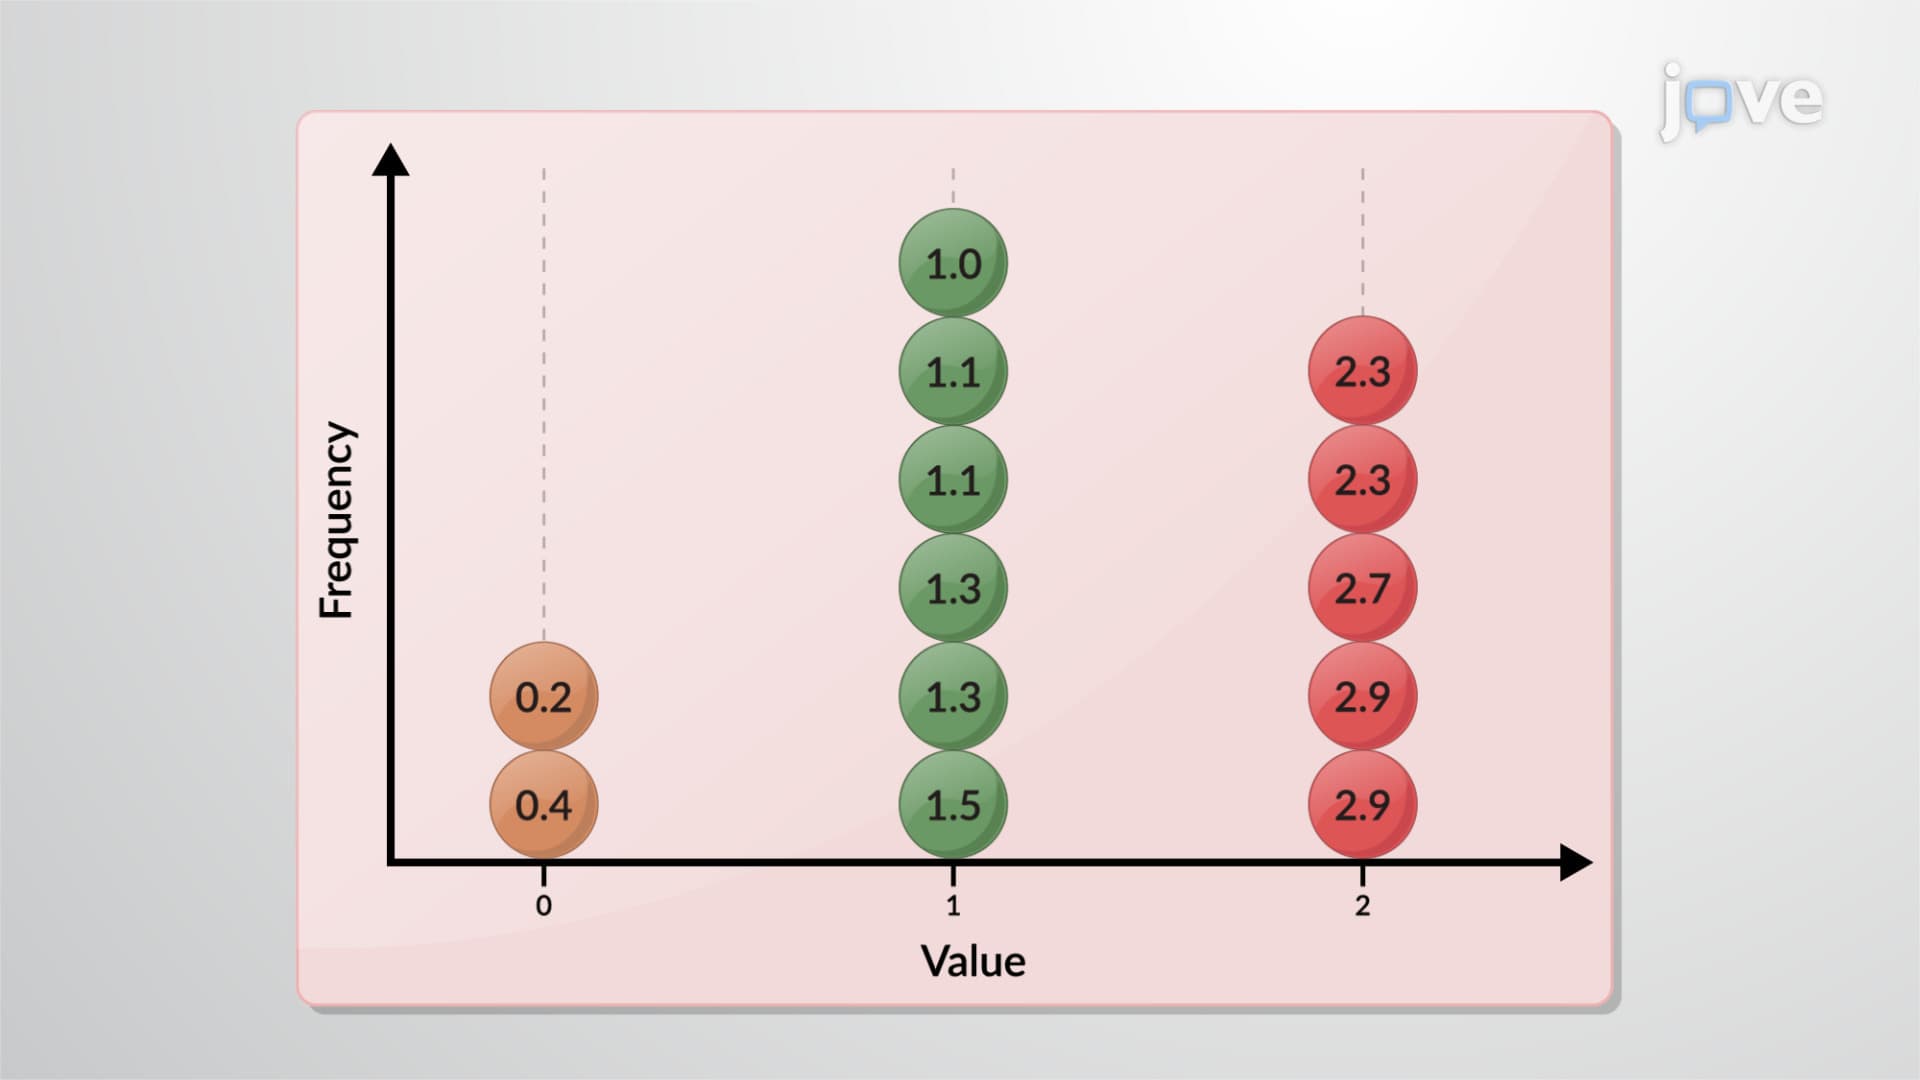
Variability: Analysis
The range is a simple measure of variability, indicating the difference between the highest and...
 01:30
Vitamins
 01:22
Effect of Hepatic Disease on Pharmacokinetics: Pathophysiologic Assessment and Liver Function Test
 01:24
Dosage Regimen: Individualization
 01:25
Role of Vitamins in Maintaining Bone Health
Vitamin A
Vitamin A is involved in the process of bone remodeling. Retinoic acid, the active metabolite of Vitamin A, has nuclear receptors in osteoblasts and osteoclasts, which are involved in bone remodeling.
Vitamin B12
Vitamin B12 acts as a cofactor during the formation of osteoblast-related proteins, such as osteocalcin. Vitamin B12 plays a role...