Related Experiment Video
Updated: Jun 3, 2026
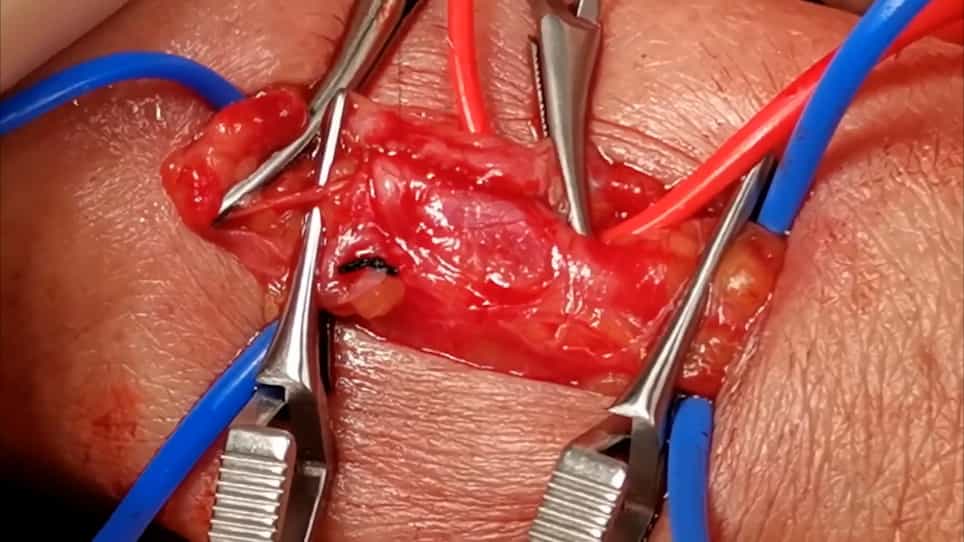
Creating Radio-cephalic Arteriovenous Fistula in the Forearm with a Modified No-Touch Technique
Published on: April 1, 2022
Barriers to timely arteriovenous fistula creation: a study of providers and patients
Pamela A Lopez-Vargas1, Jonathan C Craig, Martin P Gallagher
1Centre for Kidney Research, The Children's Hospital at Westmead, Sydney, Australia.

Insights
Most hemodialysis patients start with catheters, not preferred arteriovenous fistulas (AVFs). Formalized predialysis pathways improve AVF placement by addressing system barriers and optimizing referral timing.
Area of Science:
- Nephrology
- Vascular Surgery
- Health Services Research
Background:
- Clinical guidelines prioritize native arteriovenous fistulas (AVFs) for hemodialysis vascular access.
- However, a majority of patients in Western countries initiate hemodialysis via catheters.
- Factors contributing to delays in permanent AVF creation remain poorly understood.
Purpose of the Study:
- To identify physician and system-level barriers and enablers to arteriovenous fistula (AVF) placement.
- To investigate characteristics associated with timely AVF creation.
- To understand factors influencing the choice of vascular access at the initiation of hemodialysis therapy.
Main Methods:
- A multicenter, mixed-methods cohort study was conducted across 9 nephrology centers in Australia and New Zealand.
- Data were prospectively collected from 319 incident hemodialysis patients, including predialysis education, staff interviews, referral times, and estimated glomerular filtration rate (eGFR).
- Qualitative and quantitative analyses were employed to identify barriers and enablers to AVF placement.
Main Results:
- Only 39% of 319 incident hemodialysis patients started therapy with an AVF; 59% used a catheter.
- Key barriers included lack of formal referral policies, long wait times for surgical review, and inadequate patient databases.
- Low eGFR thresholds (median 7 mL/min/1.73 m(2)) were observed for referral and creation, with median wait times of 3.7 weeks for access placement.
- Late nephrologist assessment (<12 months before dialysis start) independently predicted catheter use (OR, 8.71; P < 0.001).
- High-performing centers featured formalized predialysis pathways, centralized databases, and lower nephrologist-to-patient ratios.
Conclusions:
- A formalized predialysis pathway, incorporating patient education and defined eGFR thresholds for AVF placement, is associated with improved rates of permanent vascular access.
- System-level factors, such as clear policies and efficient patient management, are crucial for optimizing AVF utilization.
- Further research should explore patient-specific barriers and utilize longitudinal data for a comprehensive understanding.
Background:
Current clinical practice guidelines recommend a native arteriovenous fistula (AVF) as the vascular access of first choice. Despite this, most patients in western countries start hemodialysis therapy using a catheter. Little is known regarding specific physician and system characteristics that may be responsible for delays in permanent access creation.
Study Design:
Multicenter cohort study using mixed methods; qualitative and quantitative analysis.
Setting & Participants:
9 nephrology centers in Australia and New Zealand, including 319 adult incident hemodialysis patients.
Predictor:
Identification of barriers and enablers to AVF placement.
Outcomes:
Type of vascular access used at the start of hemodialysis therapy.
Measurements:
Prospective data collection included data concerning predialysis education, interviews of center staff, referral times, and estimated glomerular filtration rate (eGFR) at AVF creation and dialysis therapy start.
Results:
319 patients started hemodialysis therapy during the 6-month period, 39% with an AVF and 59% with a catheter. Perceived barriers to access creation included lack of formal policies for patient referral, long wait times for surgical review and access placement, and lack of a patient database for management purposes. eGFR thresholds at referral for and creation of vascular accesses were considerably lower than appreciated (in both cases, median eGFR of 7 mL/min/1.73 m(2)), with median wait times for access creation of only 3.7 weeks. First assessment by a nephrologist less than 12 months before dialysis therapy start was an independent predictor of catheter use (OR, 8.71; P < 0.001). Characteristics of the best performing centers included the presence of a formalized predialysis pathway with a centralized patient database and low nephrologist and surgeon to patient ratios.
Limitations:
A limited number of patient-based barriers was assessed. Cross-sectional data only.
Conclusions:
A formalized predialysis pathway including patient education and eGFR thresholds for access placement is associated with improved permanent vascular access placement.


