Related Experiment Video
Updated: Jun 3, 2026
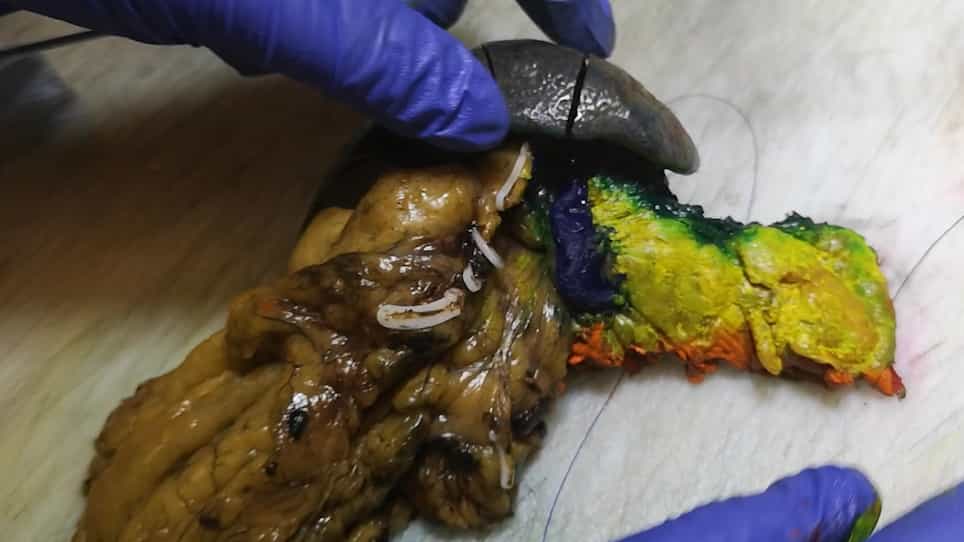

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
Implication of the examining pathologist to meet the oncologic standard of lymph node count after laparoscopic
Malgorzata Lanowska1, Jekaterina Vasiljeva, Vito Chiantera
1Department of Gynecology, Charité Universitätsmedizin, Berlin, Germany.

Objective:
The lymph node number as benchmark in oncologic operations depends on the patient's anatomy, surgeon's skill and pathologist's accuracy. The influence of the pathologist is barely evaluated.
Methods:
A retrospective analysis of lymph node numbers after 700 laparoscopic lymphadenectomies in correlation to the examining pathologists was done. Three surgeons from the same department performed all operations at 2 campi, where 2 separate pathology institutions exist. Lymph node specimens were assigned randomly to any of the 62 involved pathologists.
Results:
The mean number of lymph nodes was equal for all surgeons. Lymph node specimens were analyzed in the pathology institute of campus I and II in 416 and 284 cases, respectively. The mean number of lymph nodes following pelvic and para-aortic lymphadenectomy was 36 at campus II and 30 at campus I (p < 0.0001). There was also a significant difference for pelvic (19.9 vs. 17.7; p < 0.0001) and para-aortic lymph node counts (16.2 vs. 14.1; p < 0.01) between both pathology institutes. At campus II, 22.6% of lymph node counts did not meet the oncologic standard for pelvic and 16.7% did not meet the standard for para-aortic lymph nodes. Moreover, at campus I, 35.5 and 20.8% of pathologists described less than the oncologic limit of pelvic and para-aortic lymph nodes, respectively.
Conclusion:
The number of removed lymph nodes is not an absolute parameter for surgical radicality. Interdisciplinary cooperation with pathologists is mandatory to meet oncologic standards.

