Related Experiment Video
Updated: Jun 3, 2026
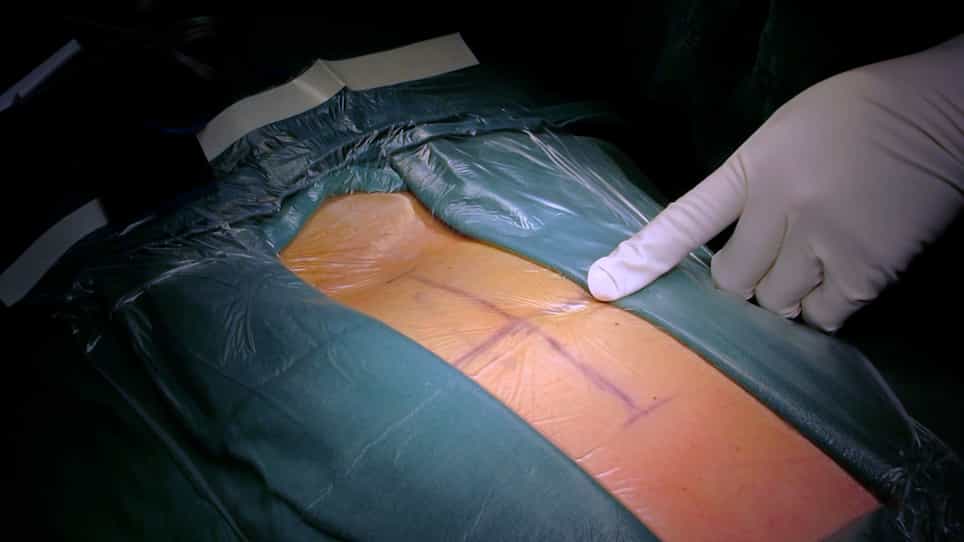

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
[The impact of thoracic and thoracolumbar angular kyphosis on pelvic shape and sagittal alignment]
Wei-Shi Li1, Zhong-Qiang Chen, Zhao-Qing Guo
1Department of Orthopaedics, Peking University Third Hospital, Beijing, China.

Objective:
To analyze the impact of thoracic and thoracolumbar angular kyphosis on pelvic shape and sagittal alignment.
Methods:
From May 2002 to June 2010, the sagittal spino-pelvic parameters were analyzed in lateral standing radiographs of 32 patients (mean age 29.6 years) with thoracolumbar angular kyphosis. The parameters included Cobb angle of kyphosis, lumbar lordosis (LL), pelvic incidence (PI), sacrum slope (SS), pelvic tilt (PT) and sagittal vertical axis (SVA). All pelvic parameters in the patients were compared with those reported in historical normal subjects. All patients were treated by using kyphotic correction and fusion. The preoperative and postoperative parameters were compared. The pelvic parameters were also compared between the patients with kyphotic apex located at T(1-8) and those located at T(9-12) and thoracolumbar junction. The linear regression analysis was used to investigate the independent factors of PI.
Results:
The mean kyphosis was 90.1° (31° - 138°). The mean age of kyphosis occurrence was 6.1 years. The mean PI, SS and PT were 34.8°, 35.8° and -0.7° respectively. The PI and PT were significantly smaller (P < 0.001) in the patients than those in normal subjects while the SS was similar. The kyphosis was improved to 27.9° post-operatively. There was no difference in PI values between pre-operation and postoperation (P > 0.05). The PI and SS in patients whose kyphosis located at thoracic spine (T(1-8)) were significantly higher than those at T(9)-L(2). Instead of patients' age and LL, the preoperative Cobb angle of kyphosis and the levels where kyphosis located were two independent impact factors of PI.
Conclusions:
The kyphosis occurred at childhood may influence pelvic shape and alignment significantly. The lower kyphotic apex located and the bigger kyphosis, the greater impact on the pelvic morphology. The surgery can improve the kyphosis, but can not change the sagittal pelvic morphology. Early treatment of thoracolumbar angular kyphosis is beneficial not only to reconstruction of spine alignment but also to the formation of sagittal pelvic morphology.
More Related Videos
 07:44
Evaluation of Patients' Posture and Gait Profile After Lumbar Fusion Surgery by Video Rasterstereography and Treadmill Gait Analysis
Published on: March 23, 2019
 04:19
Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Related Concept Videos
 01:16
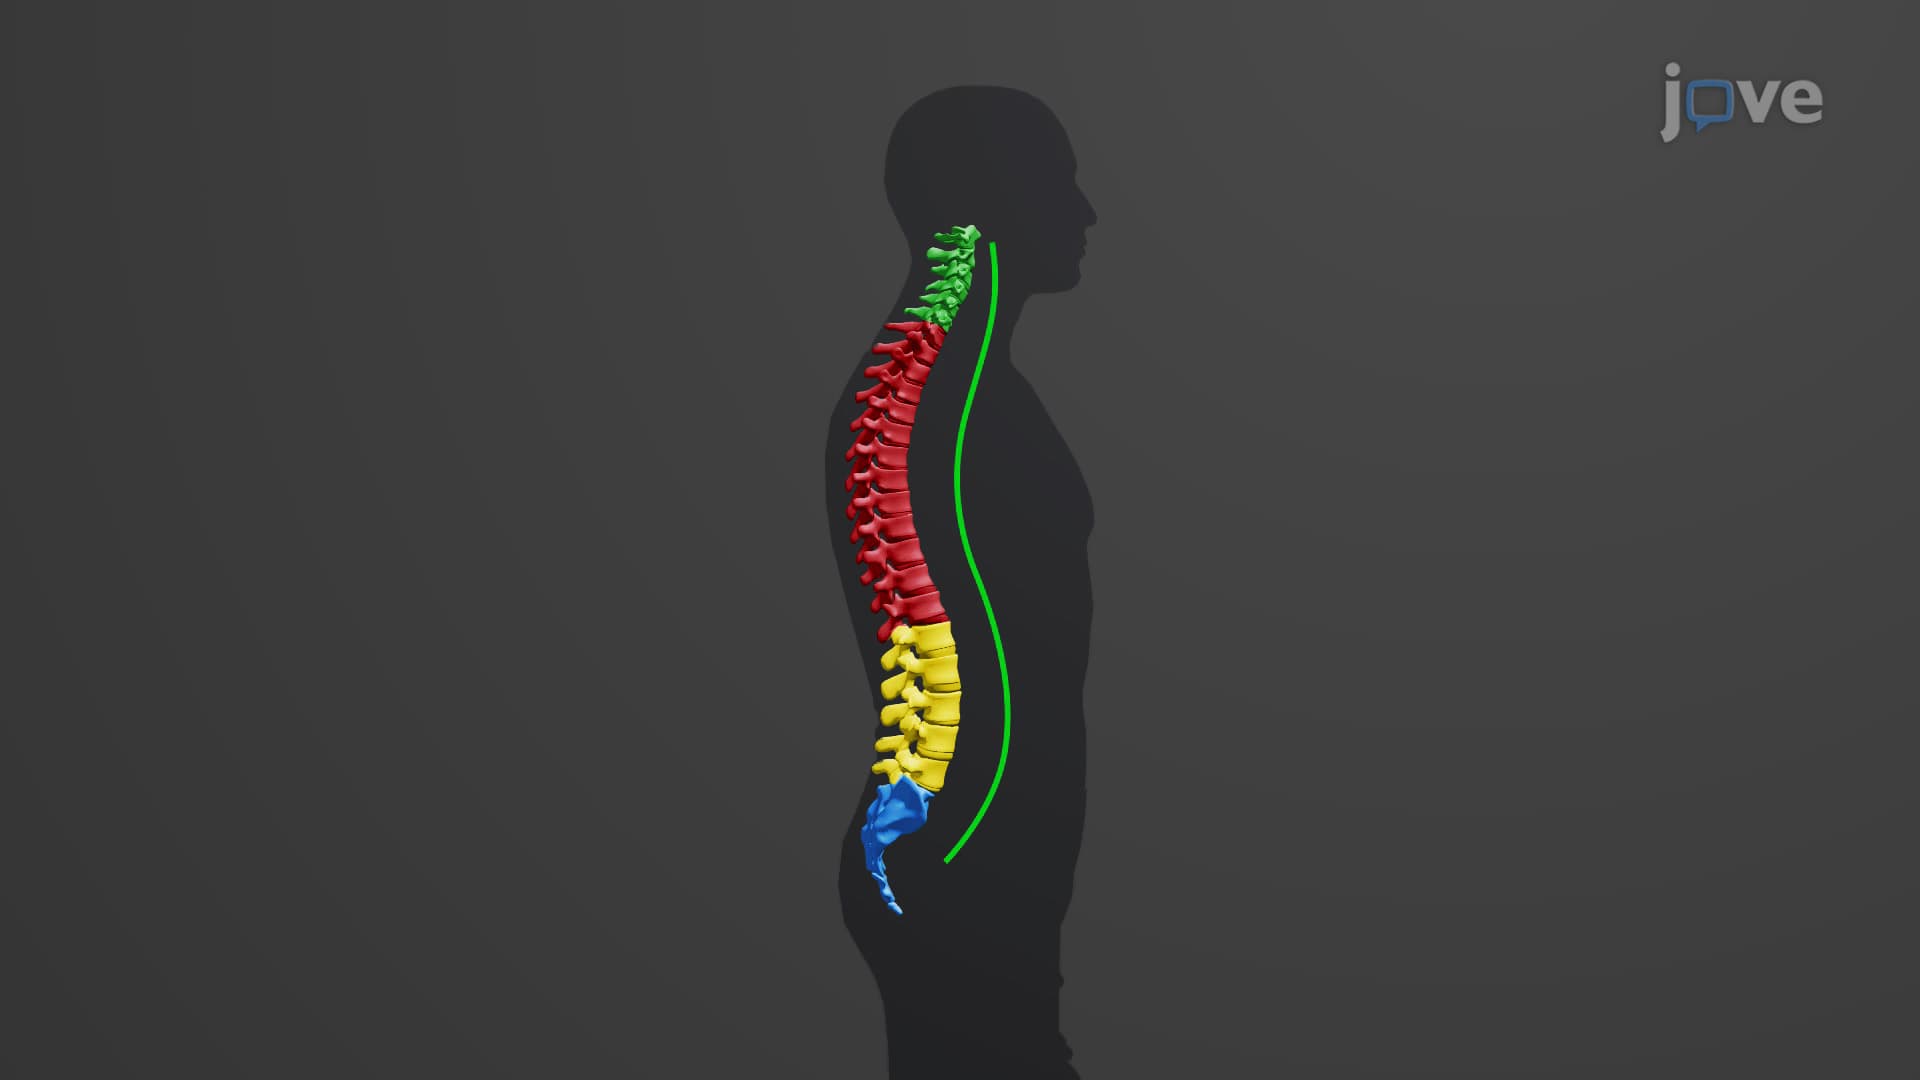
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:09
Changes in the Appendicular Skeleton with Age
Initially, the limb buds consist of a core of mesenchyme covered by a layer of ectoderm. The ectoderm at the end of the limb bud thickens to form a narrow crest called the apical ectodermal ridge. This ridge stimulates the underlying...