Related Experiment Video
Updated: Jun 3, 2026

Sodium Taurocholate Induced Severe Acute Pancreatitis in C57BL/6 Mice
Published on: June 28, 2021
[Clinical characteristics of children with acute pancreatitis]
Yi-Min Zhu1, Fang Liu, Xiao-Yu Zhou
1Department of Maternal and Child Health Care, School of Public Health, Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430030, China.

Insights
Acute pancreatitis in children often presents with gastrointestinal symptoms and can involve other organs. Early diagnosis requires monitoring serum amylase and imaging, especially in cases of unexplained abdominal pain and vomiting.
Area of Science:
- Pediatric Gastroenterology
- Pancreatology
- Clinical Pediatrics
Context:
- Acute pancreatitis in children is a serious condition requiring prompt diagnosis and management.
- Understanding the specific clinical and biochemical characteristics of pediatric acute pancreatitis is crucial for effective treatment.
Purpose:
- To analyze the clinical characteristics, diagnostic markers, and treatment outcomes of acute pancreatitis in children.
- To establish a basis for early diagnosis and treatment strategies for pediatric acute pancreatitis.
Summary:
- A retrospective study of 121 children with acute pancreatitis revealed that gastrointestinal symptoms like abdominal pain and vomiting are primary indicators.
- Elevated serum amylase levels (94.2%) within 24 hours of admission and imaging findings like pancreatic edema were common.
- Extrapancreatic organ damage, particularly to the liver and intestines, occurred in 62.0% of cases, complicating the condition.
Impact:
- Highlights the importance of considering acute pancreatitis in children with unexplained abdominal pain and vomiting, especially younger children who may not report pain.
- Emphasizes serial monitoring of serum amylase and imaging studies for timely diagnosis and management.
- Provides insights into the high incidence of extrapancreatic damage, guiding comprehensive patient care.
Objective:
To analyze the characteristics of children with acute pancreatitis and provide the basis of early diagnosis and treatment.
Methods:
Totally 121 children with acute pancreatitis admitted to Hunan Children's Hospital between March 2003 and December 2009 were enrolled in this retrospective study. The data of clinical manifestations, biochemical examinations, imaging and prognosis were summarized and statistically analyzed.
Results:
Of the 121 cases, preschool and school-age children were the main groups, and the prevalent months were May and June. Abdominal pain (88.4%) and vomiting (61.2%) were the major initial symptoms of pancreatitis in children, but none of children under the age 1 year complained of abdominal pain; 70.2% had signs of abdominal tenderness, accompanied by abdominal rigidity, distension, hepatomegaly, jaundice, etc. Severe patients developed shock, convulsions, coma and so on. Serum amylase concentration increased to above the upper reference limit in 114 children (94.2%) when they admitted within 24 hours after admission. Urine amylase elevation was noted in 77 children (79.4%). The amylase concentration decreased after 3 days, but not all returned to normal 14 days afterward. Children with sustained serum amylase elevation or serum amylase level ≥ 3 times upper limit of normal range more likely to have fever, vomiting, abdominal distension, and pancreatic abnormalities at ultrasonography or CT which showed that the echo of pancreas decreased or enhanced, pancreas edema, pancreatic duct expanded, etc. Abdominal ultrasonography and CT showed that 75 cases (62.0%) had other organ damage besides pancreatitis, liver (25.3%) and intestinal (16.0%) damages were very common, while liver and myocardial damages were seen frequently in the laboratory examinations, which complicated with serum ALT/AST, total bilirubin, blood glucose elevation and myocardial enzyme abnormalities. Several gastroscopic examinations showed mucosal hyperemia and edema, sheet-like erosion, etc. Except for one case who underwent laparotomy, all the remaining children were treated with non-operative comprehensive treatment. Of them 119 were cured or improved, 2 died and 5 had recurred disease later.
Conclusions:
Gastrointestinal symptoms were the main clinical manifestations of acute pancreatitis in children, often complicated with extrapancreatic damage. The younger the patient was, the less complaint of abdominal pain they had. This indicates that acute pancreatitis should be considered when children suffered from acute abdominal pain and vomiting which had no known cause or could not be explained. It is important to do take serial monitoring of serum amylase, and imaging procedures.


Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
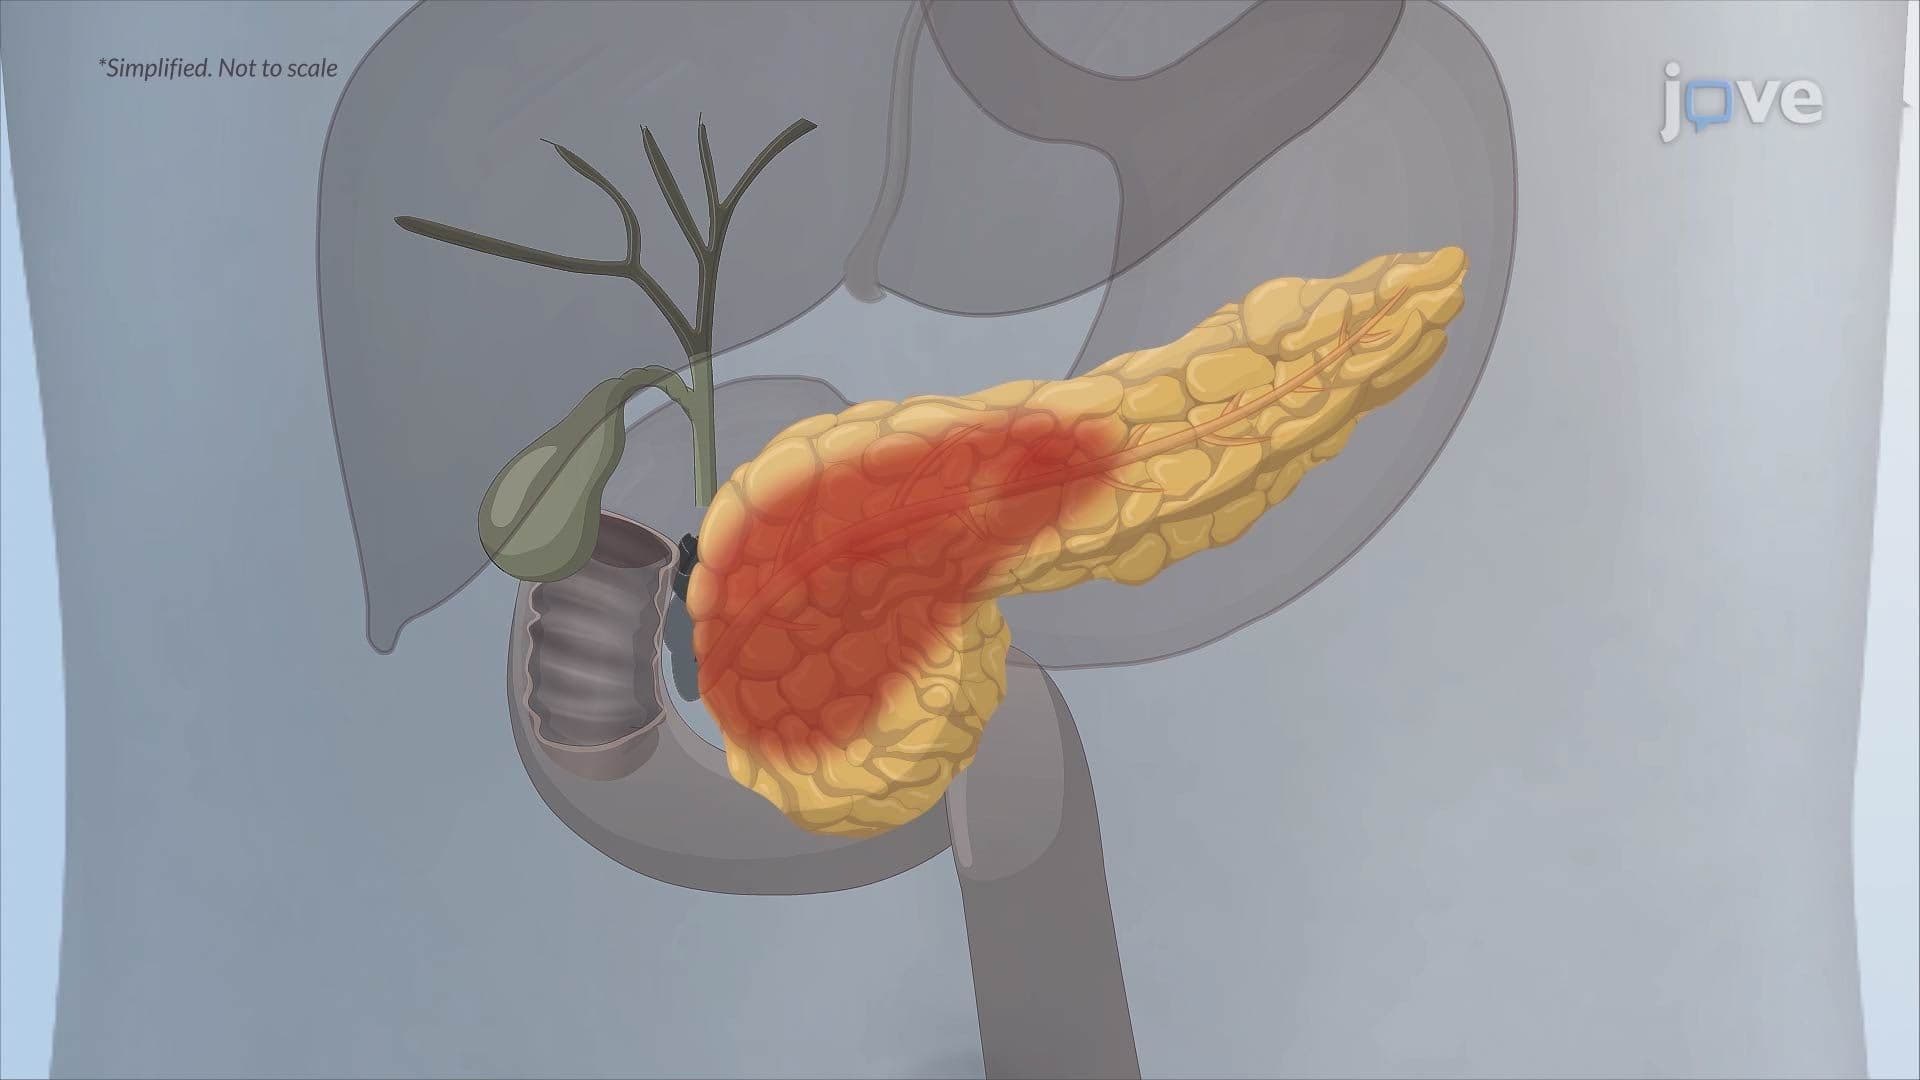
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:25
Chronic Pancreatitis I: Introduction
 01:24
Chronic Pancreatitis I: Introduction
Pancreatitis is the inflammation of the pancreas, which occurs when the immune system becomes active and causes swelling, pain, and disruptions in organ function. Pancreatitis can manifest as either an acute or chronic condition.
Acute pancreatitis arises suddenly and lasts for a brief duration, while chronic pancreatitis is a long-term affliction...