Performance of cardiac output measurement derived from arterial pressure waveform analysis in patients requiring high-dose vasopressor therapy
Related Experiment Video
Updated: Jun 3, 2026
Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
S Metzelder1, M Coburn, M Fries
1Department of Anaesthesiology, University Hospital of the RWTH Aachen, Pauwelsstr. 30, D-52074 Aachen, Germany.

Background:
Arterial pressure waveform analysis of cardiac output (APCO) without external calibration (FloTrac/Vigileo™) is critically dependent upon computation of vascular tone that has necessitated several refinements of the underlying software algorithms. We hypothesized that changes in vascular tone induced by high-dose vasopressor therapy affect the accuracy of APCO measurements independently of the FloTrac software version.
Methods:
In this prospective observational study, we assessed the validity of uncalibrated APCO measurements compared with transpulmonary thermodilution cardiac output (TPCO) measurements in 24 patients undergoing vasopressor therapy for the treatment of cerebral vasospasm after subarachnoid haemorrhage.
Results:
Patients received vasoactive support with [mean (sd)] 0.53 (0.46) µg kg(-1) min(-1) norepinephrine resulting in mean arterial pressure of 104 (14) mm Hg and mean systemic vascular resistance of 943 (248) dyn s(-1) cm(-5). Cardiac output (CO) data pairs (158) were obtained simultaneously by APCO and TPCO measurements. TPCO ranged from 5.2 to 14.3 litre min(-1), and APCO from 4.1 to 13.7 litre min(-1). Bias and limits of agreement were 0.9 and 2.5 litre min(-1), resulting in an overall percentage error of 29.6% for 68 data pairs analysed with the second-generation FloTrac(®) software and 27.9% for 90 data pairs analysed with the third-generation software. Precision of the reference technique was 2.6%, while APCO measurements yielded a precision of 29.5% and 27.9% for the second- and the third-generation software, respectively. For both software versions, bias (TPCO-APCO) correlated inversely with systemic vascular resistance.
Conclusions:
In neurosurgical patients requiring high-dose vasopressor support, precision of uncalibrated CO measurements depended on systemic vascular resistance. Introduction of the third software algorithm did not improve the insufficient precision (>20%) for APCO measurements observed with the second software version.
Related Concept Videos
 01:17
Measurement of Blood Pressure
 01:30
Equipments Used To Measure Blood Pressure
This invasive approach involves cannulating a peripheral artery. During each cardiac contraction, pressure generates mechanical motion within the catheter, transmitted through rigid, fluid-filled tubing to a transducer. This transducer converts mechanical motion into electrical signals displayed as waveforms on a monitor. An automatic flushing system prevents blood backflow. Due to the potential risk of unexpected arterial blood loss, this method is primarily used in intensive...
 01:19
Assessing Blood pressure using a doppler ultrasound
Pre-Procedural Guidelines for Doppler Ultrasound Blood Pressure Assessment:
Preparation of Equipment:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:19
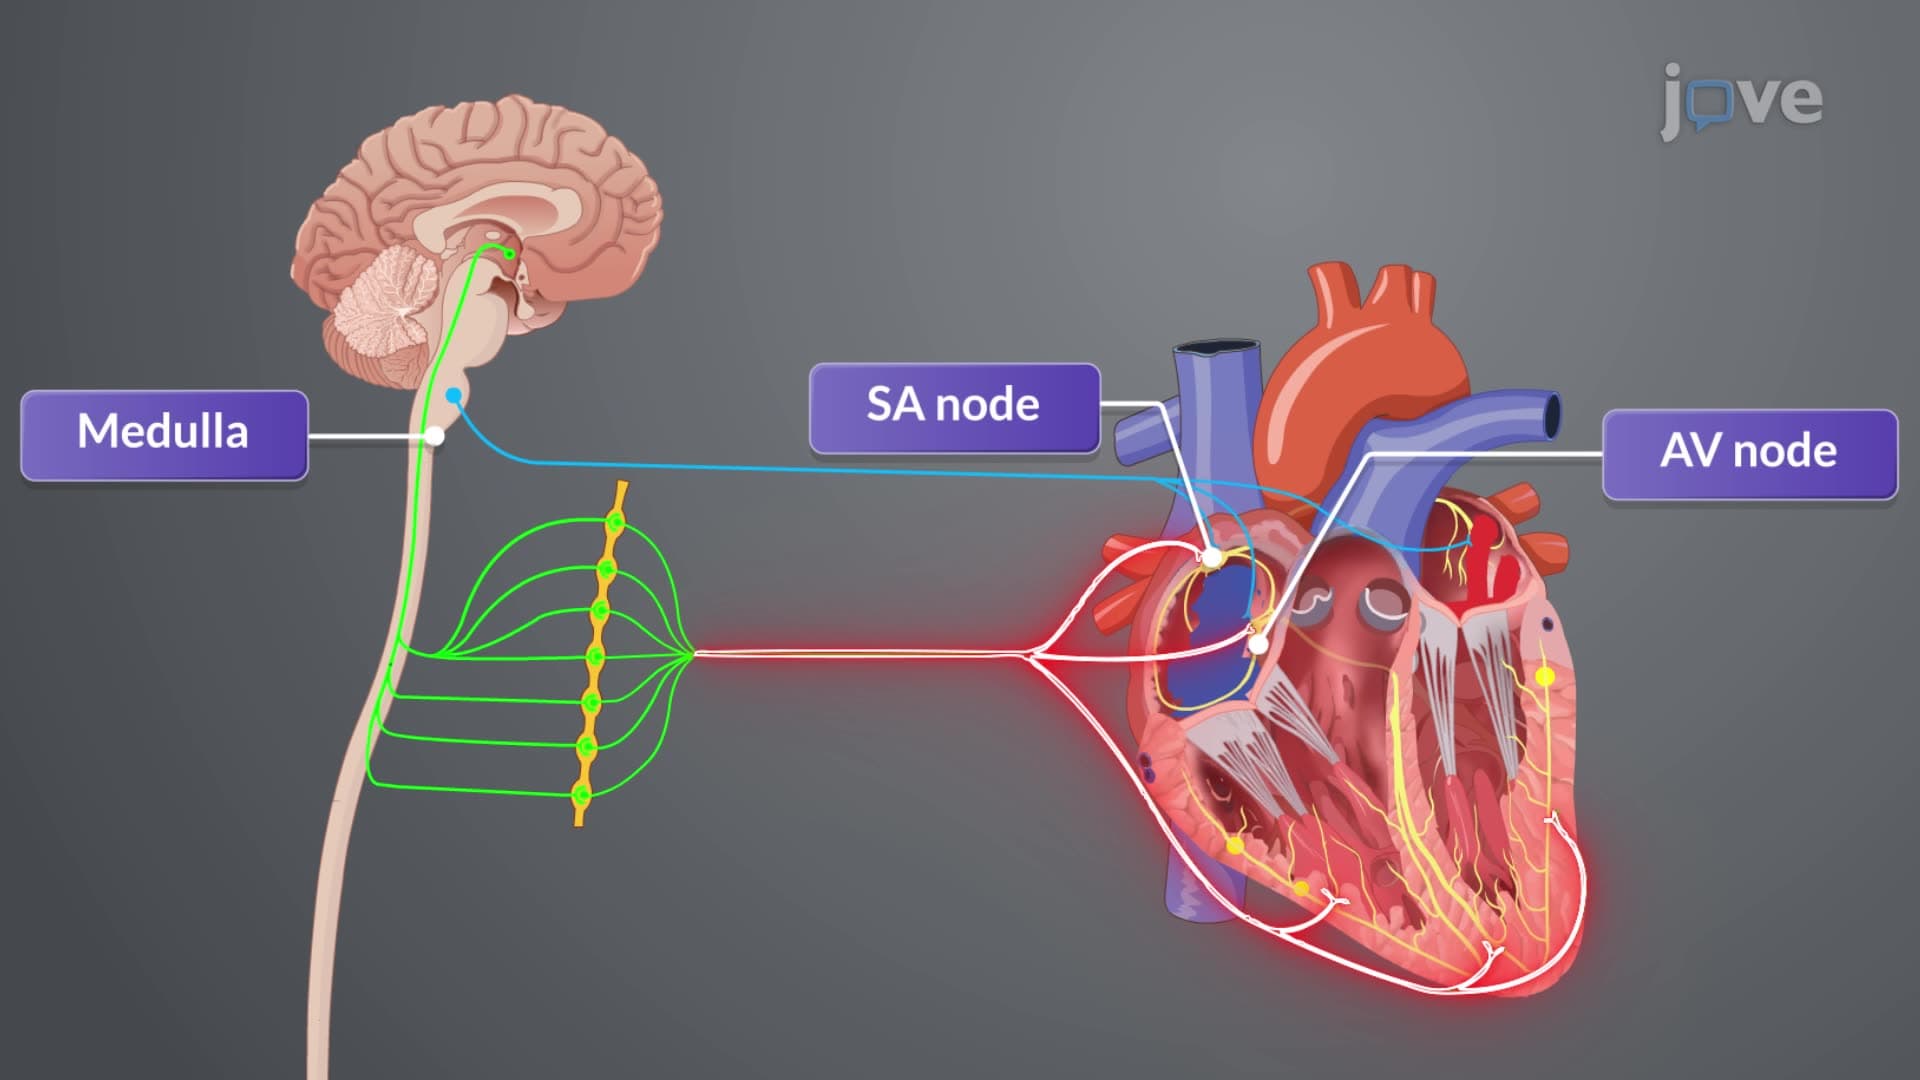
Cardiac Output I:Effect of Heart Rate on Cardiac Output
Cardiac output (CO) refers to the total amount of blood ejected by one of the ventricles in liters per minute (L/min). In a resting adult, CO ranges from 5 to 6 L/min, adjusting according to the body's metabolic requirements.
Effect of Heart Rate on Cardiac Output
Cardiac output adapts to metabolic demands during stress, physical activity, or illness. The autonomic nervous system regulates heart rate via the sinoatrial node. The parasympathetic nervous system decreases heart rate...
 01:22
Cardiac Output II: Effect of Stroke Volume on Cardiac Output
Preload
Preload refers to the initial elongation of the cardiac myocytes before contraction and is related to the volume of blood filling the heart at the end of diastole, or end-diastolic volume. The...