Related Experiment Video
Updated: Jun 3, 2026

Preoxygenation Techniques for Tracheal Intubation in Critically Ill Adults Utilizing Oxygen Mask and Noninvasive Ventilation
Published on: December 5, 2025
Impact of a specialized multidisciplinary tracheostomy team on tracheostomy care in critically ill patients
Charles de Mestral1, Sameena Iqbal, Nancy Fong
1The Department of Surgery, McGill University Health Centre, Montréal, Que., Canada.

Background:
A multidisciplinary tracheostomy team was created in 2005 to follow critically ill patients who had undergone a tracheostomy until their discharge from hospital. Composed of a surgeon, surgical resident, respiratory therapist, speech-language pathologist and clinical nurse specialist, this team has been meeting twice a week for rounds involving patients who transitioned from the intensive care unit (ICU) to the medical and surgical wards. Our objective was to assess the impact of this multidisciplinary team on downsizing and decannulation times, on the incidence of speaking valve placement and on the incidence of tracheostomy-related complications on the ward.
Methods:
This study was conducted at a tertiary care, level-1 trauma centre and teaching hospital and involved all patients who had received a tracheostomy during admission to the ICU from Jan. 1 to Dec. 31, 2004 (preservice group), and from Jan. 1 to Dec. 31, 2006 (postservice group). We compared the outcomes of patients who required tracheostomies in a 12-month period after the team was created with those of patients from a similar time frame before the establishment of the team.
Results:
There were 32 patients in the preservice group and 54 patients in the postservice group. Under the new tracheostomy service, there was a decrease in incidence of tube blockage (5.5% v. 25.0%, p = 0.016) and calls for respiratory distress (16.7% v. 37.5%, p = 0.039) on the wards. A significantly larger proportion of patients also received speaking valves (67.4% v. 19.4%, p < 0.001) after creation of the team. Furthermore, there appeared to be a decreased time to first tube downsizing (26.0 to 9.4 d) and decreased time to decannulation (50.4 to 28.4 d), although this did not reach statistical significance owing to our small sample size.
Conclusion:
Standardized care provided by a specialized multidisciplinary tracheostomy team was associated with fewer tracheostomy-related complications and an increase in the use of a speaking valve.


Related Concept Videos
 01:23
Oxygen Delivering System III: Tracheostomy and T-piece
Tracheostomy
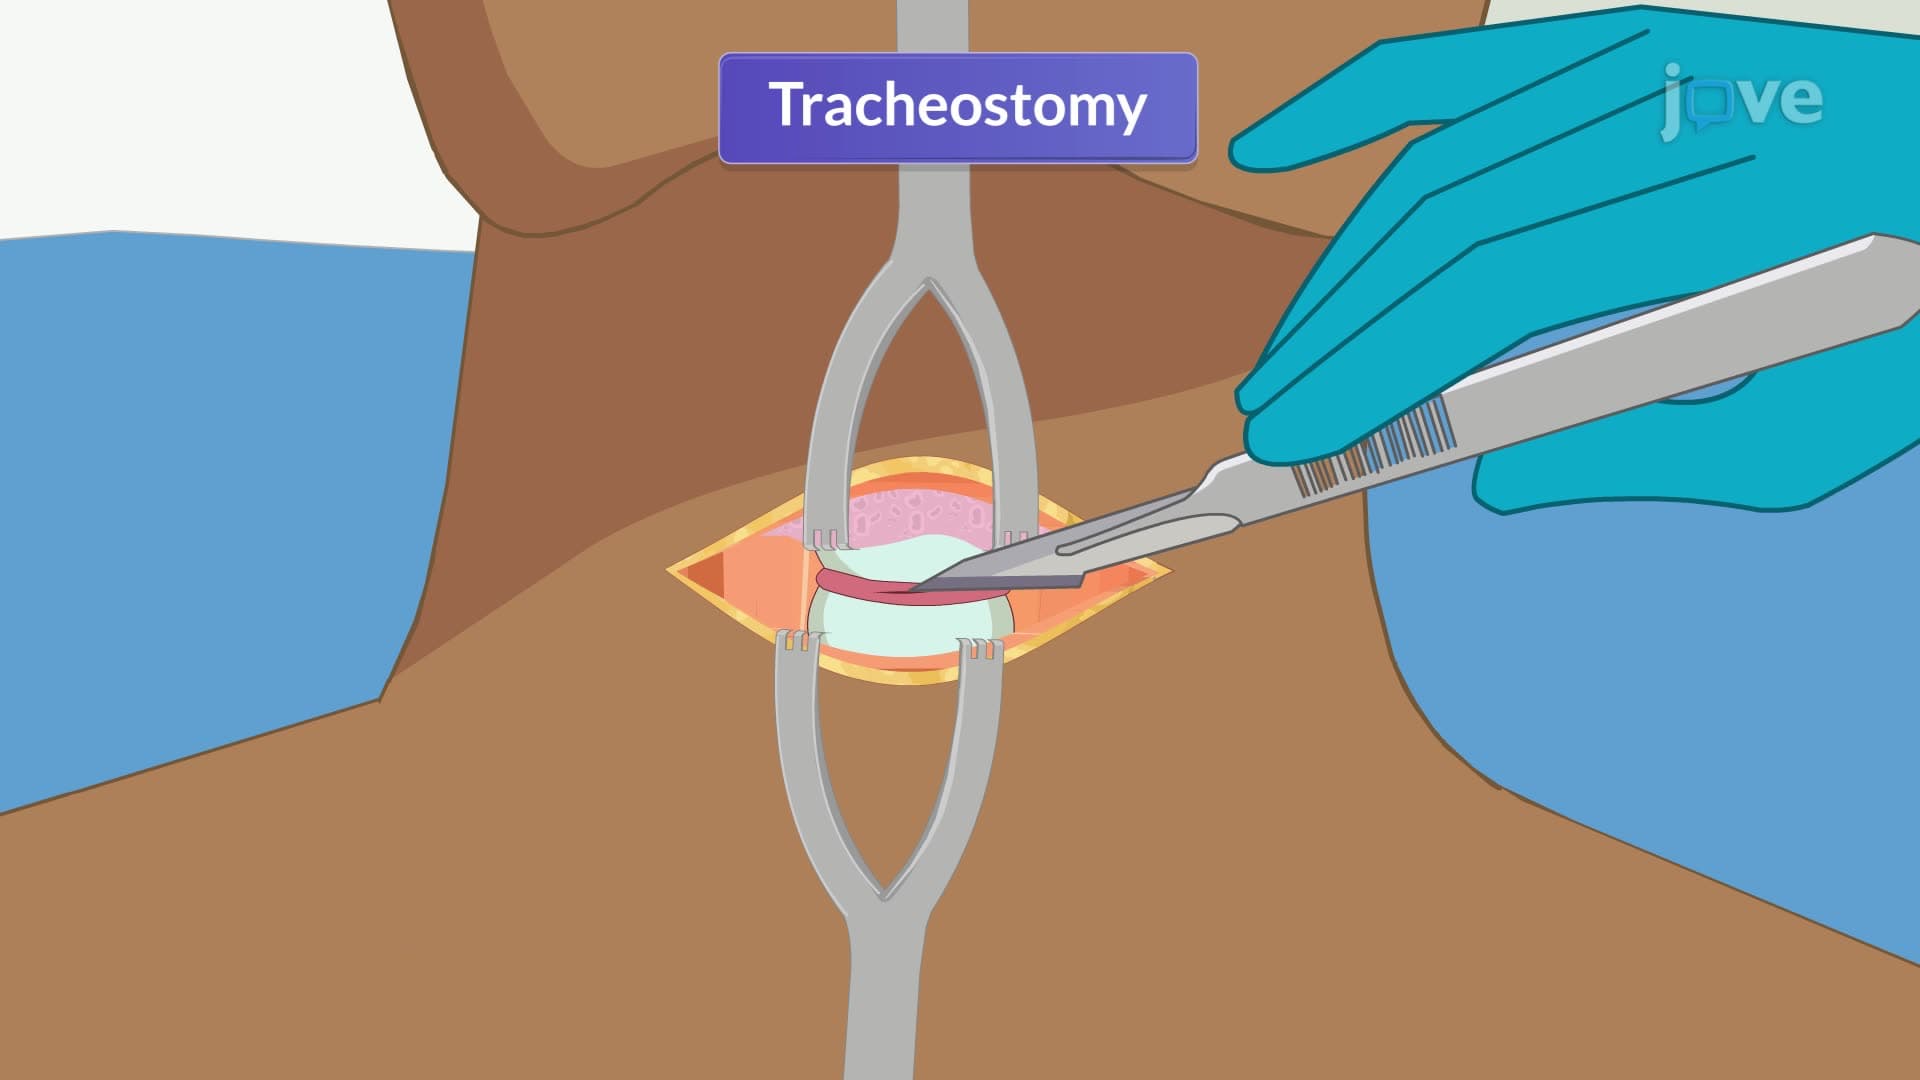
A tracheostomy is a surgically created opening (stoma) in the anterior part of the trachea. It is used to establish a patient airway, bypass an upper airway obstruction, simplify the removal of secretions, permit long-term...
 01:16
Tracheostomy Care I: Pre-procedural Steps
Required Equipment
The equipment necessary for tracheostomy care includes:
 01:28
Tracheostomy: Procedure and Tubes
Tracheostomy tubes can be made of semiflexible plastic (polyurethane or silicone), rigid plastic, or metal, and they come in...
 01:25
Tracheostomy Care II: Procedure
Step 1: Perform hand hygiene, and put on personal protective equipment: gown, gloves, mask and...
 01:16
Oxygen Delivering System II: Venturi Mask and Transtracheal Oxygen
Venturi Mask
The Venturi mask, named after the Venturi effect, is designed to deliver precise oxygen concentrations. It consists of a large tube with an oxygen inlet that narrows down, causing a pressure drop that pulls air in through adjustable side ports. The mask is a lightweight,...
 01:21
Tracheostomy Decannulation
Description of the Procedure
Decannulation refers to the permanent removal of the tracheostomy tube, signaling the resolution of the condition that initially necessitated the tracheostomy. The process requires a well-coordinated interplay between...