Related Experiment Video
Updated: Jun 3, 2026
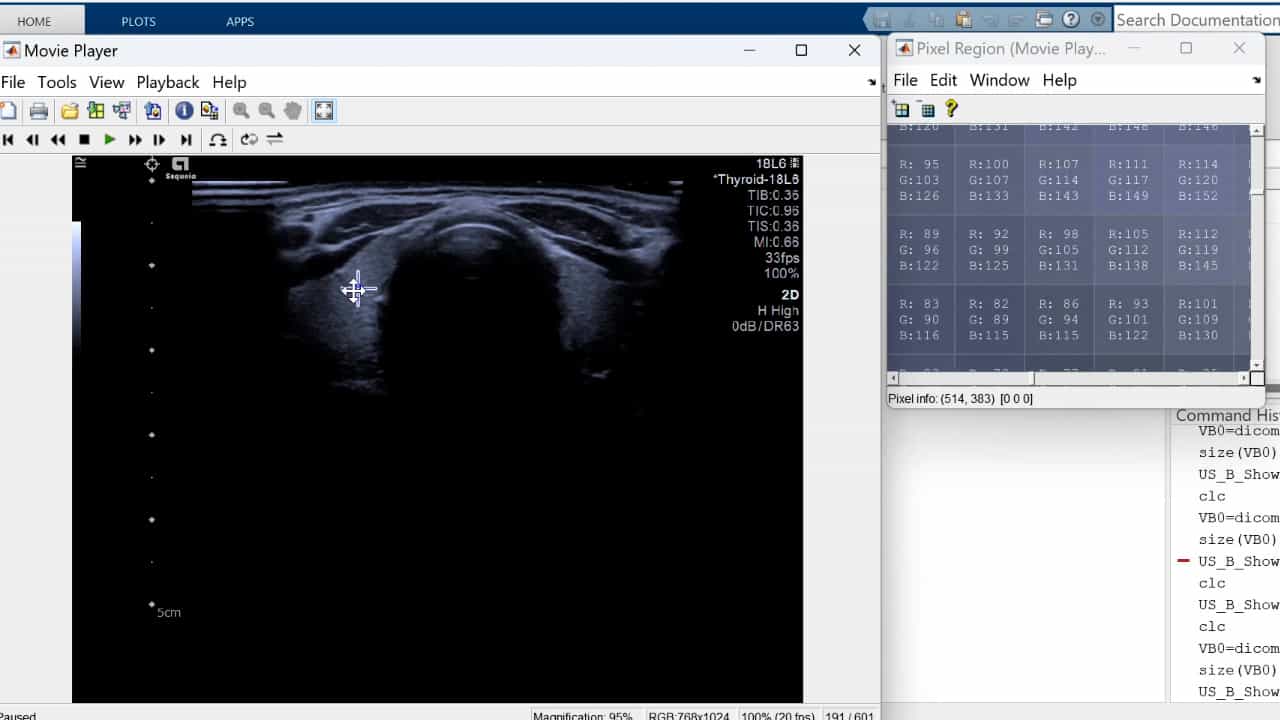

Synchronous Triplanar Reconstruction Integrated with Color Doppler Mapping for Precise and Rapid Localization of Thyroid Lesions
Published on: February 9, 2024
[Current questions of thyroid diseases in childhood]
1Debreceni Egyetem, Általános Orvostudományi Kar Gyermekgyógyászati Intézet, Endokrin Szakrendelés Debrecen Nagyerdei krt. 98. 4032. ilyesi@yahoo.com

Insights
Childhood thyroid diseases, including congenital hypothyroidism and Graves-basedow disease, stem from gene mutations or iodine deficiency. Early diagnosis and treatment, like l-thyroxin therapy, are crucial for good prognosis in pediatric thyroid disorders.
Area of Science:
- Pediatric Endocrinology
- Genetics
- Internal Medicine
Background:
- Thyroid diseases in children encompass a range of conditions, including congenital hypothyroidism, juvenile lymphocytic thyroiditis, hyperthyroidism, and thyroid nodules.
- Genetic mutations are implicated in various forms of congenital hypothyroidism and permanent hyperthyroidism, while iodine deficiency can lead to goiter and maternal hypothyroxinemia.
- Understanding the pathogenesis and diagnostic approaches for these conditions is essential for timely intervention.
Purpose of the Study:
- To review current knowledge on the diagnosis, pathogenesis, and management of various thyroid diseases in childhood.
- To highlight the role of genetic factors and iodine deficiency in pediatric thyroid disorders.
- To discuss treatment strategies and controversies in managing conditions like congenital hypothyroidism, Graves-basedow disease, and thyroid nodules.
Main Methods:
- Review of recent advancements in understanding pediatric thyroid diseases.
- Analysis of diagnostic criteria including clinical status, ultrasound, antibody detection, thyroid function tests, and fine needle aspiration cytology.
- Evaluation of treatment modalities such as l-thyroxin therapy, antithyroid drugs, surgery, and radioiodine treatment.
Main Results:
- Congenital hypothyroidism, often due to gene mutations or maternal factors, requires neonatal screening and early l-thyroxin treatment for optimal outcomes.
- Juvenile lymphocytic thyroiditis and hypothyroidism benefit from l-thyroxin therapy, while transient neonatal hyperthyroidism necessitates careful management.
- Graves-basedow disease treatment in children remains debated, with medical therapy showing low remission rates, prompting consideration of definitive treatments like surgery or radioiodine.
- Iodine deficiency disorders, such as goiter, are preventable with iodized salt and treatable with iodine or l-thyroxin.
- Thyroid nodules in children warrant investigation due to cancer risk, with medullary thyroid carcinoma requiring genetic screening and potential early thyroidectomy.
Conclusions:
- Early diagnosis and appropriate management, including genetic screening where indicated, are vital for improving outcomes in children with thyroid diseases.
- While l-thyroxin is standard for hypothyroidism, definitive treatment options for Graves-basedow disease in pediatric populations require further consideration.
- Preventive measures like iodine supplementation are crucial for addressing iodine deficiency disorders in children.
Abstract:
In recent years our knowledge on thyroid diseases in childhood has been increased. Several forms of congenital hypothyroidism (dysgenesis, dyshormongenesis, thyrotropin resistance and some central forms) are consequences of gene mutations. Maternal hypothyroxinemia due to severe iodine deficiency leads to early neurological damage and congenital hypothyroidism. Neonatal screening of congenital hypothyroidism and early treatment with l-thyroxin ensure good prognosis. Differential diagnosis of the various forms of congenital hypothyroidism in newborns is not an easy task. The need for treatment of transient hypothyroxinemia is still controversial. Diagnosis of juvenile lymphocytic thyroiditis can be ascertained by the clinical status, ultrasound examination, detection of anti-peroxydase antibodies, evaluation of thyroid function, and fine needle aspiration cytology. L-thyroxin therapy is recommended in cases of subclinical and manifest hypothyroidism. The transient form of the rare newborn hyperthyroidism is the consequence of maternal Graves-Basedow disease. It can be a sever condition and its permanent form is caused by TSH-receptor gene mutation. In the pathogenesis of autonomic thyroid adenoma mutations of the TSH-receptor and the alpha subunit of the stimulatory G-protein are involved. Treatment of Graves-Basedow disease in childhood is a debated question. The first choice is medical treatment with antithyroid and beta-blocking drugs. However, remission rate is low under this therapy, and the disease is characterised by frequent relapses. For this reason, the necessity of definitive therapy frequently arises. In Europe subtotal thyroidectomy is used as second choice of therapy, but clinical experience in the United States showed that radioiodine treatment is a safe and effective therapy for children and adolescents. Iodine deficient goitre in childhood is a form of iodine deficiency disorder. It is the consequence of adaptation to iodine deficiency. It can be treated by iodine or/and l-thyroxin, and its development can be prevented by iodinated salt. In childhood, thyroid nodule needs for a detailed investigation because of the possibility of thyroid cancer. Medullar thyroid carcinoma indicates genetic screening in the patients and their family, and the presence of disease-causing RET-proto-oncogene mutation confirms the need for total thyroidectomy already in childhood.

Related Concept Videos
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
Hypothyroidism II: Pathophysiology
 01:23
The Thyroid Gland
The follicles have a central cavity lined by simple cuboidal to squamous epithelial cells called follicular cells. These cells produce the glycoprotein...
 01:25
Hyperthyroidism I: Introduction