Related Experiment Video
Updated: Jun 2, 2026

Modified Posterior Vertebral Column Resection for Patients with Thoracolumbar Kyphotic Deformity
Published on: September 16, 2022
Kyphectomy for severe kyphosis with pyogenic spondylitis associated with myelomeningocele: a case report
Kenji Yoshioka1, Kota Watanabe2, Yoshiaki Toyama1
1Department of Orthopaedic Surgery, School of Medicine Keio University, 35 Shinanomachi, Shinjuku, Tokyo 160-8582, Japan.

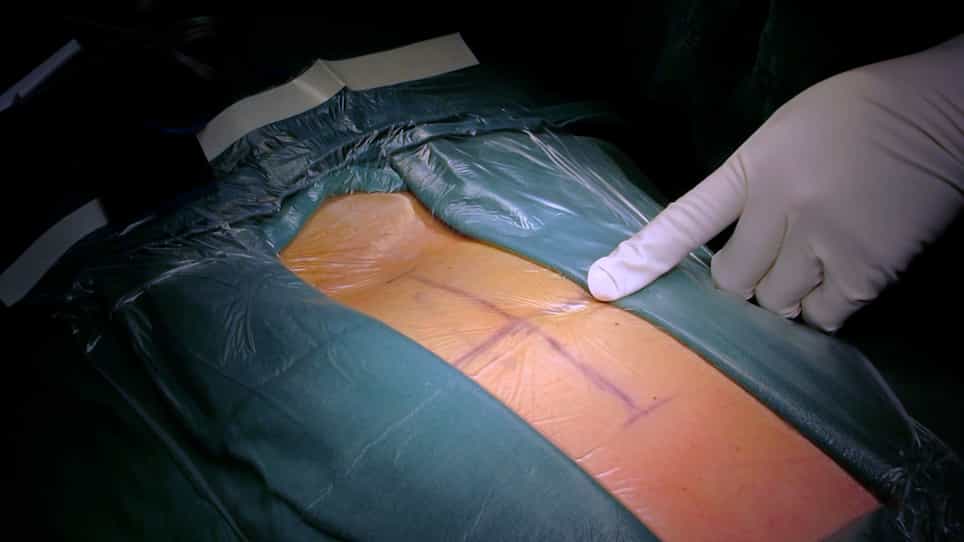
A 32-year-old woman was referred to our hospital for a refractory ulcer on her back. She had a history of myelomeningocele with spina bifida that was treated surgically at birth. The ulcer was located at the apex of the kyphosis. An X-ray film revealed a kyphosis of 154° between L1 and 3 and a scoliosis of 60° between T11 and L5. Computed tomography, magnetic resonance imaging and laboratory data indicated the presence of a pyogenic spondylitis at L2/3. To correct the kyphosis and remove the infected vertebrae together with the skin ulcer, kyphectomy was performed. Pedicle screws were inserted from T8 to T12 and from L4 to S1. The dural sac was transected and ligated at L2, followed by total kyphectomy of the L1-L3 vertebrae. The spinal column was reconstructed by approximating the ventral wall of the T12 vertebral body and the cranial endplate of the L4 vertebra. Postoperatively, the kyphosis was corrected to 61° and the scoliosis was corrected to 22°. In the present case, we treated the skin ulcer and pyogenic spondylitis successfully by kyphectomy, thereby, preventing recurrence of the ulcer and infection, and simultaneously obtaining sufficient correction of the spinal deformity.
A 32-year-old woman was referred to our hospital for a refractory ulcer on her back. She had a history of myelomeningocele with spina bifida that was treated surgically at birth. The ulcer was located at the apex of the kyphosis. An X-ray film revealed a kyphosis of 154° between L1 and 3 and a scoliosis of 60° between T11 and L5. Computed tomography, magnetic resonance imaging and laboratory data indicated the presence of a pyogenic spondylitis at L2/3. To correct the kyphosis and remove the infected vertebrae together with the skin ulcer, kyphectomy was performed. Pedicle screws were inserted from T8 to T12 and from L4 to S1. The dural sac was transected and ligated at L2, followed by total kyphectomy of the L1-L3 vertebrae. The spinal column was reconstructed by approximating the ventral wall of the T12 vertebral body and the cranial endplate of the L4 vertebra. Postoperatively, the kyphosis was corrected to 61° and the scoliosis was corrected to 22°. In the present case, we treated the skin ulcer and pyogenic spondylitis successfully by kyphectomy, thereby, preventing recurrence of the ulcer and infection, and simultaneously obtaining sufficient correction of the spinal deformity.