Related Experiment Videos
Racial disparities in blood pressure control and treatment differences in a Medicaid population, North Carolina,
Diane L Downie1, Dorothee Schmid, Marcus G Plescia
1Public Health Preparedness Program, Division of Public Health, 1 West Wilson St, Madison, WI 53703, USA. diane.downie@wi.gov

Insights
Blacks with high blood pressure had lower control rates than whites, despite receiving more interventions. Care patterns were insufficient to overcome racial disparities in blood pressure management.
Area of Science:
- Cardiovascular Health
- Health Disparities Research
- Public Health Policy
Background:
- Racial disparities in hypertension prevalence and control are significant public health concerns.
- Understanding factors contributing to these disparities is crucial for developing targeted interventions.
Purpose of the Study:
- To investigate racial disparities in blood pressure control and treatment interventions among Black and White Medicaid recipients.
- To examine patient, provider, and treatment characteristics influencing these disparities.
Main Methods:
- Retrospective chart review of 2,078 Black and 1,436 White North Carolina Medicaid recipients with hypertension.
- Analysis of provider responses and antihypertensive medication use over a one-year period.
Main Results:
- Blacks were less likely than Whites to achieve blood pressure control (43.6% vs. 50.9%).
- Blacks above goal received more frequent interventions, including 4+ antihypertensive drug classes and medication adjustments.
- A significant proportion of both groups above goal had fewer than two antihypertensive drug classes prescribed.
Conclusions:
- Despite more intensive interventions, Black Medicaid recipients had poorer blood pressure control compared to White recipients.
- Current care patterns are inadequate for achieving treatment goals and eliminating racial disparities in hypertension management.
- Further research into effective strategies for equitable hypertension control is warranted.
Introduction:
Racial disparities in prevalence and control of high blood pressure are well-documented. We studied blood pressure control and interventions received during the course of a year in a sample of black and white Medicaid recipients with high blood pressure and examined patient, provider, and treatment characteristics as potential explanatory factors for racial disparities in blood pressure control.
Methods:
We retrospectively reviewed the charts of 2,078 black and 1,436 white North Carolina Medicaid recipients who had high blood pressure managed in primary care practices from July 2005 through June 2006. Documented provider responses to high blood pressure during office visits during the prior year were reviewed.
Results:
Blacks were less likely than whites to have blood pressure at goal (43.6% compared with 50.9%, P = .001). Blacks above goal were more likely than whites above goal to have been prescribed 4 or more antihypertensive drug classes (24.7% compared with 13.4%, P < .001); to have had medication adjusted during the prior year (46.7% compared with 40.4%, P = .02); and to have a documented provider response to high blood pressure during office visits (35.7% compared with 30.0% of visits, P = .02). Many blacks (28.0%) and whites (34.3%) with blood pressure above goal had fewer than 2 antihypertensive drug classes prescribed.
Conclusion:
In this population with Medicaid coverage and access to primary care, blacks were less likely than whites to have their blood pressure controlled. Blacks received more frequent intervention and had greater use of combination antihypertensive therapy. Care patterns observed in the usual management of high blood pressure were not sufficient to achieve treatment goals or eliminate disparities.
Related Concept Videos
 01:25
Errors occurring during blood pressure monitoring
Several factors...
 01:10
Pre-Procedural Guidelines for Assessing Blood Pressure
 01:28
Factors affecting Blood pressure
Physiological Factors:
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.
 01:18
Hypertension and Regulation of Blood Pressure
 01:30
Blood Pressure
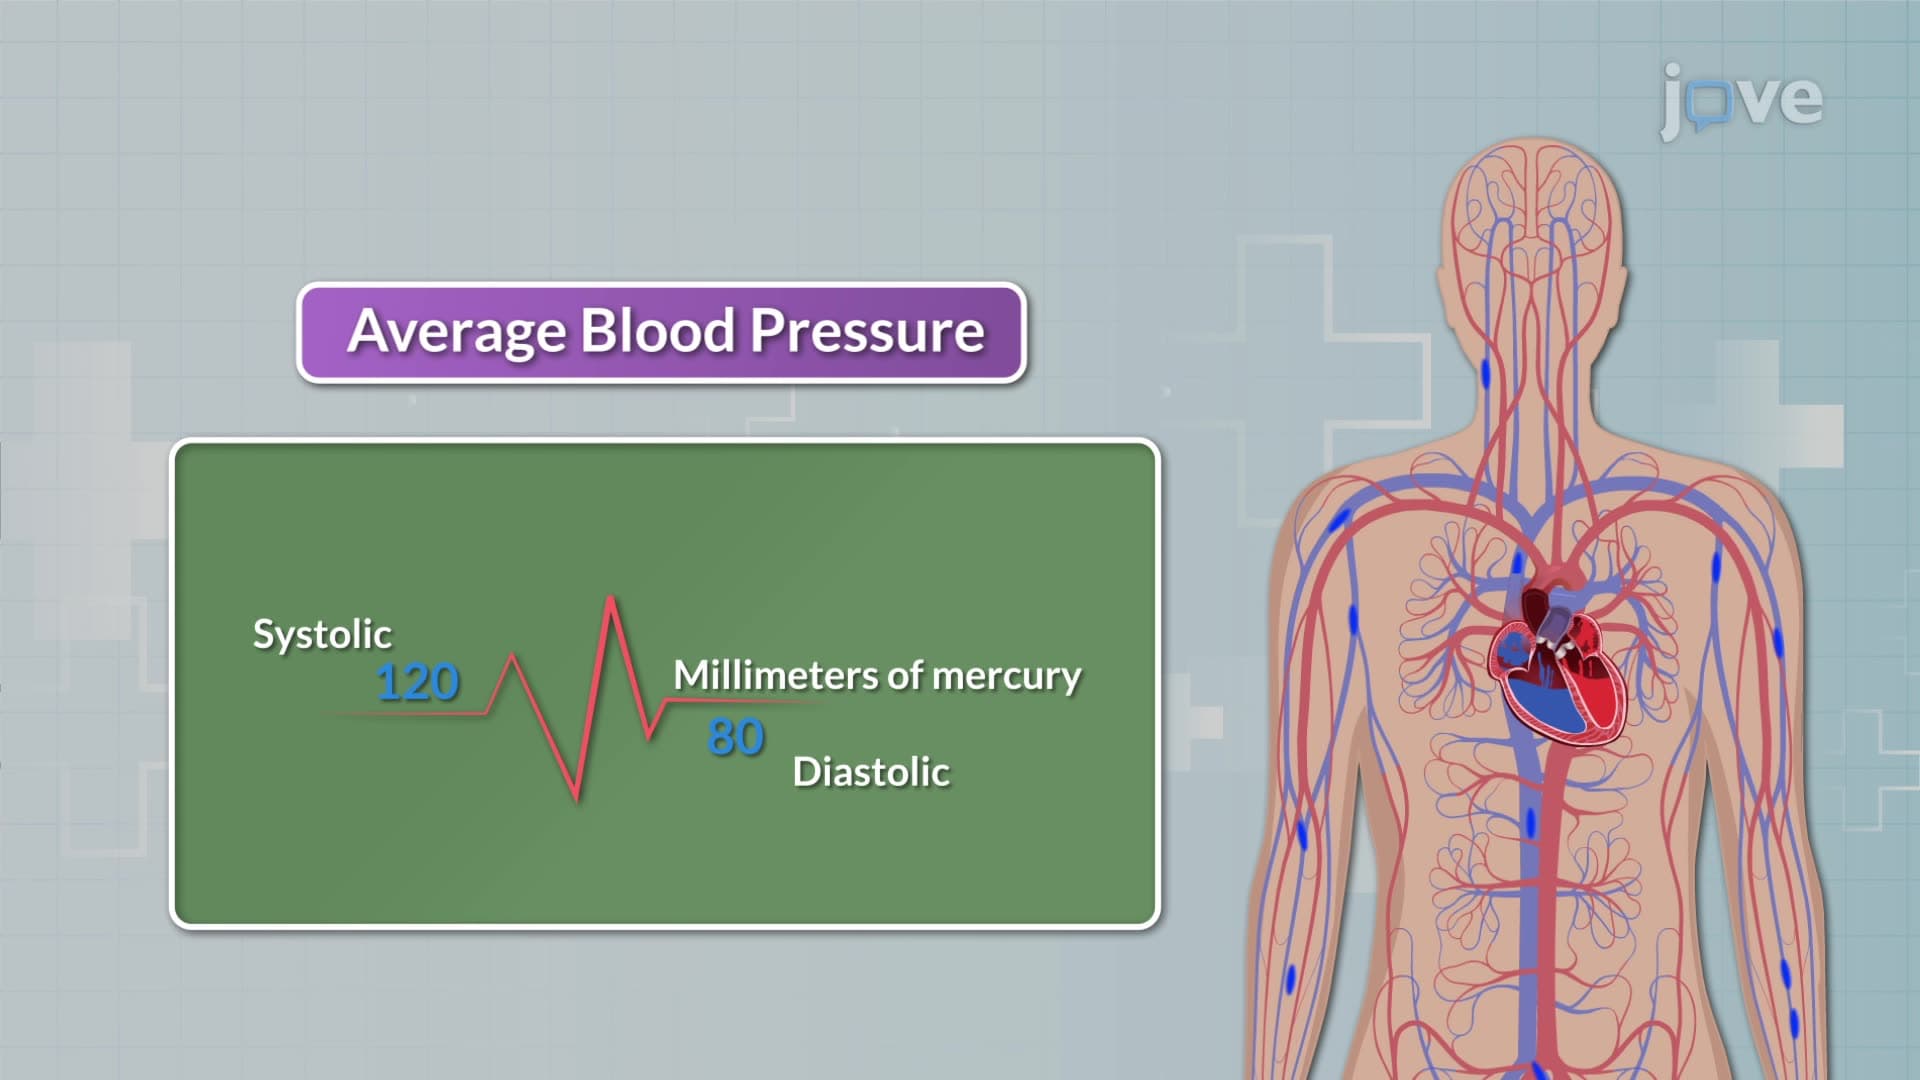
The average BP in an adult is typically around 120/80 mmHg (millimeters of mercury). In this measurement, the numerator (120) indicates the systolic pressure, which is the pressure in the arteries during the contraction of the heart's ventricles as blood is expelled. The denominator (80) represents the diastolic...