Related Experiment Video
Updated: Jun 2, 2026


Modeling and Evaluation of Murine Diabetic Cardiomyopathy Model
Published on: November 29, 2024
[Cardial target-organ damage in diabetes]
1Klinik für Kardiologie, Herz- und Diabeteszentrum Mecklenburg-Vorpommern, Greifswalder Strasse 11, Karlsburg, Germany. wmotz@drguth.de

Insights
Coronary heart disease and type 2 diabetes mellitus require interdisciplinary care. Metformin is the only antihyperglycemic with proven cardiovascular benefits, limiting endpoint-oriented treatment options.
Area of Science:
- Cardiology and Diabetology
- Interdisciplinary Patient Care
Context:
- Coronary heart disease (CHD) and type 2 diabetes mellitus (T2DM) often coexist.
- Arterial hypertension exacerbates cardiovascular risk in diabetic patients.
- Diabetic coronary artery disease (CAD) presents with rapid progression and diffuse peripheral distribution.
Purpose:
- To highlight the syntropic relationship between CHD and T2DM.
- To advocate for interdisciplinary management strategies.
- To review current antihyperglycemic therapies concerning cardiovascular endpoints.
Summary:
- Interdisciplinary care is crucial for patients with both CHD and T2DM.
- Coronary bypass surgery is preferred over percutaneous coronary stenting in severe diabetic CAD.
- Metformin is the only antihyperglycemic agent with documented cardiovascular endpoint reduction; thiazolidinediones (e.g., rosiglitazone) are associated with increased cardiovascular risk.
Impact:
- Emphasizes the need for integrated cardiology and diabetology approaches.
- Provides guidance on revascularization strategies for diabetic CAD.
- Informs antihyperglycemic treatment choices based on cardiovascular safety and efficacy.
Abstract:
Coronary heart disease and type 2 diabetes mellitus can be considered as a syntropy. Accordingly, cardiologists and diabetologists should organize an interdisciplinary car of the patient with both cardiac disease and diabetes mellitus. Arterial hypertension is frequently present in the diabetic condition and increases further morbidity and mortality rates due to the involvement of the coronary microcirculation. Coronary artery disease is characterized by a rapid progression and a diffuse distribution particularly in the periphery. Consequently in severe diabetic coronary artery disease coronary bypass surgery should be preferred rather than percutaneous coronary stenting, which should be favored in less severe cases. In the antihyperglycemic treatment a reduction in cardiovascular endpoints has only be documented after metformin. Therapy with thiazolidinediones has been terminated due to an increase in coronary morbidity and mortality under rosiglitazone. In as much glucagon-like peptide-I analogues and dipeptidylpeptidase 4 inhibitors will reduce cardiovascular endpoints has to be waited for. Thus an endpoint orientated antihyperglycemic treatment is limited to insulin, metformin and sulfonylureas.

Related Concept Videos
 01:27
Diabetic Retinopathy
 01:28
Diabetic Nephropathy
 01:24
Type II Diabetes II: Pathophysiology
 01:30
Cardiomyopathy II: Dilated Cardiomyopathy
 01:22
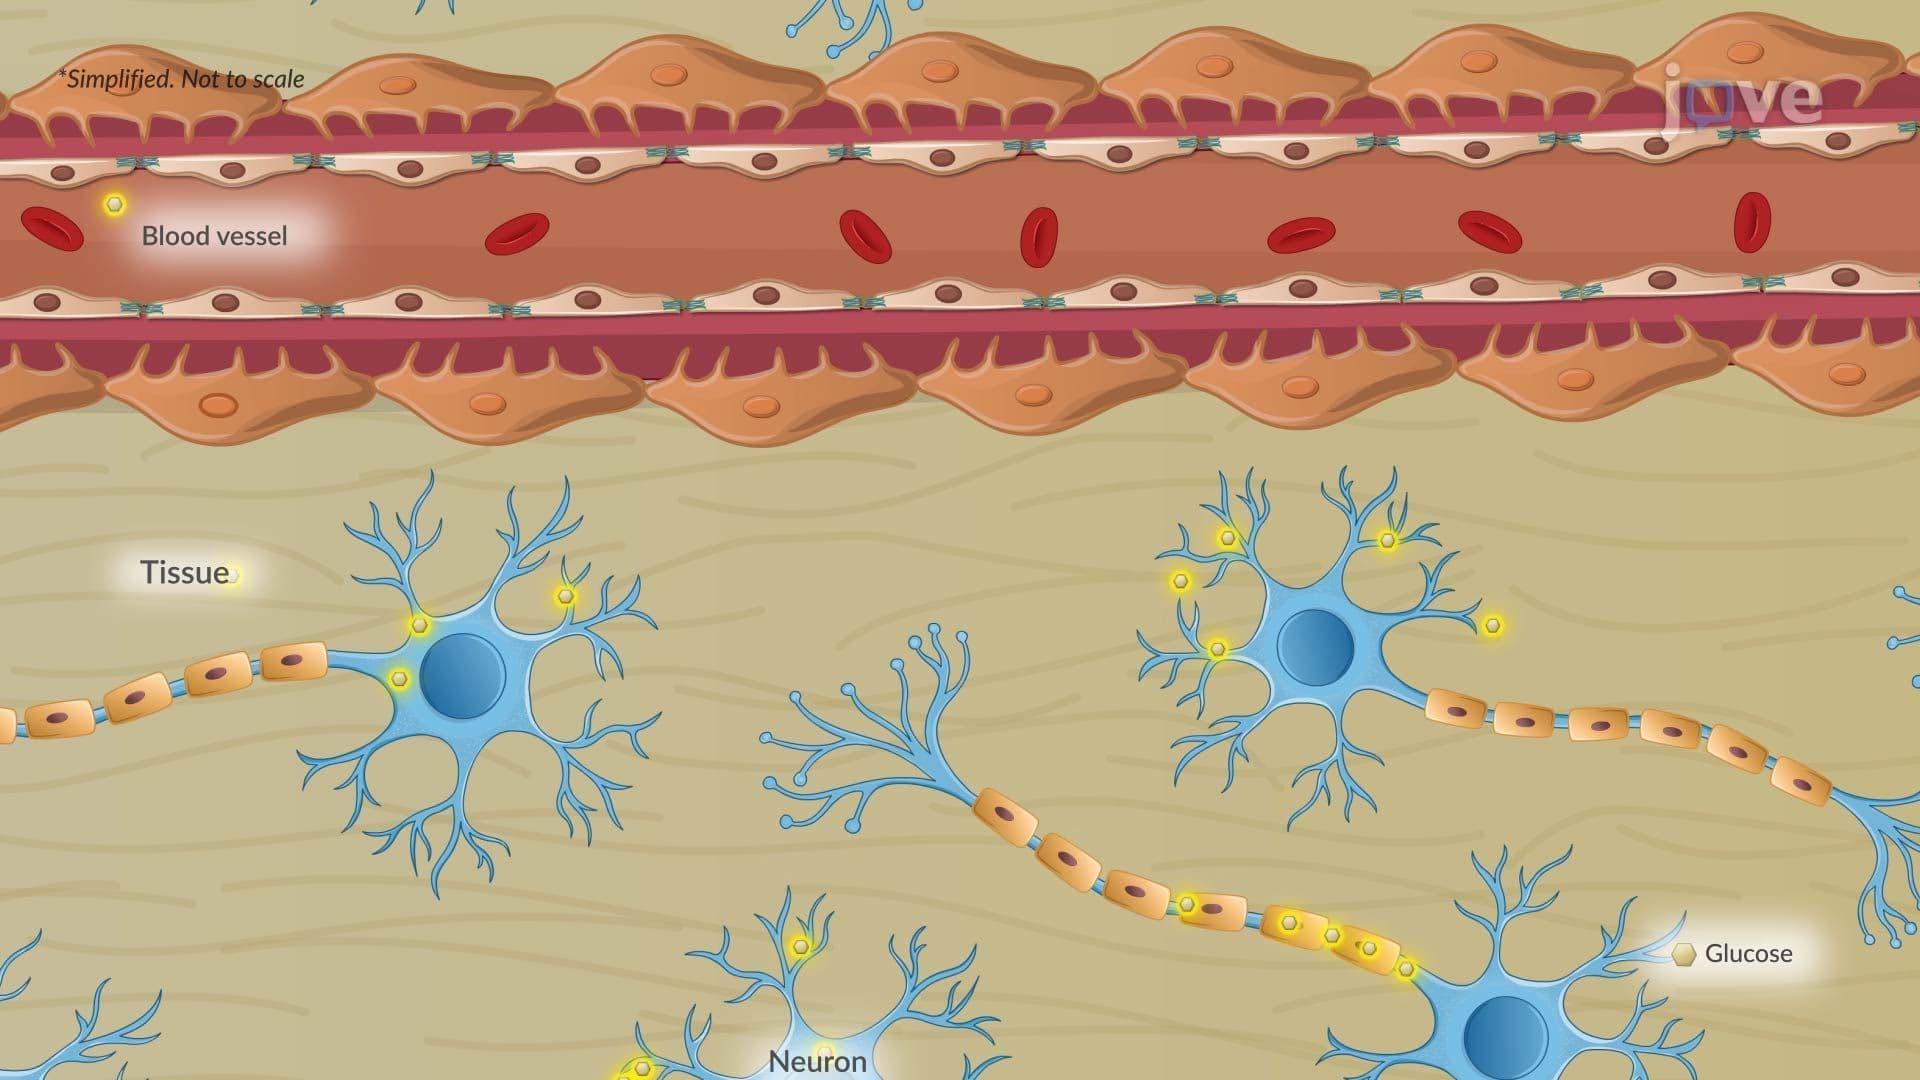
Diabetic Neuropathy
 01:20
Pathophysiology of Diabetes
Type 1 diabetes is characterized by autoimmune-mediated destruction of pancreatic β cells, with environmental factors potentially triggering this process in genetically susceptible individuals. Despite many not having a family history, certain genes increase susceptibility, suggesting a...