Related Experiment Video
Updated: Jun 2, 2026
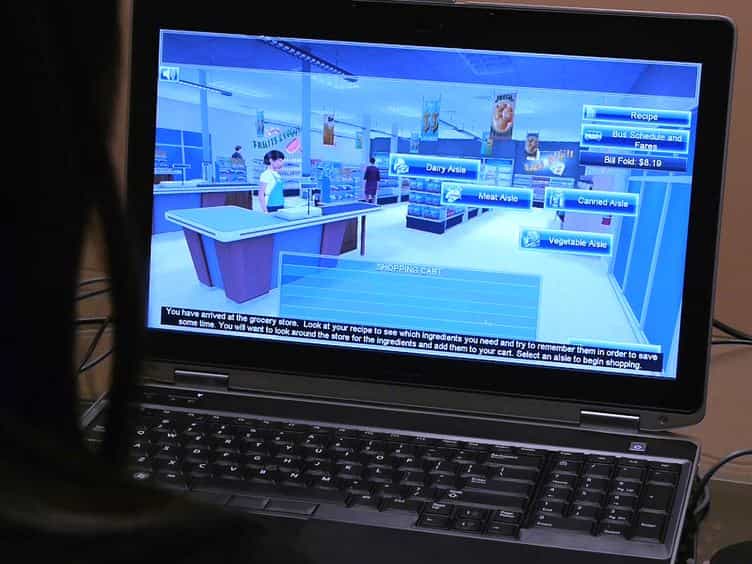
Development of a Virtual Reality Assessment of Everyday Living Skills
Published on: April 23, 2014
Temporal and Geographic variation in the validity and internal consistency of the Nursing Home Resident Assessment
Vincent Mor1, Orna Intrator, Mark Aaron Unruh
1Department of Community Health and Center for Gerontology & Health Care Research, Brown University Medical School, Box G-S121, Providence, Rhode Island, USA. Vincent_Mor@brown.edu

Background:
The Minimum Data Set (MDS) for nursing home resident assessment has been required in all U.S. nursing homes since 1990 and has been universally computerized since 1998. Initially intended to structure clinical care planning, uses of the MDS expanded to include policy applications such as case-mix reimbursement, quality monitoring and research. The purpose of this paper is to summarize a series of analyses examining the internal consistency and predictive validity of the MDS data as used in the "real world" in all U.S. nursing homes between 1999 and 2007.
Methods:
We used person level linked MDS and Medicare denominator and all institutional claim files including inpatient (hospital and skilled nursing facilities) for all Medicare fee-for-service beneficiaries entering U.S. nursing homes during the period 1999 to 2007. We calculated the sensitivity and positive predictive value (PPV) of diagnoses taken from Medicare hospital claims and from the MDS among all new admissions from hospitals to nursing homes and the internal consistency (alpha reliability) of pairs of items within the MDS that logically should be related. We also tested the internal consistency of commonly used MDS based multi-item scales and examined the predictive validity of an MDS based severity measure viz. one year survival. Finally, we examined the correspondence of the MDS discharge record to hospitalizations and deaths seen in Medicare claims, and the completeness of MDS assessments upon skilled nursing facility (SNF) admission.
Results:
Each year there were some 800,000 new admissions directly from hospital to US nursing homes and some 900,000 uninterrupted SNF stays. Comparing Medicare enrollment records and claims with MDS records revealed reasonably good correspondence that improved over time (by 2006 only 3% of deaths had no MDS discharge record, only 5% of SNF stays had no MDS, but over 20% of MDS discharges indicating hospitalization had no associated Medicare claim). The PPV and sensitivity levels of Medicare hospital diagnoses and MDS based diagnoses were between .6 and .7 for major diagnoses like CHF, hypertension, diabetes. Internal consistency, as measured by PPV, of the MDS ADL items with other MDS items measuring impairments and symptoms exceeded .9. The Activities of Daily Living (ADL) long form summary scale achieved an alpha inter-consistency level exceeding .85 and multi-item scale alpha levels of .65 were achieved for well being and mood, and .55 for behavior, levels that were sustained even after stratification by ADL and cognition. The Changes in Health, End-stage disease and Symptoms and Signs (CHESS) index, a summary measure of frailty was highly predictive of one year survival.
Conclusion:
The MDS demonstrates a reasonable level of consistency both in terms of how well MDS diagnoses correspond to hospital discharge diagnoses and in terms of the internal consistency of functioning and behavioral items. The level of alpha reliability and validity demonstrated by the scales suggest that the data can be useful for research and policy analysis. However, while improving, the MDS discharge tracking record should still not be used to indicate Medicare hospitalizations or mortality. It will be important to monitor the performance of the MDS 3.0 with respect to consistency, reliability and validity now that it has replaced version 2.0, using these results as a baseline that should be exceeded.

Related Concept Videos
 01:29
Documentation in Long-Term and Home Healthcare Setting
Long-Term Care Facilities
 01:03
Data Validation
Nursing assessment guides are generally based on holistic models rather than medical...
 01:29
Nursing Assessment
The nurse collects all aspects of the patient's health in the initial assessment, establishing priorities for ongoing focused assessments and...
 01:25
Formulating and Validating Nursing Diagnosis II
Risk nursing diagnoses represent clinical judgments of an individual, family, or community more vulnerable to developing the health problem than others...
 01:05
Data Collection III
The principles to begin the physical assessment include conducting a comprehensive or problem-related history in a quiet, well-lit room, emphasizing privacy and comfort for the patient.
 01:26
Guidelines for Nursing Documentation II
Timely documentation is crucial to ensure continuity of care for patients. Any delays in recording or reporting medical information can result in medical errors and even adverse patient outcomes. From medication administration to diagnostic test results, every detail must be accurately and promptly documented to provide the best possible care for patients.