Related Experiment Video
Updated: Sep 30, 2026

Scanning Electron Microscopy of Macerated Tissue to Visualize the Extracellular Matrix
Published on: June 14, 2016
[Myocardial structure in various forms of hypertrophy. II. Myocyte hypertrophy or hyperplasia? Results of the study]
S Grajek1, S Paradowski, M Zajac
1Kliniki Kardiologii Instytutu Kardiologii AM w Poznaniu.

Insights
Cardiac muscle hypertrophy involves changes in myocyte size and number. Increased heart weight above 250g leads to myocyte hyperplasia, a result of cardiac muscle mass increase.
Area of Science:
- Cardiovascular pathology
- Cardiac remodeling
- Histopathology
Background:
- Cardiac muscle hypertrophy is a common adaptation to increased workload.
- Understanding the cellular mechanisms of hypertrophy is crucial for diagnosing and managing heart disease.
Purpose of the Study:
- To investigate the relationship between left ventricular (LV) weight and myocyte characteristics in hypertrophied hearts.
- To determine the role of myocyte hyperplasia in cardiac enlargement.
Main Methods:
- Histometric analysis of myocyte diameter, length, volume, density, and number in 103 human hearts.
- Correlation of these parameters with LV weight.
- Evaluation of factors influencing LV weight, including coronary artery diameter and atherosclerosis.
Main Results:
- Histometric parameters correlated with LV weight up to 350g; heavier hearts showed similar magnitudes.
- Myocyte number was significantly higher in hearts >250g (5.53 x 10^9) vs <250g (4.31 x 10^9).
- LV weight was influenced by coronary artery diameters; myocyte hyperplasia was observed in hearts >250g, irrespective of etiology.
Conclusions:
- Cardiac muscle mass increase leads to myocyte hyperplasia.
- Hypertrophy progresses to hyperplasia beyond a certain threshold of LV weight.
- Myocyte hyperplasia is a common finding in advanced heart failure, regardless of the underlying cause.
Abstract:
In 103 hearts with various forms of cardiac muscle hypertrophy the following parameters were estimated: diameter, length, volume, density and number of myocytes, as well as the density of nuclei of myocytes. The values of all histometric parameters correlated well with the LV weight up to 350 g. In heavier hearts these parameters were approximately at the same magnitude. The number of myocytes was significantly higher in hearts with LV weight above 250 g than in hearts below 250 g: 5.53 x 10(9) vs 4.31 x 10(9), p less than 0.001. The influence of coronary artery diameters, degree of atherosclerosis, weight and percent of fibrous tissue and age on LV weight were evaluated as well. Only coronary artery diameters significantly influenced on LV weight. On the basis of linear discriminant function, three classes of hearts were separated: 1) LV weight 250 g - absence of hyperplasia, only hypertrophy 2) LV weight 251-350 g - hypertrophy + signs of hyperplasia 3) LV weight 350 g - marked signs of hyperplasia Among 18 patients with the LV weight above 350 g (all patients with congestive heart failure), 11 suffered from valvular disease, 3 were postinfarction patients, 2 suffered from primary hypertension and 2 from primary congestive cardiomyopathy. It indicates that, irrespective to the etiologic factor, hyperplasia is a simple result of the cardiac muscle mass increase.


Related Concept Videos
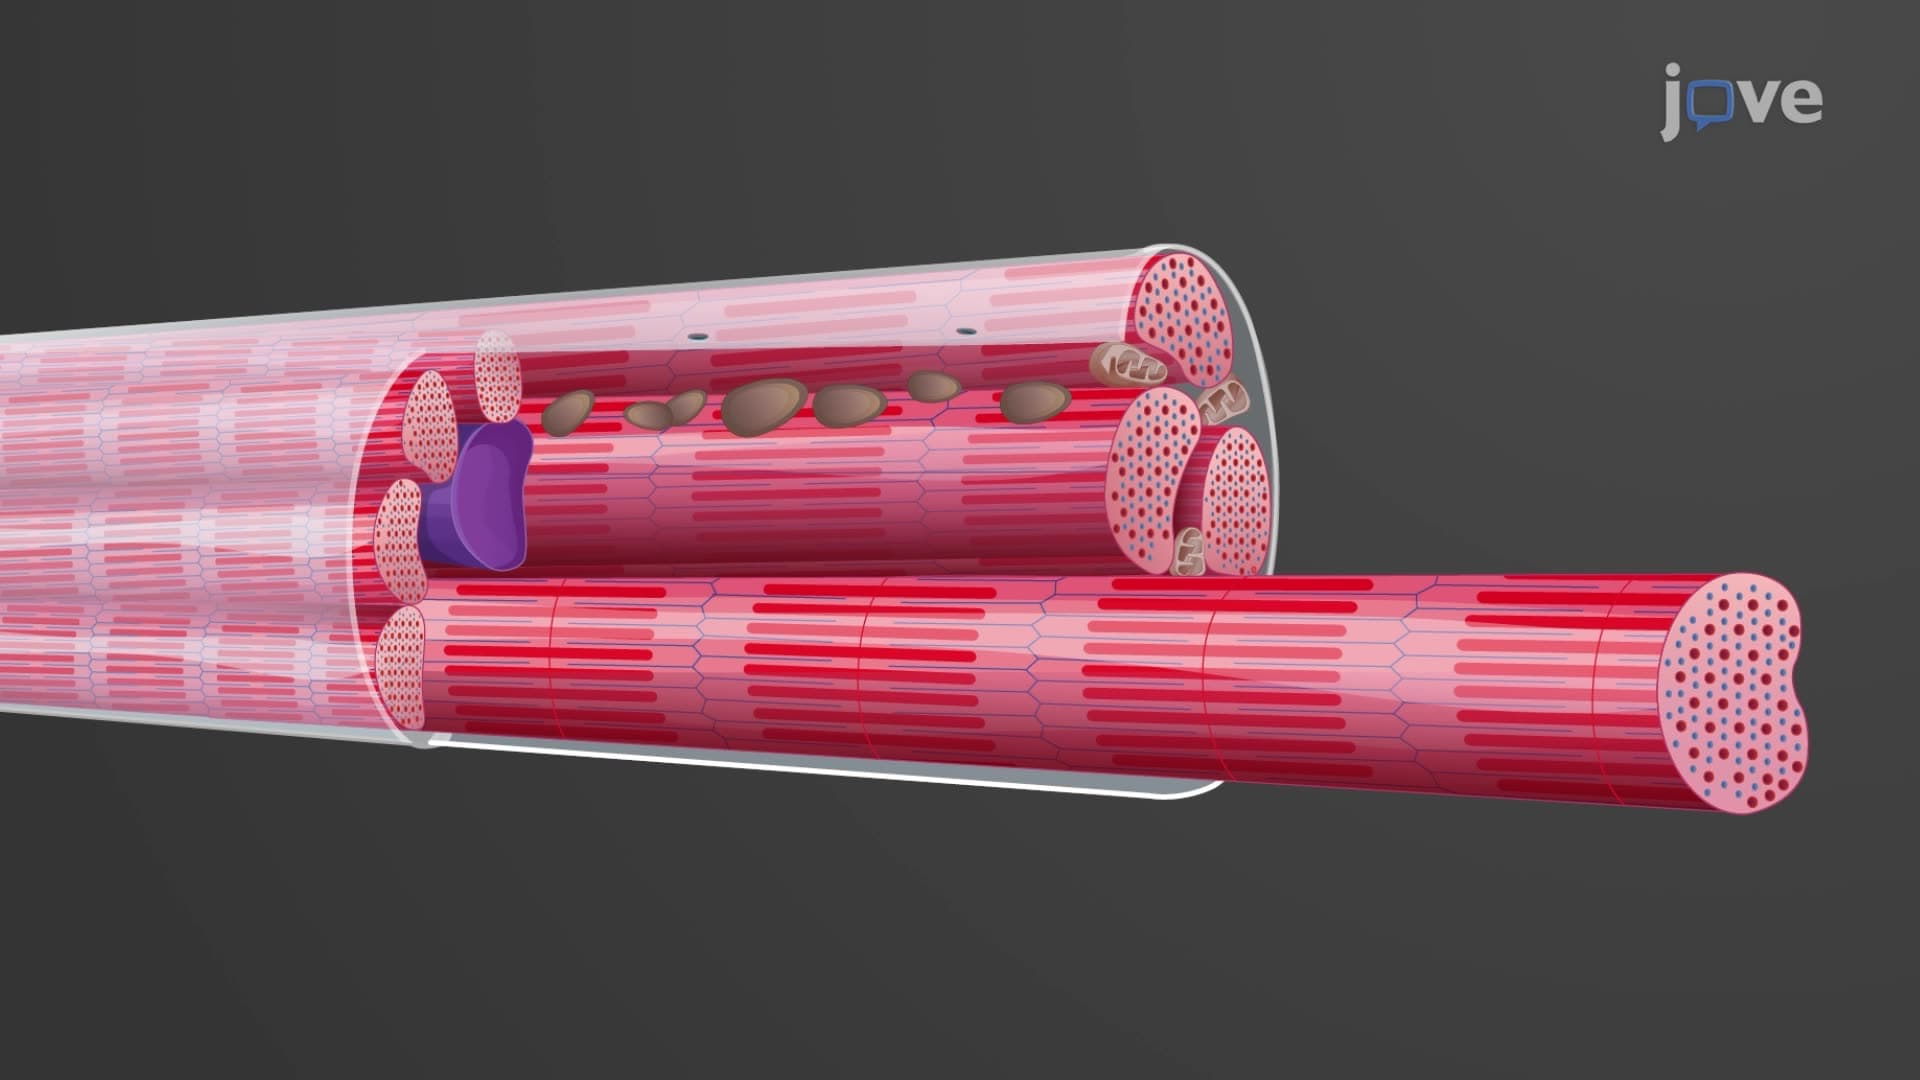 01:13
Structure of Cardiac Muscles
Compared to skeletal muscles, cardiac muscle cells are small and mostly have a single nucleus. Additionally, they are usually...
 01:21
Myocarditis I: Introduction
 01:27
Myocarditis II: Clinical Features and Diagnostic Tests
 01:29
Heart Failure II: Pathophysiology
 01:29
Cardiomyopathy III: Hypertrophic Cardiomyopathy
 01:26
Cellular Adaptation II: Hypertrophy