Related Experiment Video
Updated: Jun 2, 2026

08:27

Bronchoalveolar Lavage Exosomes in Lipopolysaccharide-induced Septic Lung Injury
Published on: May 21, 2018
Exit of leucocytes across the alveolar epithelium worsens lung injury
Thorax
|April 22, 2011

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:26
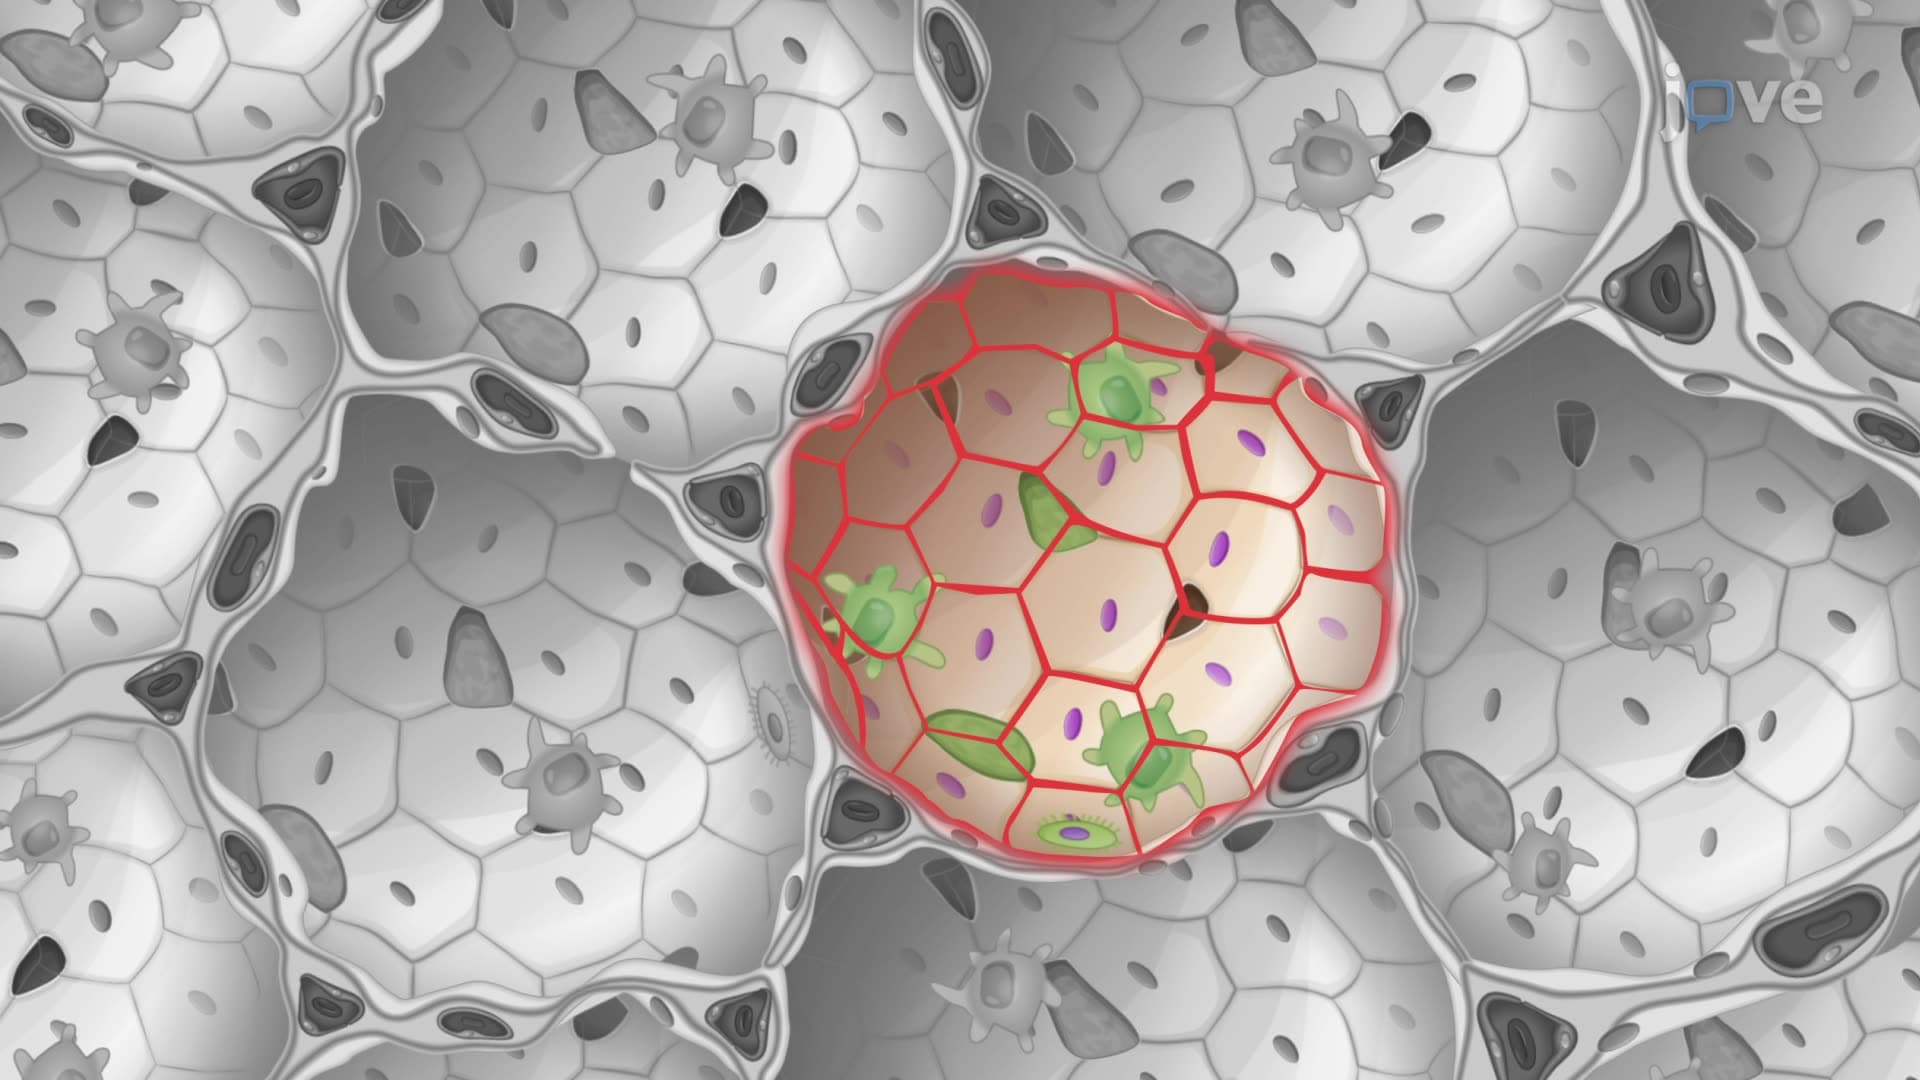
Alveoli and Alveolar Ducts
The respiratory zone of the human body, which stands in contrast to the conducting zone, comprises the structures that actively participate in the exchange of gases. The initiation of this zone is marked by the terminal bronchioles converging into respiratory bronchioles, the tiniest bronchiole classification. The respiratory bronchioles give way to the alveolar ducts that opens into a congregation of alveoli. Actively involved in gas exchange, alveoli resemble tiny sacs similar to clusters of...
 01:23
Chronic Obstructive Pulmonary Disease II: Emphysema
Emphysema, a major phenotype of chronic obstructive pulmonary disease (COPD), is characterized by irreversible destruction of alveolar walls and permanent enlargement of distal airspaces. Unlike chronic bronchitis, which primarily affects the airways, emphysema predominantly involves the lung parenchyma, where structural damage leads to airflow limitation.PathophysiologyIt most commonly results from prolonged exposure to cigarette smoke and other toxic gases, particularly cigarette smoke.
 01:20
Chronic Obstructive Pulmonary Disease-II: Pathophysiology
Chronic Obstructive Pulmonary Disease (COPD) pathophysiology is intricate and multifaceted, involving a complex interplay of physiological processes. Understanding these mechanisms is crucial for effectively managing and treating COPD. Here is an in-depth look at the critical elements in the pathophysiology of COPD:
Chronic Inflammation
Chronic Inflammation
 01:10
Atelectasis II: Pathophysiology
Atelectasis develops when alveoli lose their air and collapse inward. Because lung tissue is naturally elastic, these air sacs shrink rather than remaining open. Collapsed alveoli are no longer ventilated, reducing their role in gas exchange. Blood flow may continue in these regions, creating a ventilation–perfusion mismatch. Clinical findings include decreased breath sounds, dullness to percussion, reduced chest expansion, and decreased tactile fremitus as sound transmission through collapsed...
 01:18
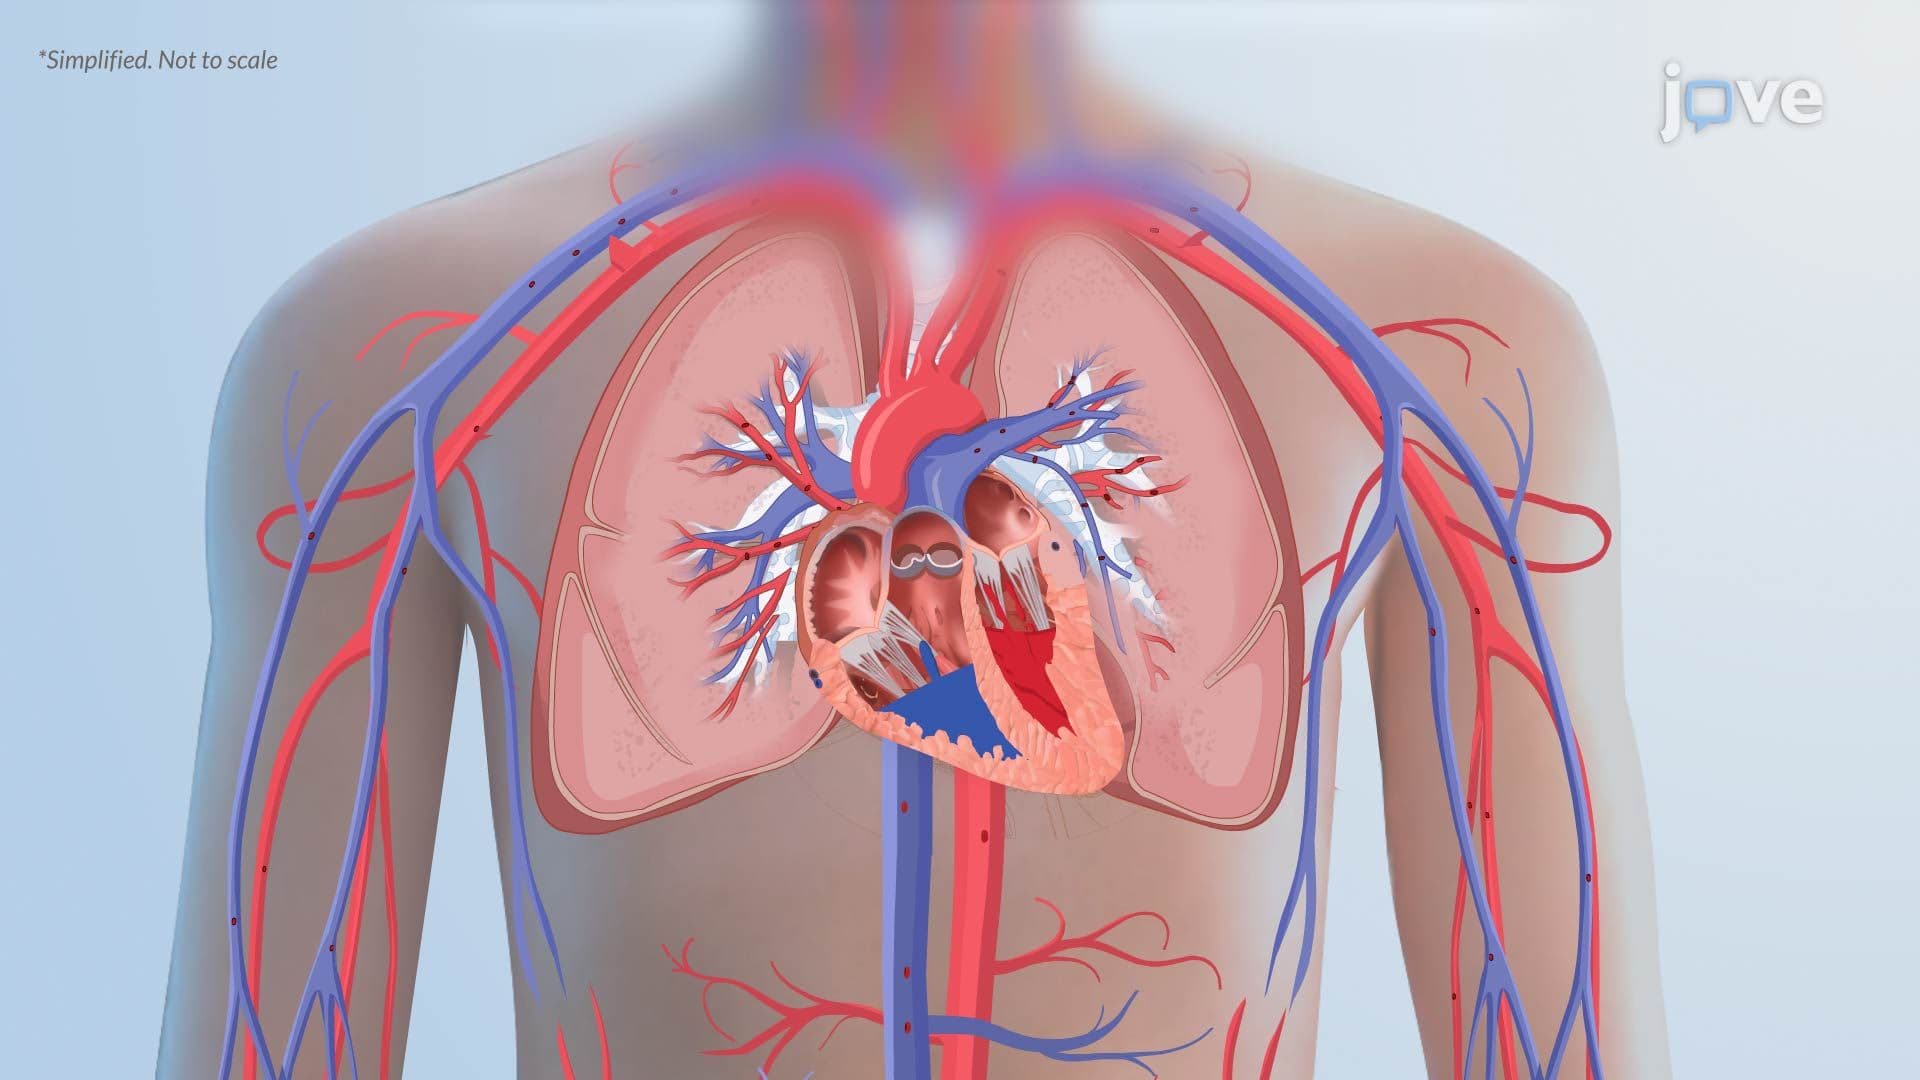
Pulmonary Edema II: Pathophysiology
Pulmonary edema is the accumulation of fluid in the interstitial and alveolar spaces of the lungs, impairing gas exchange and oxygen delivery. It may be cardiogenic or noncardiogenic, but both reduce oxygenation and lung compliance.Cardiogenic Pulmonary EdemaCardiogenic edema results from increased hydrostatic pressure in pulmonary capillaries, usually due to left ventricular dysfunction from myocardial infarction, heart failure, or valvular disease. Ineffective cardiac pumping causes blood to...
 01:24
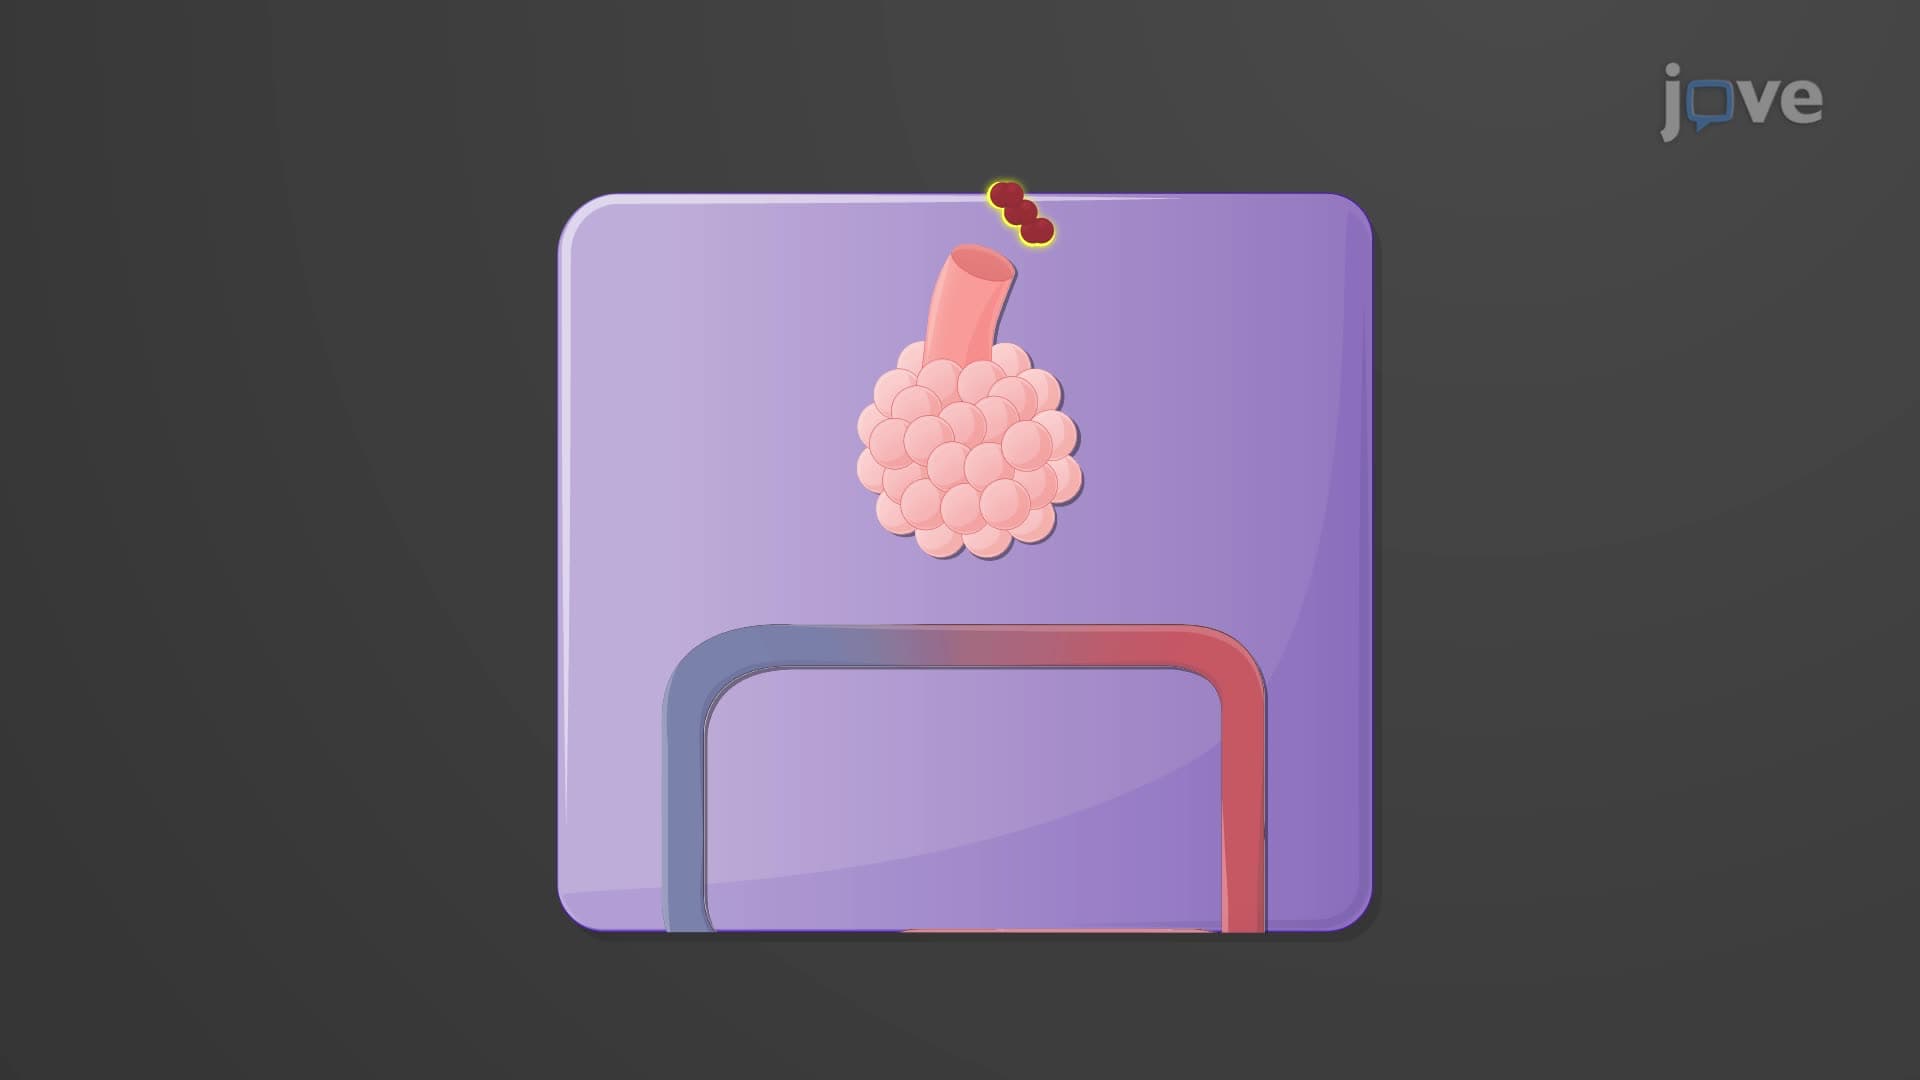
External and Internal Respiration
External respiration occurs in the lungs, and it is the first step in the journey of oxygen inside the body. When we inhale, oxygen enters our lungs and diffuses across the thin alveolar membrane. The alveoli are tiny, air-filled sacs that provide a vast surface area for gas exchange. Oxygen in the alveoli has a higher partial pressure (105 mmHg) than in the adjacent pulmonary capillaries (40 mmHg), establishing a pressure gradient. As a result, oxygen molecules move from the alveoli into the...