Contralateral trigeminal neuropathy in a case of convexity cerebellar meningioma

Kaushik Ghosh1, S P Ghorai, Suniti Saha

  • 1Department of Neurosurgery, Bangur Institute of Neurology and Institute of Postgraduate Medical Education and Research, Kolkata.

Related Concept Videos

Cranial Nerves: Types Part I01:14

Cranial Nerves: Types Part I

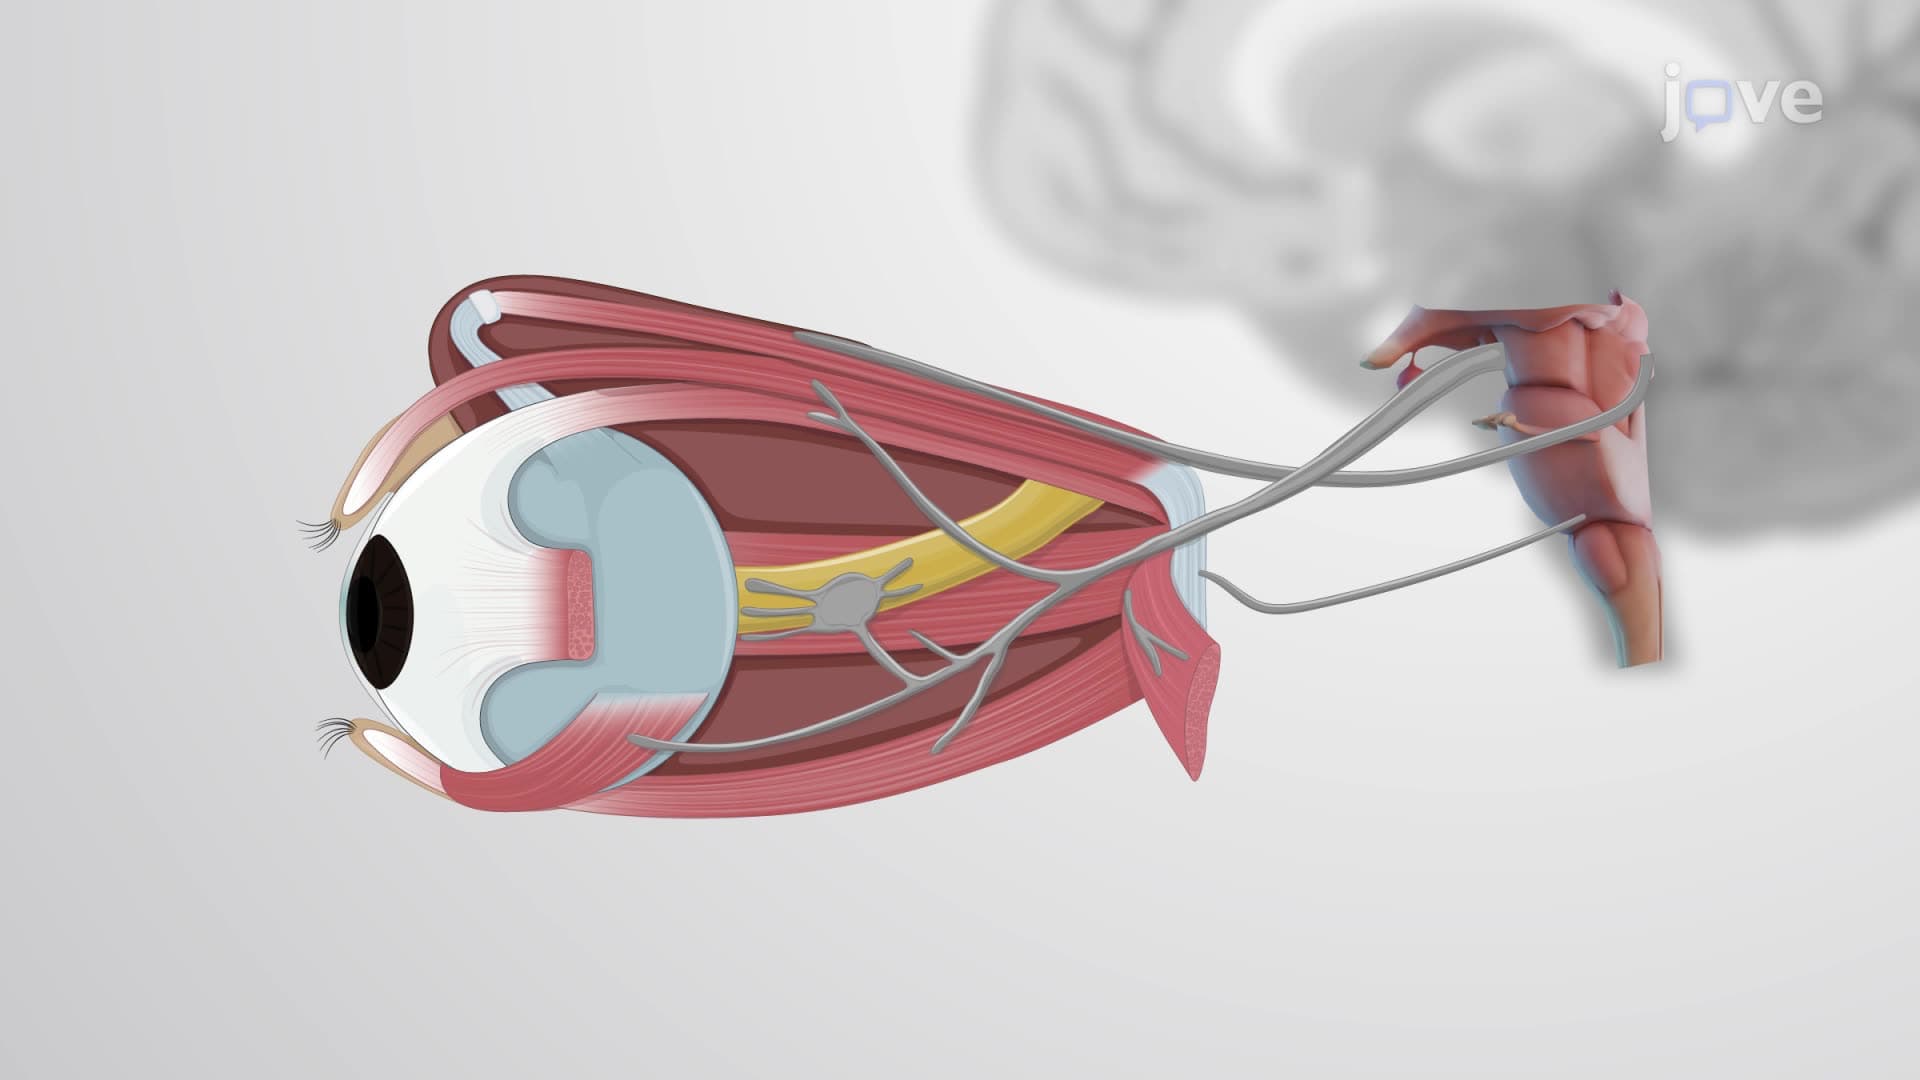
Cranial nerves are responsible for transmitting motor and sensory information between the brain and various parts of the body. There are twelve pairs of cranial nerves, with the first six being essential in sensory perception, motor control, and autonomic functions related to the head and neck.
Olfactory Nerve (Cranial Nerve I)
The olfactory nerve, or cranial nerve I, is unique as it is purely sensory and dedicated to the sense of smell. This nerve originates in the olfactory epithelium of the...
Major Somatic Sensory Pathways01:28

Major Somatic Sensory Pathways

Sensory impulses related to touch, pressure, vibration, and proprioception from various body parts, such as the limbs, trunk, neck, and posterior head, travel to the cerebral cortex through the posterior column-medial lemniscus pathway. The pathway’s name derives from the two white-matter tracts that convey the impulses: the spinal cord's posterior column and the brainstem's medial lemniscus. First-order sensory neurons extend their axons into the spinal cord, forming the posterior columns...
Cranial and Spinal Meninges01:19

Cranial and Spinal Meninges

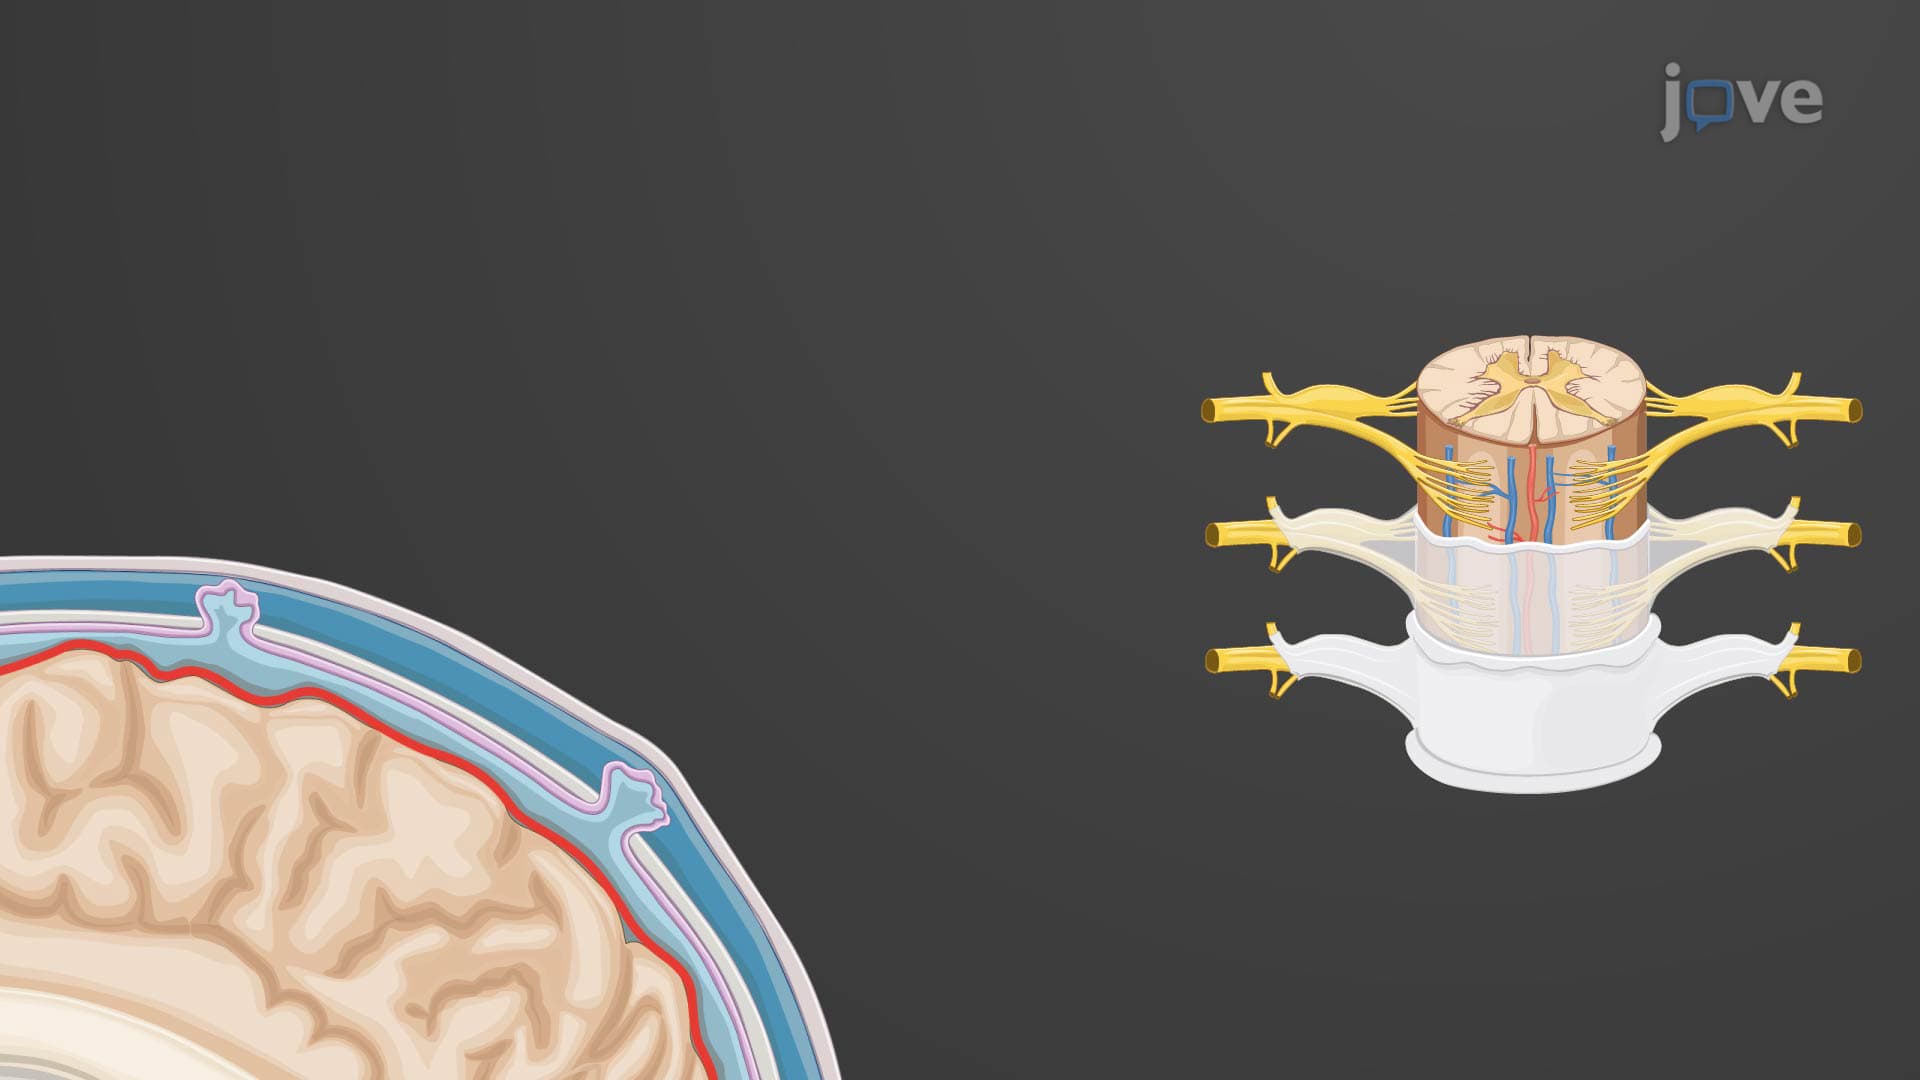
The cranial and spinal meninges are complex protective structures surrounding the central nervous system (CNS), consisting of the brain and spinal cord. These meninges consist of the dura mater, the arachnoid mater, and the pia mater. They protect the CNS, provide structural support, and aid in circulating cerebrospinal fluid (CSF).
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...

Secondary Spinal Cord Injury llI: Pathophysiology01:25

Secondary Spinal Cord Injury llI: Pathophysiology

Early Ischemia and Ionic ImbalanceWithin minutes of spinal cord injury, a secondary cascade begins, progressing over hours to weeks. Vascular damage reduces blood flow, causing ischemia and mitochondrial dysfunction. ATP depletion leads to ion pump failure, membrane depolarization, sodium influx, potassium efflux, and water accumulation, resulting in cellular swelling. Increased intracellular calcium further disrupts mitochondria and accelerates cellular injury.Excitotoxicity and Neuronal...
Cerebral Edema ll: Pathophysiology01:22

Cerebral Edema ll: Pathophysiology

Vasogenic edema is a major form of cerebral edema characterized by abnormal accumulation of fluid in the brain’s extracellular space due to disruption of the blood–brain barrier (BBB). The BBB is a specialized structure composed of endothelial cells connected by tight junctions, supported by astrocytic endfeet and a basement membrane. Under normal conditions, it tightly regulates the movement of ions, proteins, and solutes between the bloodstream and brain parenchyma. When this barrier loses...
Increased Intracranial Pressure ll: Pathophysiology01:29

Increased Intracranial Pressure ll: Pathophysiology

Increased intracranial pressure (ICP) refers to a potentially life-threatening rise in pressure inside the skull. This usually happens when there is a major change in the volume of brain tissue, blood, or cerebrospinal fluid (CSF) — the three components inside the skull. According to the Monro-Kellie doctrine, if the volume of one component increases, the volumes of the other components must decrease to maintain normal pressure. If this does not happen, ICP rises.The process often begins with...