Induction of tolerance to parental parathyroid grafts using allogeneic thymus tissue in patients with DiGeorge anomaly
Related Experiment Video
Updated: May 12, 2026
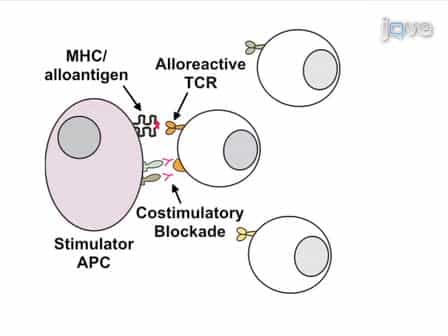
Induction of Alloantigen-specific Anergy in Human Peripheral Blood Mononuclear Cells by Alloantigen Stimulation with Co-stimulatory Signal Blockade
Published on: March 14, 2011
Ivan K Chinn1, M Louise Markert
1Department of Pediatrics, Division of Allergy and Immunology, Duke University Medical Center, Durham, NC 27710, USA. chinn001@mc.duke.edu

DiGeorge anomaly can affect both thymic and parathyroid function. Although athymia is corrected by allogeneic thymus transplantation, treatment options for hypoparathyroidism have been unsatisfactory. Parathyroid transplantation offers the potential for definitive cure but remains challenging because of graft rejection. Some allogeneic parathyroid grafts have functioned in adult recipients in the context of immunosuppression for renal transplantation. Other efforts have attempted to reduce the allogenicity of the parathyroid grafts through manipulation of the parathyroid tissues before transplantation (by using encapsulation or special culture techniques). Recently, we demonstrated the efficacy of parental parathyroid transplantation when combined with allogeneic thymus transplantation in an infant with complete DiGeorge anomaly. The recipient developed tolerance toward the parathyroid donor. The parathyroid graft has functioned for 5 years after transplantation without the need for continued immunosuppression or calcium supplementation. We observed that matching of the allogeneic thymus graft to the parathyroid donor HLA class II alleles that are unshared with the recipient appears to be associated with the induction of tolerance toward the parathyroid graft. Further work is needed to determine the optimal means for using combined allogeneic thymus and parental parathyroid transplantation to correct hypoparathyroidism in patients with both complete and partial DiGeorge anomaly.
DiGeorge anomaly can affect both thymic and parathyroid function. Although athymia is corrected by allogeneic thymus transplantation, treatment options for hypoparathyroidism have been unsatisfactory. Parathyroid transplantation offers the potential for definitive cure but remains challenging because of graft rejection. Some allogeneic parathyroid grafts have functioned in adult recipients in the context of immunosuppression for renal transplantation. Other efforts have attempted to reduce the allogenicity of the parathyroid grafts through manipulation of the parathyroid tissues before transplantation (by using encapsulation or special culture techniques). Recently, we demonstrated the efficacy of parental parathyroid transplantation when combined with allogeneic thymus transplantation in an infant with complete DiGeorge anomaly. The recipient developed tolerance toward the parathyroid donor. The parathyroid graft has functioned for 5 years after transplantation without the need for continued immunosuppression or calcium supplementation. We observed that matching of the allogeneic thymus graft to the parathyroid donor HLA class II alleles that are unshared with the recipient appears to be associated with the induction of tolerance toward the parathyroid graft. Further work is needed to determine the optimal means for using combined allogeneic thymus and parental parathyroid transplantation to correct hypoparathyroidism in patients with both complete and partial DiGeorge anomaly.