Related Experiment Video
Updated: Jun 2, 2026

Separation of Immune Cell Subpopulations in Peripheral Blood Samples from Children with Infectious Mononucleosis
Published on: September 7, 2022
[Intravascular large B-cell lymphoma: an important cause of fever of unknown origin]
Yasufumi Masaki1, Miyuki Miki, Tomoyuki Sakai
1Hematology and Immunology, Kanazawa Medical University, Daigaku, Uchinada, Kahoku-gun, Ishikawa, Japan.

Intravascular large B-cell lymphoma (IVLBCL) is an important cause of fever of unknown origin (FUO) and multiple organ failure (MOF). Earlier, most IVLBCL cases were diagnosed only postmortem; however, now, it is possible to diagnose and treat these cases antemortem. Although hematogeneous dissemination of malignant tumor cells except lymphoma is beyond the scope of present treatment regimens, IVLBCL (hematogeneous dissemination of lymphoma) can be treated by chemotherapy so correct diagnosis is important. The onset and clinical course of IVLBCL is heterogeneous. Many IVLBCL cases show rapid deterioration, but some have a relatively indolent early period that transforms to rapid progression later. Leukemic appearance is not uncommon. It is difficult to distinguish between IVLBCL and lymphomas originating from extra-nodular organs with systemic dissemination into extra-nodular organs. Minimally invasive and highly sensitive procedures are required for its accurate diagnosis: bone marrow aspiration and biopsy, and random skin biopsy are recommended. If IVLBCL is suspected, to achieve the correct diagnosis, we should avoid glucocorticoid therapy before a biopsy is obtained, even in serious cases. IVLBCL shows remarkable response to treatment with rituximab-containing chemotherapy (R-CHOP). Delayed administration of rituximab and reduced dose of chemotherapy on the first course may be initially indicated in elderly, poor performance status or cases with high tumor burden. High-dose chemotherapy with autologous hematopoietic stem cell rescue should be considered, if possible. Aggressive combination therapy with high dose methotrexate is a recent idea because of central nervous system involvement, or relapse is common and there is poor prognosis.
Intravascular large B-cell lymphoma (IVLBCL) is an important cause of fever of unknown origin (FUO) and multiple organ failure (MOF). Earlier, most IVLBCL cases were diagnosed only postmortem; however, now, it is possible to diagnose and treat these cases antemortem. Although hematogeneous dissemination of malignant tumor cells except lymphoma is beyond the scope of present treatment regimens, IVLBCL (hematogeneous dissemination of lymphoma) can be treated by chemotherapy so correct diagnosis is important. The onset and clinical course of IVLBCL is heterogeneous. Many IVLBCL cases show rapid deterioration, but some have a relatively indolent early period that transforms to rapid progression later. Leukemic appearance is not uncommon. It is difficult to distinguish between IVLBCL and lymphomas originating from extra-nodular organs with systemic dissemination into extra-nodular organs. Minimally invasive and highly sensitive procedures are required for its accurate diagnosis: bone marrow aspiration and biopsy, and random skin biopsy are recommended. If IVLBCL is suspected, to achieve the correct diagnosis, we should avoid glucocorticoid therapy before a biopsy is obtained, even in serious cases. IVLBCL shows remarkable response to treatment with rituximab-containing chemotherapy (R-CHOP). Delayed administration of rituximab and reduced dose of chemotherapy on the first course may be initially indicated in elderly, poor performance status or cases with high tumor burden. High-dose chemotherapy with autologous hematopoietic stem cell rescue should be considered, if possible. Aggressive combination therapy with high dose methotrexate is a recent idea because of central nervous system involvement, or relapse is common and there is poor prognosis.

Related Concept Videos
 01:25
Types of Fever
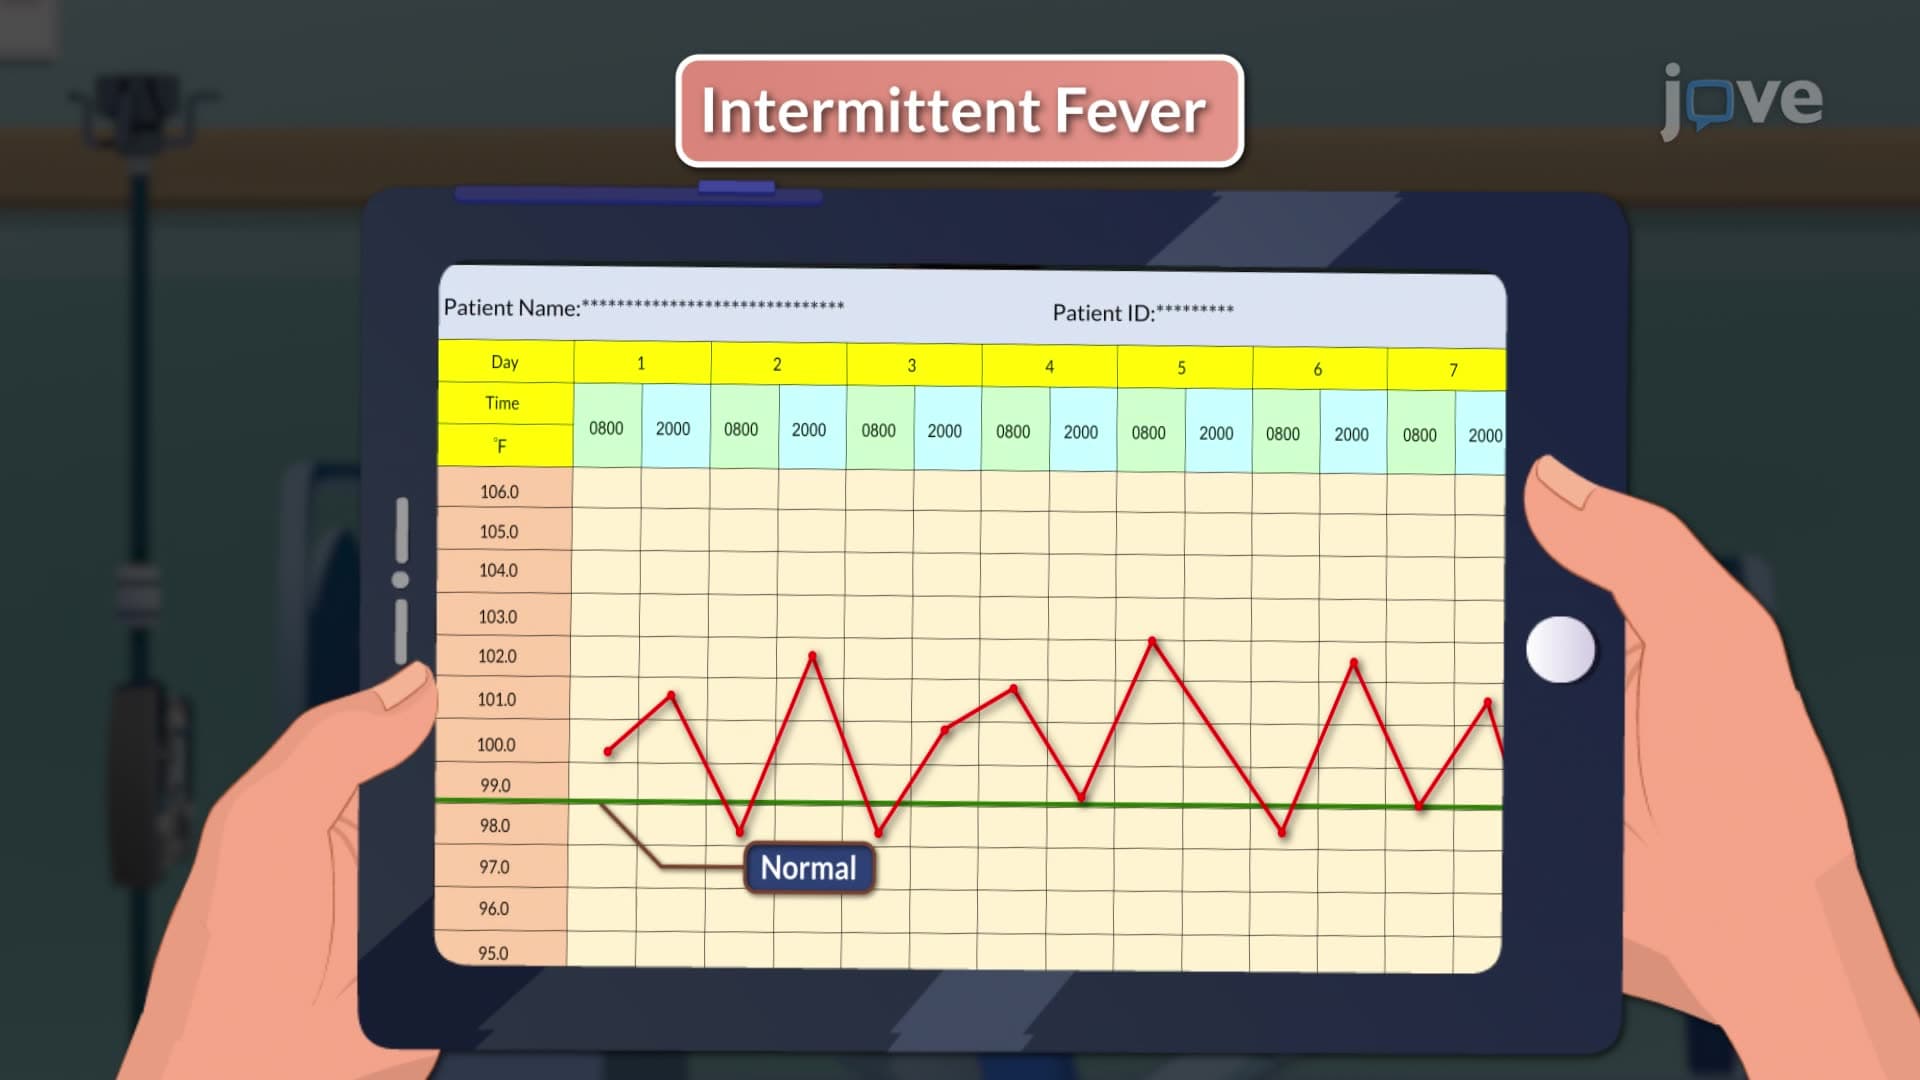
Here are the different types of fever:
 01:25
Increased Body Temperature
 01:26
Patterns of Fever
 01:27
Disorders of Leukocytes
Leukopenia may result from bone marrow disorders, autoimmune diseases, and infectious diseases. For example, conditions such as multiple myeloma and aplastic anemia can impair the bone marrow's ability to produce adequate leukocytes. Similarly, autoimmune diseases like lupus and viral infections such as HIV can prompt the immune system...
 01:28
Graves' Disease I: Introduction
 01:19
Encephalitis l: Introduction