Related Experiment Video
Updated: Jun 2, 2026
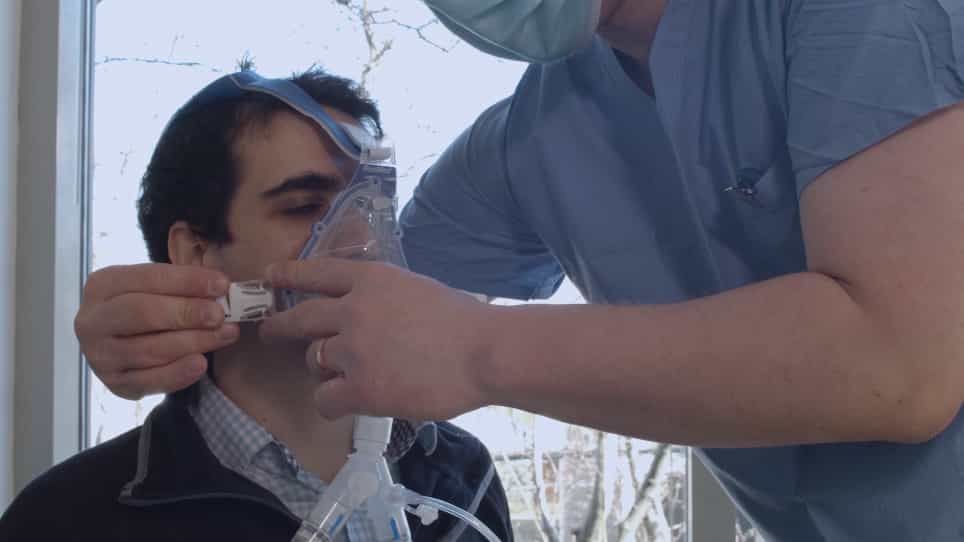

A Novel Inhalation Mask System to Deliver High Concentrations of Nitric Oxide Gas in Spontaneously Breathing Subjects
Published on: May 4, 2021
Effects of inhaled nitric oxide in neonatal hypoxemic respiratory failure from a multicenter controlled trial
Yi-fei Wang1, Cui-qing Liu, Xi-rong Gao
1Department of Pediatrics and Neonatology, Children's Hospital of Fudan University, Laboratory of Neonatology, Ministry of Health, Shanghai, China.

Background:
Hypoxemic respiratory failure (HRF) is one of the most common causes for neonatal infants requiring aggressive respiratory support. Inhaled nitric oxide (iNO) has been established routinely as an adjunct to conventional respiratory support in developed countries. The aim of this study was to investigate effects of iNO in neonates with HRF in resource limited condition with no or limited use of surfactant, high frequency oscillatory ventilation (HFOV) and extracorporeal membrane oxygenation.
Methods:
A non-randomized, open, controlled study of efficacy of iNO was conducted over 18 months. Eligible term and near-term neonates from 28 hospitals with HRF (oxygenation index > 15) were enrolled prospectively into two groups as either iNO or control. Oxygenation improvement and mortality as primary endpoint were determined in relation with dosing and timing of iNO, severity of underlying diseases, complications and burden. Intention-to-treat principle was adopted for outcome assessment. Response to iNO at 10 or 20 parts per million (ppm) was determined by oxygenation in reference to the control (between-group) and the baseline (within-group).
Results:
Compared to 93 controls, initial dose of iNO at 10 ppm in 107 treated infants significantly improved oxygenation from first hour (P = 0.046), with more partial- and non-responders improved oxygenation with subsequent 20 ppm NO (P = 0.018). This effect persisted on days 1 and 3, and resulted in relatively lower mortalities (11.2% vs. 15%) whereas fewer were treated with surfactant (10% vs. 27%), HFOV (< 5%) or postnatal corticosteroids (< 10%) in both groups. The overall outcomes at 28 days of postnatal life in the iNO-treated was not related to perinatal asphyxia, underlying diseases, severity of hypoxemia, or complications, but to the early use of iNO. The cost of hospital stay was not significantly different in both groups.
Conclusions:
With relatively limited use of surfactant and/or HFOV in neonatal HRF, significantly more responders were found in the iNO-treated patients as reflected by improved oxygenation in the first three days over the baseline level. It warrants a randomized, controlled trial for assessment of appropriate timing and long-term outcome of iNO.

Related Concept Videos
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:16
Treatment for Pulmonary Arterial Hypertension: Oxygen Therapy for Respiratory Failure
Oxygen therapy is vital in increasing and maintaining blood oxygen levels in PAH patients. As a result, it aids in reducing fatigue, improving...
 01:23
Physiological Control of Respiration
Breathing, a seemingly passive process, is regulated by the respiratory center in the brainstem. This center coordinates the involuntary control of respirations, which means it occurs without conscious effort, ensuring a smooth and uninterrupted pattern.
Regulation of Ventilation
The body maintains ventilation by monitoring levels of carbon dioxide (CO2), oxygen (O2), and hydrogen ion concentration (pH) in the arterial blood. Among these factors, the level of CO2 plays a crucial...
 01:21
Acute Respiratory Failure-II
The underlying physiological abnormalities that contribute to hypoxemic respiratory failure include: